

SNF billing guidelines for Medicare Part A start with a qualifying 3-day hospital stay, then an accepted assessment, a HIPPS rate code and a monthly claim on the UB-04 or 837I. Payment runs per day under PDPM, for up to 100 days per benefit period, and the facility bills most services itself.
Many older articles on skilled nursing billing mix care levels, retired RUG tables and Medicaid and Medicare forms. This rewrite replaces them with what current CMS sources say, so a billing lead, administrator or owner can see the whole path from admission to payment.
It also folds in the questions readers asked in our earlier posts on RUG rates, the MDS and Part A coverage days, and keeps only what we could verify.
Key takeaways
- Part A needs a 3-day inpatient hospital stay, then covers up to 100 days per benefit period.
- In 2026 the daily coinsurance is $217 for days 21 to 100, per Medicare.gov.
- PDPM replaced RUG-IV on October 1, 2019; RUG rate tables are obsolete.
- The accepted MDS assessment sets the rate code, so billing starts there.
- Consolidated billing makes the SNF responsible for most covered-stay services.
What SNF billing covers, and what this guide leaves out
SNF billing is the process a skilled nursing facility uses to charge Medicare for a covered skilled stay. It is not the same thing as invoicing a resident for private-pay room and board. This guide covers Medicare Part A stays, which is where the rules are most specific and where most claim problems start.
Medicare Part A pays for a stay only when the resident needs daily skilled care, given by or under the supervision of skilled nursing or therapy staff (per Medicare.gov). Independent living or personal care alone does not meet that test. Medicaid, Medicare Advantage and commercial plans each set their own rules, so check the payer before applying anything below.
Claims for Medicare go to the Medicare Administrative Contractor (MAC) in the 837 institutional electronic format or on Form CMS-1450, which carries the UB-04 data set (Medicare Claims Processing Manual, Chapter 6, section 10.1). One mix-up is worth clearing up: the CMS-1450 is a Medicare Part A claim form here, not a Medicaid one. If you are new to the form, our medical claim forms guide explains how institutional and professional forms differ.
Medicare Part A SNF coverage: the 3-day stay and 100 days
To qualify, a resident needs a medically necessary hospital inpatient stay of at least three days in a row, and usually enters the SNF within 30 days of leaving the hospital. Observation or emergency department time does not count toward the three days (see Medicare.gov and the CMS Medicare Learning Network SNF billing reference (MLN006846, January 2026)).
Some plans waive the stay. The CMS reference says Medicare Advantage plans, 1876 Cost plans, PACE plans and certain ACO-affiliated SNFs may waive the 3-day requirement, so verify the payer’s rule before you assume a missed stay means a denial.
Coverage runs by benefit period. A benefit period ends after the patient has not been an inpatient of a hospital or SNF for 60 consecutive days. Within one period, Part A covers up to 20 full days, then up to 80 more days with daily coinsurance, and the benefit is exhausted after 100 days (CMS Medicare Learning Network SNF billing reference (MLN006846, January 2026)). A resident who is readmitted within 30 days of discharge can resume benefit days without a new qualifying hospital stay.
| Days in the benefit period | What Medicare pays | What the resident pays (2026) |
|---|---|---|
| Days 1 to 20 | Full SNF coverage | $0 per day, after the $1,736 Part A deductible |
| Days 21 to 100 | Coverage continues | $217 per day coinsurance |
| Day 101 and later | No SNF coverage in that benefit period | All costs |
| Medicare Advantage enrollees | Set by the plan | Plans may charge copayments in the first 20 days |
Source: Medicare.gov, Skilled nursing facility care (2026 amounts)
Day 21 does not start Part B
A common myth says Medicare Part B begins on day 21. It does not. Day 21 changes the daily coinsurance inside the Part A benefit. The 2026 amounts above change each January, so confirm the current figure before you quote a family.
The same questions come up often in our older rate explainer, Medicare daily rates for skilled nursing facilities, and in our comparison of Medicare Part A versus Part B. Use those for background, and use CMS pages for any figure you put on a claim or a resident notice.
How an SNF claim is built: assessment, HIPPS code, UB-04
An SNF Medicare claim is built from the resident’s assessment, not just from the services listed in the chart. The facility may bill only after the assessment is submitted to the state assessment database, a validation report shows it was accepted, and the covered day has been used (Medicare Claims Processing Manual, Chapter 6, section 30.1).
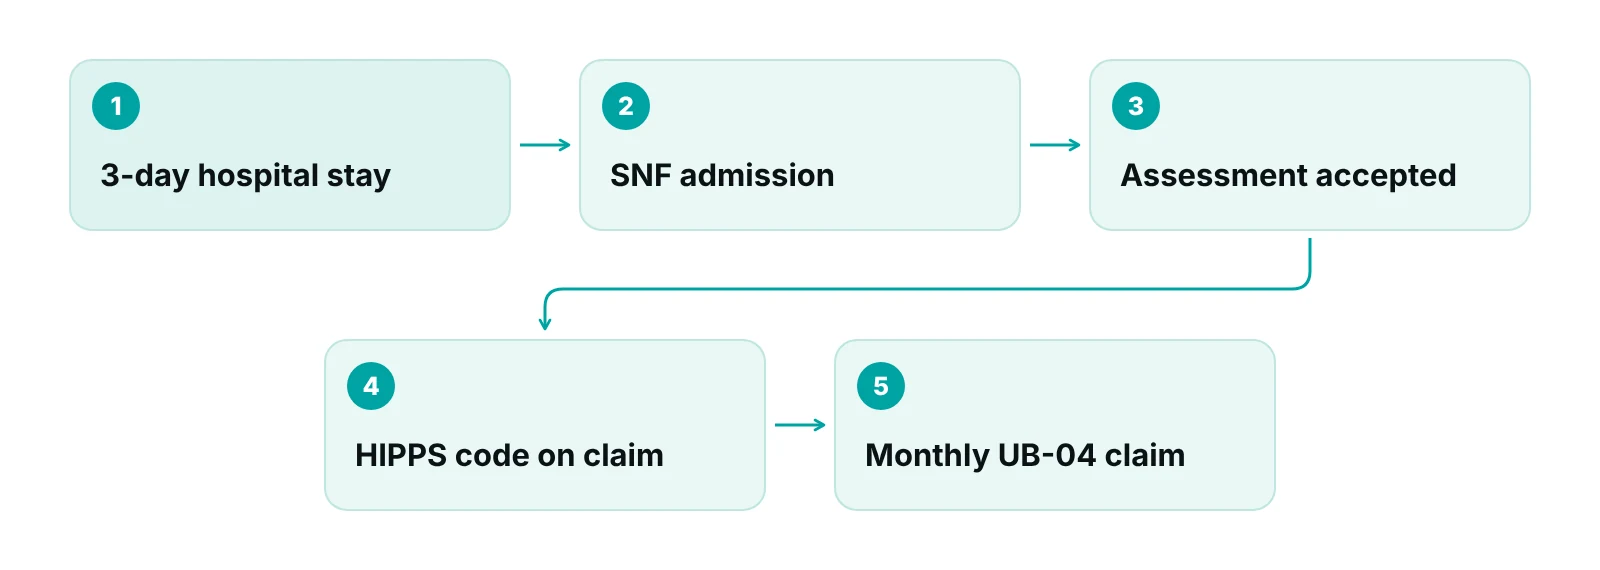
The claim then carries a rate code, called a HIPPS code, that reflects the resident’s assessed level of care. The CMS billing reference lists the key fields on the UB-04, shown in Table 2 (CMS Medicare Learning Network SNF billing reference (MLN006846, January 2026)).
| UB-04 field | What goes there | Detail |
|---|---|---|
| Type of bill (FL 04) | 21X for SNF inpatient services | 18X is for swing bed services |
| Statement covers period (FL 06) | From and through dates | From date is the admission date, or the day after the prior through date |
| Occurrence span code 70 (FL 35-36) | Dates of the 3-day qualifying hospital stay | Required to show the stay was met |
| Revenue code (FL 42) | 0022 for SNF PPS | Total charges (FL 47) are zero on 0022 lines |
| HIPPS rate code (FL 44) and units (FL 46) | The rate code and covered days for each code | Reported in the order the level of care was received |
| Diagnoses (FL 67 and 67A-67Q) | ICD-10-CM principal and other diagnosis codes | Include all applicable diagnoses |
Source: CMS Medicare Learning Network, SNF billing reference MLN006846 (January 2026); Medicare Claims Processing Manual, Chapter 6, sections 30 and 40
How often to bill
SNFs send claims monthly and in sequence, and also when the resident is discharged, drops from skilled care or exhausts the benefit period. Each bill’s from date must be the day after the previous bill’s through date, and admissions that span October 1 need separate bills for each federal fiscal year (Medicare Claims Processing Manual, Chapter 6, sections 30 and 40). The CMS reference adds a short warning: Medicare will not pay under the SNF PPS unless you bill a covered day.
Corrections have a clock
If an assessment is corrected and the rate code changes, the adjustment must be submitted within 120 days of the through date on the bill, with condition code D2. CMS expects most corrections during the Part A stay and says providers who routinely correct after the stay ends may face focused medical review (Chapter 6, section 30.3).
Timely filing is a separate limit that this guide does not state. Confirm it with your MAC. For general claim-submission steps, see our overview of medical billing services, which covers claim preparation and charge entry for facilities and practices.
PDPM and what replaced RUG rates
The Patient Driven Payment Model (PDPM) pays SNFs for Medicare Part A stays. CMS finalized it in July 2018 and it took effect October 1, 2019, replacing the RUG-IV system (Noridian Medicare). Any article that explains SNF payment through RUG groups, ADL score bands and per-day RUG dollar tables describes a retired system.
PDPM has five case-mix adjusted components plus a variable per diem adjustment, and a fixed non-case-mix component. Each case-mix component pays a base rate times a case-mix index for the resident, and the per diem adjustment changes the rate as the stay goes on.
| Component | How it is calculated | Notes |
|---|---|---|
| Physical therapy (PT) | PT base rate x PT case-mix index x VPD factor | Variable per diem (VPD) adjustment applies |
| Occupational therapy (OT) | OT base rate x OT case-mix index x VPD factor | VPD adjustment applies |
| Speech-language pathology (SLP) | SLP base rate x SLP case-mix index | No VPD factor listed |
| Nursing | Nursing base rate x nursing case-mix index | An 18% adjustment factor applies only to residents with HIV/AIDS |
| Non-therapy ancillary (NTA) | NTA base rate x NTA case-mix index x VPD factor | VPD adjustment applies |
| Non-case-mix | A fixed non-case-mix base rate | Not tied to the resident’s case-mix index |
Source: Noridian Medicare, SNF PDPM page (CMS-published formulas, page updated June 2025)
The old advice to “optimize your RUG rate” does not translate. Under PDPM the case-mix groups come from the assessment, so accuracy and completeness of the assessment matter more than any billing-office tactic. Our separate piece on the impact of PDPM on SNF billing goes further into the model.
“If a payment group cannot be traced back to the assessment, it is not ready to bill.”
The MDS: where the claim starts
The Minimum Data Set (MDS) is the resident assessment data that facilities submit, and under PDPM it is the source for the rate code on a claim. Chapter 6 ties the HIPPS code to the assessment and says a change to that code after an MDS correction needs condition code D2 on the adjustment (Medicare Claims Processing Manual, Chapter 6, section 30.3).
What each MDS assessment type is, how many are required and when each is due are set in the CMS Resident Assessment Instrument (RAI) Manual and Chapter 6, section 30. Older summaries often blur two different purposes of the MDS, the care-planning assessments and the payment assessments. Rather than repeat a rule of thumb, have your MDS coordinator confirm the schedule against the current RAI Manual.
The MDS also feeds quality reporting. In the FY 2027 final rule, CMS finalized that all SNFs must submit MDS data for all residents receiving covered skilled care, regardless of payer (CMS fact sheet on the FY 2027 SNF final rule).
Billing cannot fix a weak assessment
A billing team can check that an assessment was accepted, that dates line up and that the HIPPS code on the claim matches the validation report. It cannot decide the clinical answers inside the MDS. Keep that boundary clear between the MDS coordinator, clinical leaders and billing.
Consolidated billing: the SNF bills for most services
Under SNF consolidated billing, the facility itself must submit all Medicare claims for the services its residents receive during a covered Part A stay, except for specifically excluded services (CMS).
In practice, an outside supplier or provider cannot bill Medicare Part B directly for a service that falls under consolidated billing. It must look to the SNF for payment. That means the facility needs a clear process for agreements, invoices and reconciliation with those suppliers.
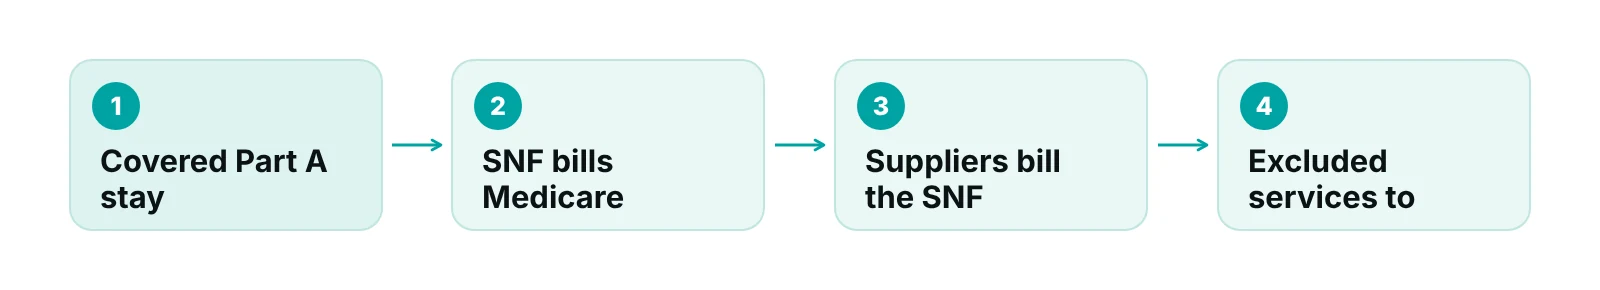
CMS lists exclusions that stay separately billable to Part B, including physician professional services; services of nurse practitioners, physician assistants and certain other practitioners; hospice care related to the terminal condition; and certain outpatient hospital services such as emergency services, CT and MRI scans and radiation therapy. Claims for excluded services must include the SNF’s Medicare provider number. Therapy remains subject to consolidated billing regardless of whether the resident is in a covered Part A stay.
The excluded list is long and changes. Check the current CMS consolidated billing page and code lists each year rather than relying on a summary. For unpaid or short-paid claims in a post-acute setting, our guides to medical billing denial management and accounts receivable follow-up apply to institutional claims too.
What changed for fiscal year 2027
CMS issued the FY 2027 SNF PPS final rule on July 29, 2026. It raises rates by 2.4%, which is a 3.3% market basket update less a 0.9% productivity adjustment, for an estimated $882.74 million in aggregate payments (CMS fact sheet on the FY 2027 SNF final rule). Federal fiscal years begin October 1, which is why admissions that span that date need separate bills.
- PDPM: CMS issued a Request for Information on updating PDPM and addressing observed case-mix upcoding. No changes were finalized.
- Quality reporting: two COVID-19 measures are removed starting with the FY 2028 SNF QRP, and the data submission window shortens from 4.5 months to about 45 days starting with the FY 2029 QRP.
- Value-based purchasing: performance standards were finalized for FY 2029 and FY 2030, and CMS estimates a $203.60 million reduction in FY 2027 for SNFs subject to net payment reductions.
Read the fact sheet and the final rule itself before you change a workflow. Rates and wage-index tables are published with the rule and differ by facility location.
A practical SNF billing workflow and where it breaks
Most SNF billing problems are sequence and data problems, not coding puzzles. A claim fails when the qualifying stay is not documented, the assessment is not accepted, the bill is out of sequence or no covered day was billed. The geriatrics and long-term care billing workload is also different from outpatient work; see how RCM Finder frames it on our geriatrics billing page.
- Admission: record the qualifying hospital stay dates and the payer, and note whether the plan waives the 3-day rule.
- Assessment: confirm acceptance in the state database before the first billable claim.
- Claim build: match type of bill, covered days, HIPPS code and occurrence span code 70 to the record.
- Monthly cycle: bill in sequence; split claims at October 1; bill on discharge, drop from skilled care or benefit exhaustion.
- Corrections: track the 120-day window and the D2 condition code.
- Suppliers: reconcile consolidated-billing invoices against what you billed.
A practice management system that tracks claims by stage helps here because every claim has an owner and a stage, with checks for missing data before submission. Do not rely on any tool to decide clinical or assessment questions.
Want a second look at your SNF claim workflow?
We review how claims move from admission to payment and flag where sequence, dates or follow-up break down. Pricing, if you want help afterward, is quoted after the audit.
Our recommendations
- Retire every RUG-based tool. Remove RUG tables, ADL bands and per-day rate sheets from training material and checklists. They describe a system that ended on October 1, 2019.
- Make assessment acceptance a hard stop. Do not release a first claim until the assessment shows as accepted and the HIPPS code matches the validation report.
- Keep one calendar for dates. Track the 3-day stay, the 30-day transfer window, benefit-period days, the October 1 split and the 120-day correction window in one place.
- Write down your consolidated billing process. List who approves supplier invoices, how they are matched to the stay and who checks the current CMS exclusion list each year.
- Verify the payer, not just Medicare. Medicare Advantage and Medicaid plans may waive or change rules. Record the payer’s own policy at admission.
- Update coinsurance figures every January. Resident notices and family conversations should use the current year’s amounts from Medicare.gov, not last year’s.
Track every SNF claim by stage and owner.
The RCM Finder portal tracks each claim by stage with an owner and checks for missing data before submission. It does not make assessment or clinical decisions.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
SNF billing comes down to a short chain: a qualifying stay, an accepted assessment, a correct HIPPS code and a monthly claim sent in sequence. If your team is stretched, review how your accounts receivable follow-up works for institutional claims, and use the revenue calculator to size what slow payment costs you. A free practice audit shows where the chain breaks.
Frequently asked questions
How often do skilled nursing facilities bill Medicare Part A?
SNFs send Part A claims monthly and in sequence. They also bill when a resident is discharged, drops from skilled care or exhausts the benefit period. Each bill’s from date must be the day after the previous through date, and stays that cross October 1 need separate bills for each federal fiscal year.
Which claim form does an SNF use for Medicare?
Medicare Part A claims go to the MAC as an 837 institutional electronic claim or on Form CMS-1450, which uses the UB-04 data set. Type of bill 21X is used for SNF inpatient services and 18X for swing beds. The CMS-1450 here is a Medicare form, not a Medicaid one.
How many days does Medicare cover in a skilled nursing facility?
Up to 100 days per benefit period, after a qualifying hospital stay of at least three days in a row. In 2026 Medicare.gov lists $0 per day for days 1 to 20 after the Part A deductible, $217 per day for days 21 to 100, and all costs after day 100. Amounts change every year.
Are RUG rates still used for SNF billing?
No. The Patient Driven Payment Model replaced RUG-IV for Medicare Part A SNF payment on October 1, 2019. PDPM pays through five case-mix components, a variable per diem adjustment and a non-case-mix component, so RUG tables and ADL bands in older articles are out of date.
What does the MDS have to do with SNF billing?
The MDS is the assessment data behind the rate code on a Medicare claim. The facility may bill only after the assessment is accepted in the state database, and a corrected assessment that changes the HIPPS code needs condition code D2 on an adjustment filed within 120 days of the through date.
Do Medicare Advantage plans follow the same SNF rules?
Not always. CMS says Medicare Advantage plans, 1876 Cost plans, PACE plans and certain ACO-affiliated SNFs may waive the 3-day hospital stay requirement, and Medicare.gov says Advantage plans may charge copayments in the first 20 days. Check each plan’s own policy before admitting a resident.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Skilled nursing facility care — Medicare.gov (2026)
- Skilled Nursing Facility Billing Reference (MLN006846) — CMS Medicare Learning Network (2026)
- Medicare Claims Processing Manual, Chapter 6 — CMS (2020)
- Skilled Nursing Facility (SNF) PDPM — Noridian Medicare (2025)
- SNF Consolidated Billing — CMS (2026)
- FY 2027 SNF PPS Final Rule (CMS-1843-F) fact sheet — CMS (2026)
Disclaimer: This article is educational and is not legal, coding or compliance advice. Medicare rules, rates and payer policies change, and Medicaid and commercial plans differ. Confirm current requirements with CMS, your Medicare Administrative Contractor and your compliance counsel before billing.
