
Use POS 10 telehealth coding when the patient is at home during a real-time telehealth visit, and POS 02 when the patient is anywhere else. For services on dates on or after January 1, 2024, Medicare pays POS 10 at the non-facility rate and POS 02 at the facility rate. Modifiers 93 and 95 do not change that rate.
The place of service (POS) code is one of the few telehealth fields that moves the payment, not just the paperwork. A wrong choice can mean a short payment that nobody notices, or a denial that someone has to rework. This guide covers what POS 10 means, how to choose between it and POS 02, how Medicare pays it, and what to check before the claim goes out. For the full picture of telehealth coding, see our telehealth billing guide; for modifier choices, see the telehealth modifiers guide. We do not repeat either here.
Key takeaways
- POS 10 means telehealth provided in the patient’s home. POS 02 means telehealth provided somewhere other than the patient’s home.
- Since January 1, 2024, Medicare pays covered telehealth services billed with POS 10 at the non-facility rate and POS 02 at the facility rate.
- Modifiers 93 and 95 describe the technology. For Medicare they do not change the payment rate; the POS code does.
- Medicare’s home-based flexibilities for non-behavioral care run through December 31, 2027. Behavioral and mental health care at home is permanent.
- Medicaid and commercial plans can treat home telehealth differently, so keep a one-page rule sheet per payer.
What POS 10 means on a telehealth claim
POS 10 is the place of service code for telehealth provided in the patient’s home. In the CMS code set, the home is a private residence, not a hospital or other facility. POS 10 took effect on January 1, 2022, and CMS told Medicare contractors to start recognizing it on April 4, 2022 (CMS Transmittal 11437). It is the home-based counterpart to POS 02, which covers telehealth when the patient is not in their home.
The code describes where the patient was during the visit. That is the question your billing team has to answer for every telehealth claim, and the answer has to come from the visit record, not from habit.
At launch, CMS instructed contractors to process POS 10 claims with the same business rules used for POS 02 (CMS Transmittal 11437). That changed for 2024, which is covered below. If you have older notes saying the two codes pay alike, they describe the 2022 and 2023 setup.
POS tells the payer where. The modifier tells the payer how.
Place of service says where the patient was. A modifier such as 95 or 93 says whether the visit used audio and video or audio only. A telehealth claim often needs both, depending on the payer. The modifier rules sit in the telehealth modifiers guide; this page stays on the POS decision. Our modifier 95 guide covers that one modifier in more depth.
POS 10 vs POS 02: how to choose
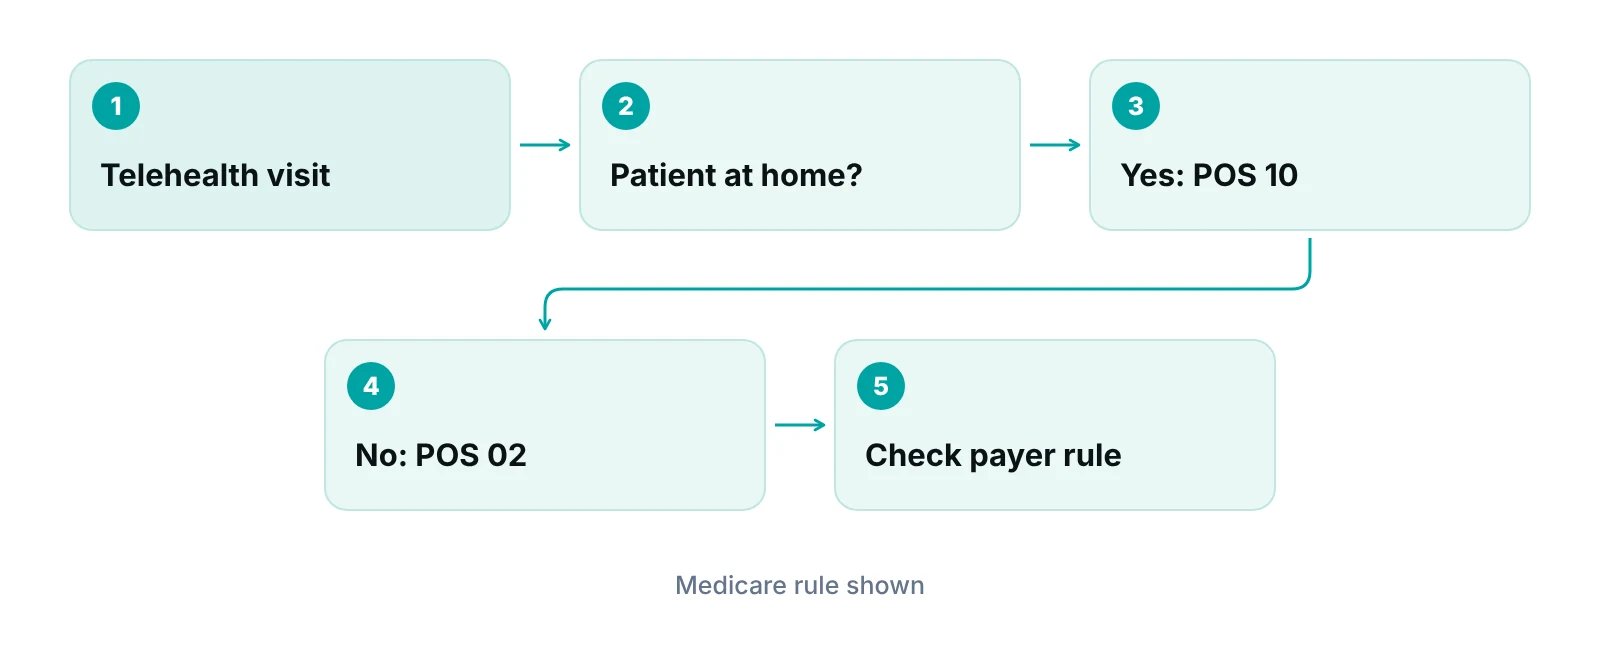
Choose by the patient’s location at the moment of the visit. If the patient was in their home, use POS 10. If the patient was in any other place, such as a clinic, another practice’s exam room or a hospital, use POS 02. The table sets out the two codes next to the in-person office code.
| POS code | Name | Where the patient is | How Medicare pays it (dates of service from Jan 1, 2024) |
|---|---|---|---|
| 10 | Telehealth Provided in Patient’s Home | In a private residence | Non-facility Medicare Physician Fee Schedule rate |
| 02 | Telehealth Provided Other than in Patient’s Home | Anywhere other than their home | Facility rate |
| 11 | Office (in-person visit) | At the practice’s office | Not a telehealth code; paid under in-person office rules |
Source: CMS Transmittal 12671, Billing and Payment for Telehealth Services with Place of Service (POS) 10 (June 6, 2024); CMS Transmittal 11437 (May 27, 2022).
If you need the wider POS picture, our POS code guide compares the office and hospital outpatient codes, and the POS 11 guide covers the in-person office code.
Common scenarios
Staff usually get the clear cases right and miss the edges. The table lists the cases that come up at the front desk.
| Situation | POS to use | Note |
|---|---|---|
| Patient joins the video visit from their own house or apartment | 10 | The standard POS 10 case |
| Patient joins from a rural health clinic or another provider’s office | 02 | The patient is not at home |
| Patient joins from a hospital room | 02 | CMS defines home as a place other than a hospital or other facility |
| Patient joins from work, a car or a public place | 02 | Not a home |
| Patient lives in an assisted living facility or group home | Check first | The CMS descriptor says private residence; ask your MAC or the payer how it treats this setting |
| Patient was home at the start but moved before the visit ended | Document it | Record where the patient was and choose from the note |
Source: CMS Transmittal 11437 (May 27, 2022) for the POS 02 and POS 10 descriptors. Situations are examples, not CMS rulings.
How Medicare pays POS 10 claims
Medicare pays covered telehealth services billed with POS 10 at the Medicare Physician Fee Schedule non-facility rate. This applies to dates of service on or after January 1, 2024. CMS issued the instruction in Transmittal 12671 on June 6, 2024, and contractors implemented it on July 8, 2024 (CMS Transmittal 12671). Claims for POS 02 are paid at the facility rate under the same transmittal.
Two points matter for practice managers. First, the rate follows the POS code, not the modifier. CMS states that modifier 93 (audio-only) and modifier 95 (audio and video) do not change the payment rate; only the POS code decides whether the facility or non-facility rate applies. Second, this is a rule for Medicare. It does not bind Medicaid or commercial plans.
Do not budget from an average
Fee schedule amounts are set code by code, and facility and non-facility rates differ by code. Older articles that quote one average dollar figure for telehealth or for the facility setting are not a reliable guide. Look up the codes you actually bill in the CMS Physician Fee Schedule look-up tool for your locality and year.
Timeline: how the POS 10 rules developed
| Date | What happened | Why it matters |
|---|---|---|
| January 1, 2022 | POS 10 becomes effective in the CMS code set | Home telehealth gets its own code |
| April 4, 2022 | CMS contractors implement the POS 10 and POS 02 changes | Contractors process POS 10 with the same business rules as POS 02 |
| January 1, 2024 | Medicare pays POS 10 at the non-facility rate for covered telehealth services | Rate now depends on POS 10 vs POS 02 |
| June 6, 2024 | CMS issues Transmittal 12671 (Change Request 13582) | Manual instructions updated for billing and payment |
| July 8, 2024 | Implementation date of Transmittal 12671 | Systems and contractors apply the instruction |
| December 31, 2027 | Current end date for Medicare’s non-behavioral home telehealth flexibilities | Plan for it now; see the next section |
Sources: CMS Transmittal 11437 (2022); CMS Transmittal 12671 (2024); HHS Telehealth.HHS.gov telehealth policy updates (page updated February 5, 2026).
“A place of service code is cheapest to get right at check-in and most expensive to fix after a denial.”
What is still in flux for 2026 and 2027
Medicare’s home-based telehealth rules depend on temporary extensions, so check the end dates. According to HHS telehealth policy updates (last updated February 5, 2026), non-behavioral telehealth care at home is covered through December 31, 2027, and audio-only platforms can be used for non-behavioral services through the same date. The same page says Medicare patients can permanently receive telehealth for behavioral and mental health care in their home, and that behavioral and mental services can permanently use audio-only communication.
That split matters for POS 10 because the code is about the patient’s home. For behavioral and mental health, the home setting is permanent. For most other care, the home setting is time-limited unless Congress acts again.
- Home as the patient’s location (non-behavioral): covered through December 31, 2027.
- Audio-only (non-behavioral): allowed through December 31, 2027.
- Behavioral and mental health at home: permanent, including audio-only delivery.
- In-person visit requirement for mental health telehealth: not required through December 31, 2027, per the same HHS page.
CMS also made two changes in its 2026 fee schedule final rule. It removed the split between provisional and permanent telehealth services, so its review now asks whether a service can be furnished using an interactive two-way audio-video system. It also added services to the Medicare Telehealth Services List (CMS CY 2026 fee schedule final rule summary). Check the current list for each code before you bill it from home.
Practices that bill therapy and counseling by telehealth feel this most. Our behavioral and mental health billing page describes how those revenue cycles are usually organized.
Claim and documentation checks before you bill
Most POS 10 problems are data problems: the wrong code, a missing modifier, or a note that does not show where the patient was. A short check at the point of charge entry catches most of them.
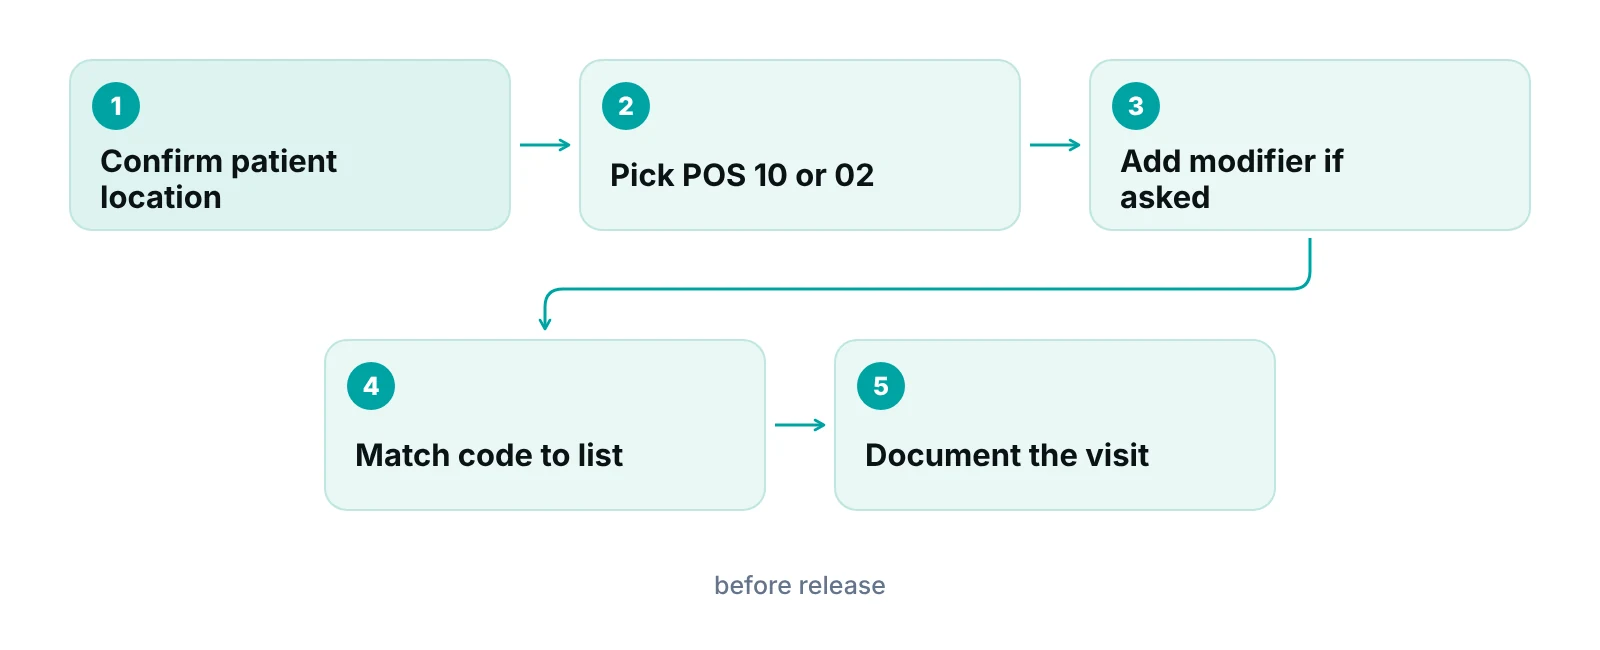
- Confirm the patient’s location. Record in the note where the patient was during the visit. Do not leave it to the biller to guess.
- Pick POS 10 or POS 02 from that note. A home visit is POS 10; any other location is POS 02.
- Add the modifier the payer expects. Medicare and other payers differ here, so follow the telehealth modifiers guide and each payer’s policy.
- Check that the service is covered by telehealth. The Medicare Telehealth Services List decides whether a code can be billed by telehealth at all.
- Keep the same documentation you would for an in-person visit, plus the technology used (video or audio only), the date and the patient’s location.
We recommend building these five items into the visit template so they are captured during care rather than reconstructed at billing.
Not sure where your telehealth claims are slipping?
Our free practice audit looks at a sample of your telehealth claims and shows where place of service, modifier or documentation gaps may be causing short payments or denials.
Where POS 10 claims go wrong
A POS 10 claim usually fails for one of four reasons. None of them is exotic, and each can be tested for in your own claims data.
- POS 02 used for a home visit, or the reverse. This mismatch can change the payment on Medicare claims.
- Wrong or missing modifier. A payer that expects 95 or 93 may reject or reprice a claim that leaves it off.
- Service not on the telehealth list. The code is billable in person but not by telehealth, or not from home.
- Note does not show the patient’s location or the technology used. Without it, an auditor cannot support the POS.
When these show up as denials, work them by pattern, not claim by claim. Our denial management guide explains how to group and trend denial reasons, and the clean claims guide covers edits that catch errors before submission. If you would rather hand the rework to a team, see our denial management services.
See what a coding error can cost
Use the revenue calculator to estimate how much a small share of short-paid or denied claims adds up to over a year.
Medicaid and commercial plans: do not assume Medicare rules
Medicare’s POS 10 payment rule applies to Medicare. Medicaid programs and commercial plans publish their own policies, and they can differ on which POS they accept, which modifiers they require and whether home telehealth pays the same as an office visit. Treat each plan as a separate rule set.
A practical approach is a one-page sheet for each of your top payers. It lists the POS code accepted for home telehealth, the modifier for video and for audio-only, the covered codes, and the date someone last checked. Revisit the sheet when a payer bulletin arrives and at the start of each year.
If your billing team is stretched, this kind of rule tracking is part of what an outsourced team does. Our medical billing services include claim submission and coding support, and you can compare options before deciding.
Our recommendations
- Make patient location a required field. We recommend a required field in the visit note for where the patient was, so POS 10 or POS 02 can be chosen from the record.
- Set the default POS by rule, not by clinician. Have the charge entry team assign POS from the location field. Letting each clinician pick leads to mixed coding for the same type of visit.
- Check Medicare rates for your codes. Pull the non-facility and facility amounts for your top telehealth codes from the fee schedule and see what a wrong POS would cost on each.
- Calendar the 2027 end date. Home-based flexibilities for non-behavioral care are listed through December 31, 2027. Review your telehealth mix well ahead of that date.
- Keep one payer rule sheet per plan. List the POS, modifier and covered codes for each major payer, with a last-checked date.
- Report denials by POS and modifier. Add POS and modifier to your denial report so patterns show up in the data.
Bottom line
POS 10 is simple to define and easy to get wrong: the patient at home takes POS 10, the patient anywhere else takes POS 02, and Medicare pays the two differently. Confirm the patient’s location at the visit, check the modifier rule for each payer, and track the December 31, 2027 end date for non-behavioral home care. If telehealth claims are being short-paid or denied, our medical billing services and denial management services can review them, or you can contact our team.
Frequently asked questions
What is POS 10 in medical billing?
POS 10 is the place of service code for telehealth provided in the patient’s home. CMS describes the home as a private residence rather than a hospital or other facility. The code took effect on January 1, 2022. It tells the payer where the patient was during the visit, not how the visit was delivered.
When should I use POS 10 instead of POS 02?
Use POS 10 when the patient is at home during the telehealth visit. Use POS 02 when the patient is somewhere other than their home, such as a clinic or hospital. Choose from the visit note. For unusual settings such as assisted living, ask your MAC or the payer how it treats the setting.
Does Medicare pay POS 10 the same as an office visit?
For services on dates on or after January 1, 2024, Medicare pays covered telehealth services billed with POS 10 at the non-facility Physician Fee Schedule rate. Payment is still set code by code, so look up the codes you bill. Do not assume it equals every in-person amount.
Do modifiers 93 or 95 change the rate for POS 10 or POS 02?
For Medicare, no. CMS states that modifier 93 (audio-only) and modifier 95 (audio and video) do not change the payment rate. The POS code decides whether the facility or non-facility rate applies. Other payers may use the modifiers differently, so check each payer’s policy.
Can I bill audio-only visits from the patient's home?
Under the HHS telehealth policy page, Medicare allows audio-only for non-behavioral services through December 31, 2027, and allows audio-only permanently for behavioral and mental health services. Whether a particular code qualifies, and what modifier to add, depends on the code and the payer, so verify it before billing.
Do Medicaid and commercial plans follow the Medicare POS 10 rule?
Not automatically. Medicaid programs and commercial plans set their own telehealth policies for place of service, modifiers and payment. Confirm each plan’s current policy for the date of service, and record what you find on a per-payer rule sheet your billing team can reuse.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- CMS Transmittal 11437: New/Modifications to the Place of Service (POS) Codes for Telehealth — CMS (2022)
- CMS Transmittal 12671: Billing and Payment for Telehealth Services with Place of Service (POS) 10 — CMS (2024)
- Transmittal R12671CP summary page — CMS (2024)
- Telehealth policy updates (Medicare) — HHS, Telehealth.HHS.gov (2026)
- Medicare Physician Fee Schedule final rule summary, CY 2026 (MM14315) — CMS (2025)
Disclaimer: This article is educational. It is not legal, coding or compliance advice. CPT is owned by the AMA, and payer and state rules vary and change, so confirm each rule with your MAC and each payer before billing.
