
Modifier 25 vs 59 comes down to what you are separating. Modifier 25 marks a significant, separately identifiable E/M visit on the same day as a procedure. Modifier 59 marks a distinct non-E/M service that a coding edit would otherwise bundle. CMS prefers the more specific XE, XS, XP or XU when one fits.
These two modifiers get mixed up because both tell a payer “count this separately.” They do not work on the same kind of code, and they do not carry the same risk. This guide is the single place on our blog for both, and it also covers the X modifiers and a short note on modifier 91. It is based on the CMS MLN fact sheet on modifiers 59 and X{EPSU} (April 2026), the CMS NCCI Policy Manual and two Medicare contractor pages, not on unsourced denial statistics. A short comparison is below, then each modifier in turn.
Key takeaways
- Modifier 25 goes on an E/M code. Modifier 59 is never appended to an E/M service.
- Modifier 25 needs a significant, separately identifiable visit beyond the decision to do the procedure, shown in the note.
- Use an established modifier (24, 25, 57, 58, RT, LT and others) before 59 when it fits.
- XE, XS, XP and XU say why services were distinct. CMS says to use them instead of 59 whenever possible.
- A different diagnosis alone does not justify 59, XE, XP, XS or XU.
What is the difference between modifier 25 and modifier 59?
Modifier 25 is for evaluation and management (E/M) services. Modifier 59 is for everything except E/M. The CMS fact sheet states it directly: modifier 59 “should not be appended to an E/M service,” and a separate E/M service reported with a non-E/M service on the same date is the job of modifier 25 (CMS, 2026).
The second difference is what each one overrides. Modifier 25 tells the payer that a visit stands apart from a same-day procedure, so the visit is not folded into the procedure payment. Modifier 59 tells the payer that two procedures that an edit would normally pair were different enough to report together. CMS calls these paired-code checks National Correct Coding Initiative (NCCI) procedure-to-procedure edits. Their purpose is to stop payment for overlapping services unless the services are separate and distinct (HHS-hosted MLN summary).
| Modifier | What it separates | Reported on | The test in short |
|---|---|---|---|
| 25 | A same-day E/M visit from a procedure or other service | An E/M code | Significant and separately identifiable, supported by the note |
| 59 | One non-E/M service from another that is normally reported together | A non-E/M code | Different session, procedure, site or organ system, and no more specific modifier fits |
| XE, XS, XP, XU | The same as 59, with the reason named | A non-E/M code | Separate encounter, structure, practitioner, or non-overlapping service |
| 91 | A repeat clinical lab test on the same day | A lab test code | Needed to get subsequent reportable results, not a rerun |
Sources: CMS MLN fact sheet on modifiers 59 and X{EPSU} (April 2026); First Coast Service Options modifier 25 fact sheet (March 2026); Noridian modifier 91 page (May 2025).
Many claims need neither. If no edit pairs the codes and no same-day visit stands apart from a procedure, a modifier only adds audit risk.
When is modifier 25 correct?
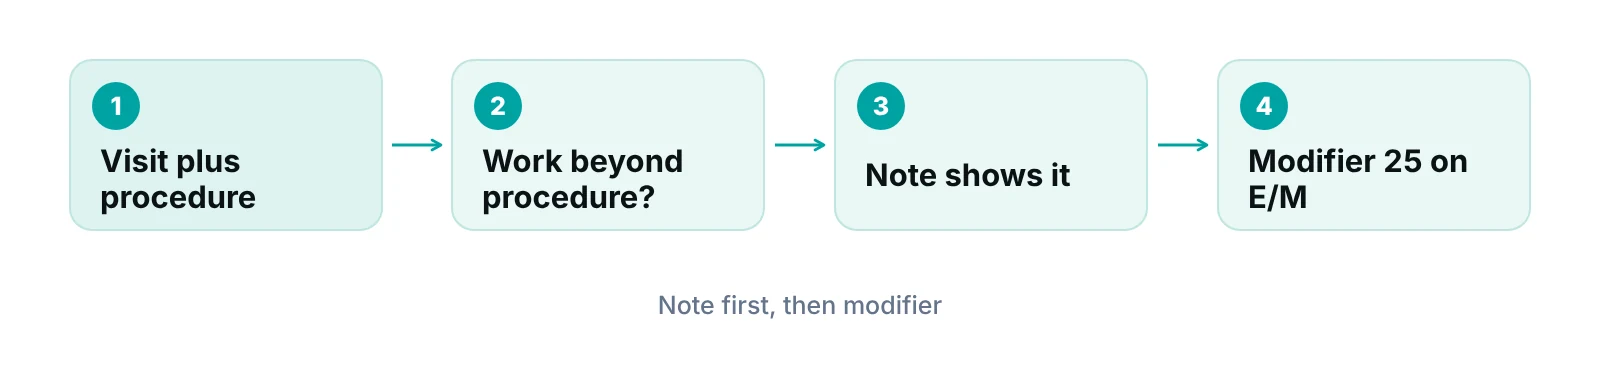
Modifier 25 is correct when the same clinician performs a significant, separately identifiable E/M service on the same day as a procedure or other service, and the note supports it. Medicare contractor guidance says payment is allowed when the documentation supports the modifier, and not when it does not (First Coast Service Options, March 2026).
Why a minor procedure is where it matters
A procedure with a global period of 0 or 10 days is a minor surgical procedure under Medicare policy. Under that policy, E/M services on the same date are included in the procedure payment, and so is the decision to perform the minor procedure. What can be reported separately is a significant and separately identifiable E/M service unrelated to that decision, with modifier 25 (CMS NCCI Policy Manual for Medicare Services, edition revised 1/1/2022).
In plain terms, the evaluation that leads to the decision to do the procedure is part of the procedure payment. A full evaluation of a different complaint is not. Specialties that do minor procedures during visits, such as dermatology, need this line drawn clearly, and a dermatology billing and revenue cycle team works with it daily.
Rules that trip up modifier 25 claims
- Do not use modifier 25 with CPT 99211, per the contractor fact sheet.
- If the visit leads to the decision to do a major procedure (a 90-day global), the E/M is reported with modifier 57, not 25 (NCCI manual).
- Follow-up care related to a prior surgery during its global period is included in that surgery. An unrelated E/M for a new problem in that period uses modifier 24 (contractor fact sheet).
- Physicians of the same specialty in the same group are treated as one physician for this rule.
- For dates of service on or after January 1, 2025, the add-on G2211 can be paid with an office or outpatient E/M reported with modifier 25 only when a listed Medicare Part B preventive service, immunization administration or annual wellness visit is also on the claim. Otherwise the claim denies (contractor fact sheet, March 2026).
If you want to see how level selection works once the visit is separate, our guide to the 99213 CPT code walks through it.
“A modifier does not make a service payable. It points the payer to the part of the record that already proves the service stood on its own.”
When is modifier 59 correct, and when is it misuse?
Modifier 59 is correct only when documentation supports a different session, different procedure or surgery, different site or organ system, separate incision, lesion or injury, and no more descriptive modifier is available. CMS says modifier 59 should not be used when another established modifier fits, and that the modifier is for situations where its use best explains the circumstances (CMS MLN fact sheet on modifiers 59 and X{EPSU} (April 2026)).
It is also not a code. It is a modifier added to a procedure code.
What the NCCI edit is checking
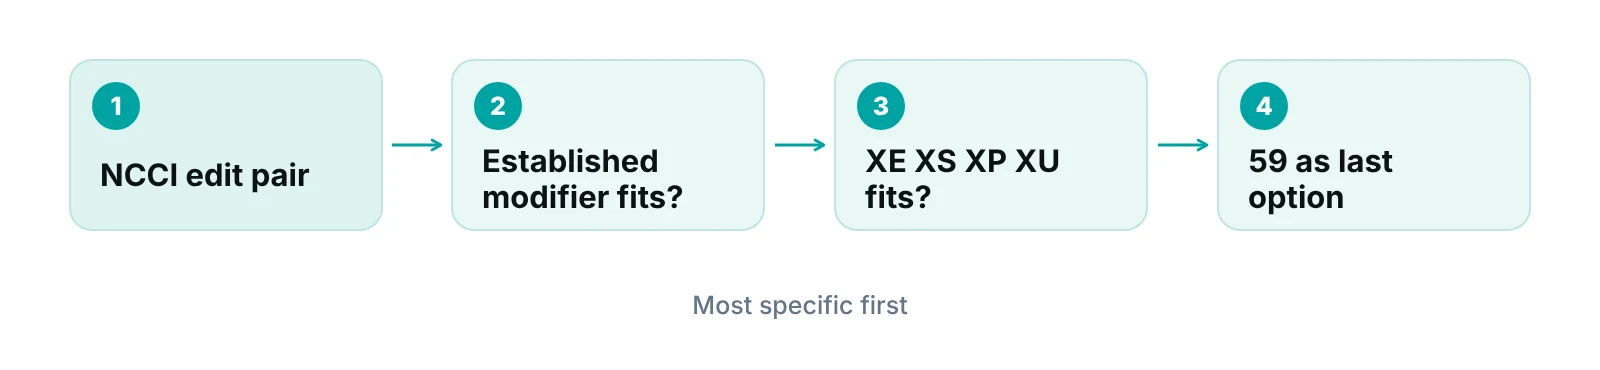
Each NCCI procedure-to-procedure edit pair carries a modifier indicator. CMS describes an indicator of “0” as codes you do not report together by the same provider. An indicator of “1” means you report the codes together only in limited circumstances, by using an NCCI-associated modifier such as 59 or an X modifier. If the pair is not one that allows a modifier, no modifier can fix it.
What does not justify modifier 59
- Different diagnoses alone. CMS says different diagnoses are not adequate criteria for 59, XE, XP, XS or XU. The service must also be distinct.
- Different code descriptors. CMS says not to use 59 or XU just because the descriptors of two codes differ.
- A software prompt. A scrubber or an edit report can flag a pair. Only the note can show it was distinct.
- An E/M service. Use modifier 25 for that.
A new diagnosis is therefore not required, and a new diagnosis is not enough. The test is whether the services were truly separate, and whether the note proves it.
Diagnostic and timed services
CMS gives extra conditions for two situations. A diagnostic service before a therapeutic one qualifies for 59 or XU only if the diagnostic service is the basis for the decision to do the therapeutic one. A diagnostic service after a therapeutic one qualifies only if it is not a common, expected or necessary follow-up. Timed services performed one after another in separate, non-overlapping blocks can use 59 or XE (CMS MLN fact sheet on modifiers 59 and X{EPSU} (April 2026)).
What are the XE, XS, XP and XU modifiers?
XE, XS, XP and XU are modifiers that give greater reporting specificity in situations where you previously used 59. Each names the reason the service was distinct. CMS says they should be used instead of modifier 59 whenever possible, and that Medicare allows modifiers 59, XE, XP, XS or XU on Column 1 or Column 2 codes (CMS MLN fact sheet on modifiers 59 and X{EPSU} (April 2026)).
| Modifier | Reason it states | When it fits | What the note should show |
|---|---|---|---|
| XE | Separate encounter | Services on the same day in different patient encounters, when a more specific modifier such as 24, 25, 57 or 58 does not fit | A distinct encounter, with its own time and reason |
| XS | Separate structure | Different organ or structure, or a different anatomic site, when no more specific anatomic modifier applies | The site or organ for each service |
| XP | Separate practitioner | Service performed by a different practitioner | Who performed each service |
| XU | Unusual non-overlapping service | A service that does not overlap the usual components of the main service | Why it was not part of the main service |
Source: CMS MLN fact sheet on modifiers 59 and X{EPSU} (April 2026). Wording paraphrased; check the current CPT and HCPCS manuals for official descriptors.
For different anatomic sites in the same encounter, CMS says 59 or XS applies only if a more specific anatomic modifier, such as RT, LT or F1 to F9, does not. The same fact sheet says the X modifiers, like 59, must be backed by documentation.
Payers do not all follow Medicare
The CMS fact sheet addresses Medicare only. A commercial or Medicaid plan may accept only 59, only the X modifiers, or may set its own rules for either. Check each payer’s published modifier policy and keep a short internal list so the biller does not guess.
Where does modifier 91 fit?
Modifier 91 is separate from both. It is for a repeat clinical diagnostic laboratory test on the same day that is needed to obtain subsequent reportable test values. A Medicare contractor says it may not be used to rerun a test to confirm the first result, or because of a specimen or equipment problem, or when a standard code already describes the series of results, such as a glucose tolerance test (Noridian Healthcare Solutions, May 2025).
For code-level lab examples, see our modifier 91 guide, and for lab billing in general our laboratory billing and coding guide.
Which modifier fits which situation?
Match the modifier to what is being separated, then confirm the more specific option does not apply. The table below turns the CMS and contractor rules above into a quick check. It is a guide, not a substitute for payer policy.
| Situation | Consider | Why | Check before billing |
|---|---|---|---|
| Separate evaluation of a different problem on the day of a minor procedure | 25 on the E/M | The visit goes beyond the decision to do the procedure | Note shows the extra work |
| Visit leads to the decision for a major procedure | 57 on the E/M | Major procedures follow a different rule than minor ones | Global period of the procedure |
| Unrelated E/M for a new problem during a prior surgery’s global period | 24 on the E/M | Related follow-up care is included in the surgery | Problem is not part of recovery |
| Two procedures paired by an edit, done on separate organs or sites | XS (or 59) | Separate structure | Edit allows a modifier; no RT, LT or F1 to F9 fits |
| Same two services in two separate encounters on one day | XE (or 59) | Separate encounter | Each encounter is documented on its own |
| Service performed by a different practitioner | XP (or 59) | Separate practitioner | Payer accepts XP |
| A service that does not overlap the main service’s usual components | XU (or 59) | Unusual non-overlapping service | Not a common or expected part of the main service |
| Same lab test repeated to get subsequent values | 91 | Needed for additional reportable results | Not a rerun for error or confirmation |
Sources: CMS MLN fact sheet on modifiers 59 and X{EPSU} (April 2026); CMS NCCI Policy Manual (edition revised 1/1/2022); First Coast Service Options (March 2026); Noridian (May 2025).
Two common examples are weaker than they look. Treating a cut and removing a mole in one visit is only a 59 question if an NCCI edit pairs the two codes. A fever evaluated before a minor surgery is only a 25 question if the note shows work separate from the decision to operate.
How do you keep 25 and 59 from becoming denials or audit findings?
Make the proof part of the note, then check the claim before it leaves the practice.
- Name the separation in the note. Write the site, session, encounter, practitioner or problem that makes the services distinct.
- Let the coder decide, not the software. Edit reports and scrubbers can suggest 59. The note decides whether it is true.
- Check the edit first. If the pair does not allow a modifier, change the coding or do not bill both.
- Use the most specific modifier. Prefer an established modifier, then an X modifier, then 59.
- Keep a payer list. Record which payers accept X modifiers and which require 59.
If a claim is denied for a bundling reason, read the remittance codes before resubmitting. Appending 59 to every denied line is the kind of habit that draws audits. If coder time is short, medical billing services can review modifier use before submission. Our claim scrubbing guide explains where edit checks sit, and our medical coding audits guide explains how to sample claims that carry modifiers.
A claim-tracking tool helps with the repeatable part. For example, a practice management system that tracks claims by stage can run data-completeness checks before submission and flag claims for review, so a modifier-bearing claim is looked at by a person before it goes out. It does not replace the coder’s judgment on whether the services were distinct.
Want a second set of eyes on your modifier use?
A free practice audit looks at how claims move from the visit note to payment and where bundling denials start. Pricing, if you go further, is quoted after the audit.
Modifier 79 is a different case, covered in our modifier 79 guide. If bundling denials are already a regular cost, the revenue calculator can help you size the problem before deciding what to change.
Our recommendations
- Start from the edit or the visit. We recommend asking two questions before any modifier: is an NCCI edit pairing these codes, or is a same-day visit separate from a procedure? If neither, leave the modifier off.
- Use the most specific modifier that is true. We recommend an established modifier first, then XE, XS, XP or XU, and 59 only if nothing more descriptive fits and the payer accepts it.
- Put the proof in the note. We recommend that clinicians write the session, site, structure or problem that makes the services distinct, in words a reviewer can find in seconds.
- Do not treat a diagnosis as the test. We recommend removing any internal rule that says a different diagnosis makes 59 or 25 safe. CMS says different diagnoses alone are not enough for 59 and the X modifiers.
- Keep a payer-by-payer modifier sheet. We recommend a one-page list of which payers accept X modifiers, which want 59, and which publish their own modifier 25 policy. Review it when payer bulletins arrive.
- Audit a sample of modifier claims. We recommend pulling a small sample of claims with 25 and 59 each quarter and checking each against the note.
A practice management system that tracks claims by stage can add a check before modifier claims go out.
Data-completeness checks before submission and workflow rules that flag a claim for review let a person look at a claim carrying a modifier before it is submitted. The portal does not decide whether services were distinct; that stays with the coder and the note.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Modifier 25 is for a separate visit on the day of a procedure. Modifier 59 and the X modifiers are for separate non-E/M services that an edit would bundle, with X modifiers preferred when they fit. Both stand or fall on the note. If your team is working through bundling denials, see our denial management services, or contact us to talk through your claims.
Frequently asked questions
Is a new diagnosis required to use modifier 59?
No. CMS says different diagnoses alone are not adequate criteria for 59, XE, XP, XS or XU. The services must be distinct, such as a different session, procedure, site or organ system, and the documentation must support it. A shared diagnosis does not automatically rule 59 out.
Can modifier 59 go on an E/M code?
No. CMS says modifier 59 should not be appended to an E/M service. A separate, distinct E/M on the same date as a non-E/M service is reported with modifier 25 when the note supports it.
Should I use 59 or XS, XE, XP, XU?
CMS says to use the X modifiers instead of 59 whenever possible, because they state the reason. Use 59 only when no more descriptive modifier is available. Check each payer, because not every plan accepts the X modifiers.
Do I need a different diagnosis to use modifier 25?
The test is the work, not the diagnosis field. The E/M must be significant and separately identifiable, and for a minor procedure it must be beyond the decision to do the procedure. Some payers also publish their own diagnosis rules, so check the policy.
Can I use modifier 25 with 99211?
A Medicare contractor fact sheet says not to use modifier 25 with CPT 99211. It also notes that for dates of service from January 1, 2025, G2211 with an E/M carrying modifier 25 is paid only when certain preventive services or an annual wellness visit are on the claim.
Can I repeat a lab test with modifier 91 if the first result looks wrong?
Not for a rerun. A Medicare contractor says modifier 91 may not be used to confirm a result or because of a specimen or equipment problem. It is for repeat tests needed to obtain subsequent reportable values on the same day.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Proper Use of Modifiers 59, XE, XP, XS and XU (MLN1783722) — CMS Medicare Learning Network (2026)
- MLN1783722 summary page — HHS guidance portal (CMS content) (2023)
- Modifier 25 fact sheet — First Coast Service Options (Medicare Administrative Contractor) (2026)
- Modifier 91 — Noridian Healthcare Solutions (Medicare Administrative Contractor) (2025)
- NCCI Policy Manual for Medicare Services (evaluation and management and global surgery sections) — CMS (2022)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT codes and modifier definitions are owned by the AMA, and CMS rules, payer policies and NCCI edits change and vary by payer. Verify current requirements with the current CPT manual, your payers and your compliance counsel before you act.
