

Ambulance billing services build and follow Medicare and payer claims from each transport record. Success depends on proving the trip was medically necessary, using the correct service level and mileage, and holding the right certification. CMS data show most Medicare ambulance errors are documentation problems, so fix run reports first.
If you run or bill for an ambulance service, you already know the claim is only as good as the crew’s paperwork. This guide explains how Medicare pays, what makes a trip billable, where claims fail, and how to choose between in-house, outsourced and hybrid billing. It is written for owners and billing managers, not patients.
Key takeaways
- Medicare pays a fee-schedule base rate plus loaded mileage, not your charge.
- A trip must be medically necessary and go between covered points.
- Documentation caused 63.5% of 2024 Medicare ambulance payment errors, per CMS.
- Certification rules depend on transport type and timing.
- Fix run reports and track claims by stage before deciding to outsource.
What do ambulance billing services actually do?
Ambulance billing services turn a transport run into a payable claim and then follow that claim until it is paid. The work starts with the run report and ends with posted payment, denial follow-up and patient statements. Most of the risk sits in the first step: whether the record proves the trip was needed.
Ambulance billing is not office-visit billing. There is no CPT visit code and no exam note to lean on. The claim is built from a crew’s patient care report, the pickup and drop-off points, the miles loaded, and the level of service the patient’s condition required.
- Run-report review: checking that the care report supports the level of service and the reason for transport before anything is billed.
- Claim build: service line, mileage line, origin and destination modifier, pickup ZIP code and diagnosis, all matched to the record.
- Certification and signature chase: getting physician or non-physician statements and patient or representative signatures where the rules call for them.
- Payer follow-up and appeals: working denials, resubmitting corrected claims and tracking unpaid balances.
- Patient billing: clear statements and a way for patients to ask questions.
This post explains how the money moves and where claims break, so you can decide how to run billing. For a deeper look at the code set and mileage, read our guide to ambulance billing codes and mileage. For short operational tips, see five tips for effective ambulance billing. Hospital emergency department work is a different claim type, covered in medical billing for emergency services.
Coding rules differ a lot between specialties, and ambulance is one of the least like the rest. Our specialty billing pages show how we group billing patterns for office-based specialties; ambulance needs its own checklist, which the rest of this post lays out.
How does Medicare pay for an ambulance trip?
Medicare pays ambulance transports from a national fee schedule, not from the provider’s charge. Each trip is paid as a base rate for the service level plus a separate amount for loaded miles, adjusted for where the patient was picked up.
According to the CMS ambulance fee schedule page, each service level carries a relative value unit (RVU), with basic life support (BLS) non-emergency set at 1.00 as the baseline. The base rate is a single national dollar amount, updated each year by the ambulance inflation factor. A geographic cost index is applied by pickup location, and each leg of a multi-vehicle transport is evaluated separately. The geographic index does not apply to mileage.
| Service level | Relative value unit | What it means for billing |
|---|---|---|
| BLS, non-emergency | 1.00 | The baseline; other levels are expressed against it |
| BLS, emergency | 1.60 | Emergency response is paid above the baseline |
| ALS2 | 2.75 | Higher level of care; must be supported by the care report |
| SCT (specialty care transport) | 3.25 | The highest of the four listed; needs clear clinical support |
Source: CMS, Ambulance Fee Schedule Public Use Files (CY 2026 page). The files are informational; Medicare Administrative Contractors keep the official files used to process claims.
Three temporary add-ons also apply to ground transports. Per the same CMS page, a 2% increase applies to base and mileage rates for urban pickups, 3% for rural pickups, and a 22.6% increase to the base rate for super-rural pickups. The Consolidated Appropriations Act, 2026 extended these through December 31, 2027; without further legislation they expire on January 1, 2028.
Part B deductible and coinsurance requirements apply to payments under the ambulance fee schedule, per the Medicare Claims Processing Manual, Chapter 15. The same chapter says payment for ambulance services is made only on an assignment-related basis, so the Medicare-allowed amount is what you accept for the trip.
What makes an ambulance transport billable?
A transport is billable to Medicare only when the patient’s condition requires both the ambulance trip and the level of service billed, and when the trip goes between covered points. Both tests have to be visible in the record, not just assumed.
Under 42 CFR 410.40, coverage requires that other means of transportation are contraindicated. A non-emergency transport qualifies in one of two ways: the patient is bed-confined and other transport is contraindicated, or the patient’s medical condition requires ambulance transport regardless of bed confinement. Bed confinement is one factor, not the sole test. A patient counts as bed-confined only if unable to get up from bed without assistance, unable to walk, and unable to sit in a chair or wheelchair.
Where the trip goes matters as much as why. The same regulation covers transport from any point of origin to the nearest hospital, critical access hospital, rural emergency hospital or skilled nursing facility that can provide the needed level of care. It also covers return trips from those facilities to the patient’s home, and trips for dialysis patients between home and the nearest dialysis facility.
The 'nearest appropriate facility' trap
If a crew takes a patient to a farther facility, the claim may not be supported. Make sure the run report says why the destination was chosen. Billing staff cannot fix a missing reason after the fact.
Which documents does an ambulance claim need?
An ambulance claim needs a care report that supports medical necessity, and for some non-emergency trips a signed certification statement. The certification rules depend on whether the transport is scheduled and repetitive, and on where the patient was.
| Transport type | What is required | Timing |
|---|---|---|
| Repetitive, scheduled non-emergency | PCS from the physician | Before the service; dated no earlier than 60 days before it |
| Unscheduled or non-repetitive, patient in a facility under a physician’s care | PCS, or a non-physician certification if the attending physician cannot sign | Within 48 hours after the transport |
| Unscheduled or non-repetitive, patient at home or in a facility not under direct physician care | No certification required | Not applicable |
| Certification not obtained | Document your attempts, then the claim may be submitted | After 21 calendar days from the date of service |
Source: 42 CFR 410.40(e) (eCFR) and CMS Medicare Learning Network, Ambulance Services provider compliance tips.
Repetitive means three or more round trips in a 10-day period, or at least one round trip a week for three weeks, per the CMS provider compliance tips. A signed statement alone does not prove medical necessity. CMS says all other program criteria must also be met, and the medical record must explain why ambulance transport was needed, consistent with the patient’s current condition.
Signatures are a second document risk. Claims require the patient’s signature or that of an authorized person. When the patient cannot sign, the rules list who may, including a guardian, a relative arranging treatment, a facility representative, or the provider’s representative who was present during transport. If a representative present during transport signs, CMS says specific documentation must be kept for at least four years from the date of service.
How do you build a clean ambulance claim?
A clean ambulance claim has a service line, a mileage line, a valid origin and destination modifier, the pickup ZIP code, and support in the record for each. Check these before submission, because ambulance claims that are missing pickup data can be returned as unprocessable.
The Medicare Claims Processing Manual sets out the format. Independent suppliers bill on the 837 professional transaction or the CMS-1500; hospital-based providers use the 837 institutional transaction or the CMS-1450. Each trip generally needs two lines, one for the service and one for mileage. The point-of-pickup ZIP code is required, and the old paper CMS-1491 is no longer valid. Origin and destination modifiers are made by combining two letters, the first for where the trip started and the second for where it ended.
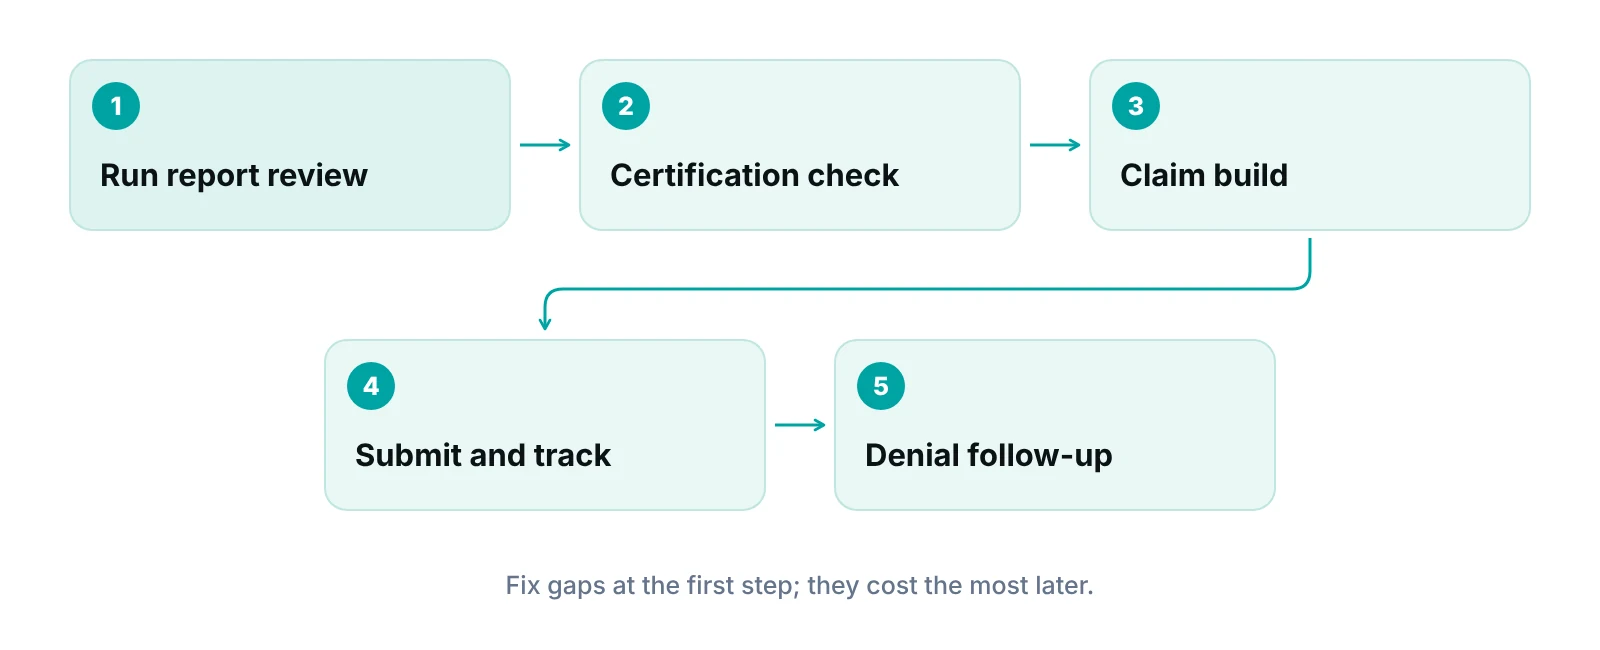
- Review the run report. Confirm it supports the service level and the reason ambulance transport was needed.
- Check certification and signatures. Match each trip to the rule for its transport type.
- Build both lines. Service line and mileage line, with the origin and destination modifier and pickup ZIP.
- Scrub before sending. Run a completeness check; claim scrubbing catches missing fields while they are cheap to fix.
- Track every claim. Know which stage it is in and who owns the next step.
The fourth and fifth steps are where software helps. A practice management system that tracks claims by stage with an owner on each claim and data-completeness checks before submission keeps a stalled claim visible. See also our guide to clean claims.
Why do ambulance claims get denied or paid wrongly?
Most ambulance payment errors in Medicare come from missing documentation, not wrong codes. CMS reported a 13.2% improper payment rate for ambulance services in its 2024 reporting, a projected $595.1 million. Of those errors, 63.5% were insufficient documentation and 27.5% were medical necessity.
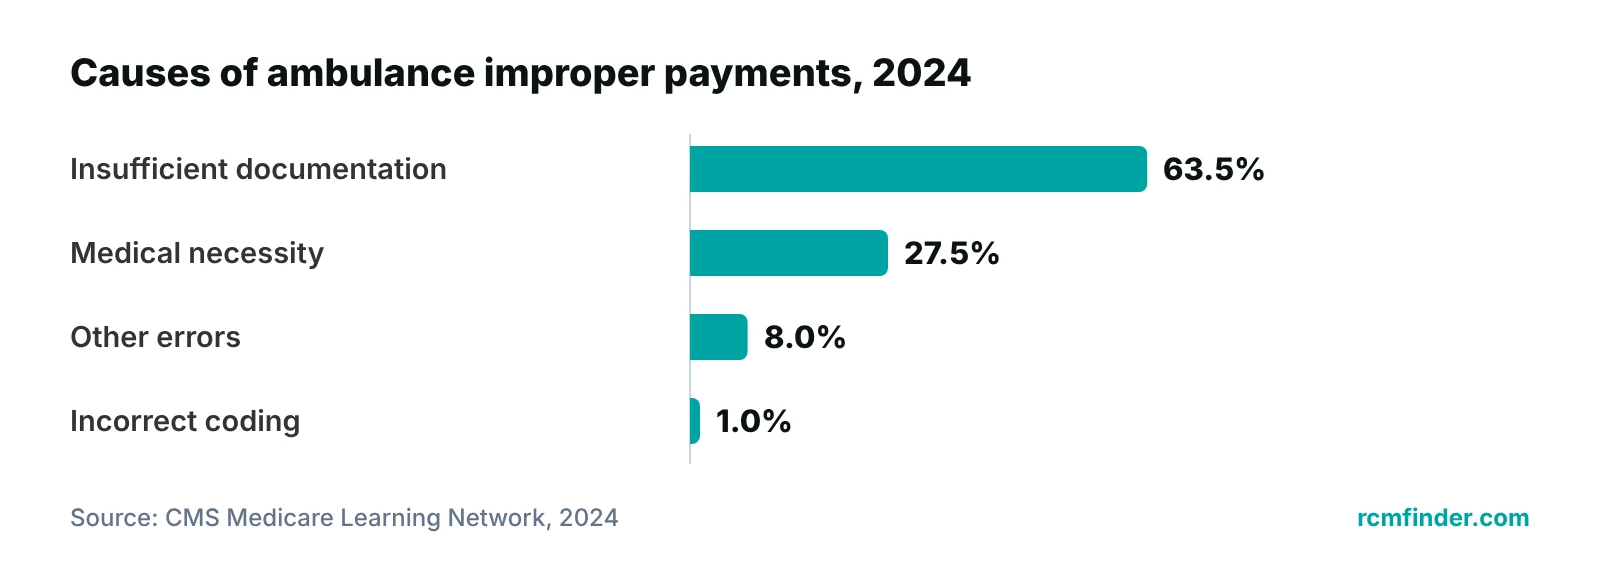
The remaining 8% were other errors such as duplicate payment, non-covered or unallowable services and ineligible patients; incorrect coding was 1%. These are improper payment findings, not a claim denial rate, so do not read them as the share of claims that get denied. They do show where reviewers look: the paperwork behind the trip.
That changes where a billing team should spend effort. Crews should write run reports that state the patient’s condition, why other transport was unsafe, and why the destination was chosen. Billers should flag thin reports before the claim goes out and feed the pattern back.
When a denial does arrive, sort it by cause: missing certification, medical necessity, wrong destination, missing pickup data, or a payer-specific rule. Each has a different fix and a different appeal. Our guide to denial management covers the appeal workflow, and denial management services describes how we work denied claims for practices that want help.
See what your own denials are telling you
Use the calculator to estimate how much revenue is stuck in unpaid or denied claims, then compare it with your current process.
What about patient bills and balance billing?
Patient statements are the part of ambulance billing most likely to draw complaints, and the rules on balance billing for ground ambulance are still being worked out. Plan for clear communication rather than assuming a federal rule protects the patient.
CMS convened the Advisory Committee on Ground Ambulance and Patient Billing to review ways to disclose charges and to protect consumers from balance billing for ground ambulance services. The committee issued its report on August 28, 2024, and CMS lists it as currently inactive. We have not verified what has changed in law since then, so check current federal and state rules before you write patient policies.
In practice: send an itemized statement, say what insurance paid and what is left, give a phone number that a person answers, and document every patient contact.
Should you bill in-house, outsource, or split the work?
Outsource when you cannot staff the documentation review and follow-up reliably; keep it in-house when you have trained billers and tight links to the crews. Many services split the work, with outside help on denials and A/R and an internal person owning crew feedback.
| Model | Works best when | Watch for |
|---|---|---|
| In-house | You have trained billers and crews who respond to documentation feedback | One person leaving can stall billing; training is on you |
| Fully outsourced | Volume is steady and you want the whole claim cycle handled | Weak feedback loop to crews if reports are never reviewed with them |
| Hybrid | You want internal control of run reports and outside help on denials and A/R | Unclear hand-offs; agree who owns each stage in writing |
| Software only | You already have staff and need claim visibility | Software does not fix thin run reports |
Source: RCM Finder operational guidance; not a statistic.
What to ask any billing vendor
Ask whether they will sign a Business Associate Agreement before touching patient data, how access is limited by role, and whether there is an audit trail of who changed a claim. Ask how they check that the care report supports the billed level of service, and how they report claim status to you. Pricing should be quoted in writing after they have reviewed your volume.
RCM Finder’s team works inside your existing systems and handles medical billing services including charge entry, claim submission and follow-up.
“If the run report is thin, no biller can rescue the claim. Fix the report before the process.”
Get a free look at your ambulance billing process
We review how claims move from run report to payment and show you where they stall. No cost to start.
Our recommendations
- Audit run reports first. Pull ten recent denied or underpaid trips and read the run reports. We look for the patient’s condition, why other transport was unsafe, and why that destination was chosen.
- Match every trip to a certification rule. Add a field to your intake that records whether the trip is repetitive, unscheduled in a facility, or from home, so the right statement is requested on time.
- Check both claim lines. Make the mileage line and the pickup ZIP code hard stops before submission. Missing pickup data is a preventable return.
- Sort denials by cause. Tag every denial as documentation, medical necessity, destination, certification or other. Review the tags monthly and share them with crews.
- Plan around the add-on end date. The temporary ground add-ons currently run through December 31, 2027. Model your revenue with and without them.
- Write the patient process down. Itemized statements, a named contact and a call log protect both patient relationships and your team’s time.
Track every ambulance claim by stage, with one owner.
RCM Finder's portal tracks claims by stage with an owner, runs data-completeness checks before submission, and flags payments below expected amounts. It is a claim-centred practice management system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Ambulance billing is a documentation business first and a coding business second. If your denials point back to thin run reports or missing certifications, the fix starts before the claim exists. When you want a second set of eyes, see our denial management services or ask for a free practice audit and we will show where your claims stall.
Frequently asked questions
What are ambulance billing services?
Ambulance billing services handle the paperwork and follow-up that turn a transport into a paid claim. That includes reviewing run reports, building the service and mileage lines, chasing certification statements, submitting claims, working denials and sending patient statements. Some services do all of it, while others only cover denials or A/R.
Why are ambulance claims denied?
In Medicare, most ambulance payment errors come from insufficient documentation or questions about medical necessity. CMS reported that 63.5% of 2024 ambulance improper payment errors were documentation and 27.5% were medical necessity. Missing certification statements, wrong destinations and missing pickup ZIP codes also cause returns and denials.
Does Medicare cover every ambulance ride?
No. Medicare covers a transport only when the patient’s condition requires both the ambulance and the level of service billed, other transport is contraindicated, and the trip goes between covered points, such as to the nearest capable hospital. A non-emergency trip needs either bed confinement with other transport contraindicated, or a condition requiring ambulance transport.
What is a physician certification statement for ambulance?
A physician certification statement (PCS) is a signed statement supporting a non-emergency transport. For repetitive scheduled trips it must be obtained before the service and dated no earlier than 60 days before it. For some unscheduled trips from a facility, it is due within 48 hours. A PCS alone does not prove medical necessity.
How is Medicare ambulance payment calculated?
Medicare pays a base rate for the service level plus a separate mileage amount, from a national fee schedule. The base is adjusted by a geographic index set by the pickup location, which does not apply to mileage. Temporary urban, rural and super-rural add-ons currently run through December 31, 2027.
Should a small ambulance service outsource billing?
It depends on whether you can staff run-report review and follow-up reliably. Outsourcing helps when volume is steady or staffing is thin. Keeping it in-house can work when billers train crews. A hybrid, with outside help on denials and A/R, is common. Whichever you choose, require a Business Associate Agreement and written reporting.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Ambulance Services (Provider Compliance Tips) — CMS Medicare Learning Network (2024)
- 42 CFR 410.40, Coverage of ambulance services — eCFR (current)
- Medicare Claims Processing Manual, Chapter 15 (Ambulance) — CMS (current)
- Ambulance Fee Schedule Public Use Files — CMS (2026)
- Advisory Committee on Ground Ambulance and Patient Billing (GAPB) — CMS (2024)
Disclaimer: This article is educational and is not legal, coding or compliance advice. Medicare rules cited were checked against CMS and eCFR pages in October 2026 and may change; payer rules vary. Confirm requirements with your Medicare Administrative Contractor and counsel.
