
Oncology CPT codes describe the visits, drug administration, radiation management and lab work billed during cancer care. Most claim problems come from how services are combined on one claim, not from the code itself. Take descriptors from the current CPT book, then apply bundling, drug waste and documentation rules before you submit.
Cancer care is billed in pieces: the visit, the drug administration, the drug, the radiation course and the labs each follow different rules. A code list on its own does not tell you which pieces can share a claim. This guide orients billing staff and practice managers by service type and points to the primary-source rules that matter most. Exact code wording belongs to the American Medical Association, so check descriptors in your current CPT book. For the specialty overview, see our oncology billing page.
Key takeaways
- Group oncology services into five buckets: visit, drug administration, the drug, radiation, and labs. Each has its own rulebook.
- Medicare’s NCCI manual allows only one ‘initial’ drug administration code per encounter unless separate IV sites and medical necessity support two.
- A same-day E/M visit with chemotherapy needs a significant, separately identifiable service and modifier 25 to be reported.
- For single-dose drugs, Medicare Part B requires JW when any amount is discarded and JZ when none is.
- Do not build a code list from memory or from old web pages. Verify each code in the current CPT book every year.
What are oncology CPT codes?
Oncology CPT codes are the standard codes used to report services given to people with cancer, from the first consult to chemotherapy visits, radiation and follow-up. There is no separate ‘oncology code set’. The codes come from the usual CPT sections (evaluation and management, medicine, radiology, pathology and laboratory, surgery), and the specialty simply uses a particular slice of them.
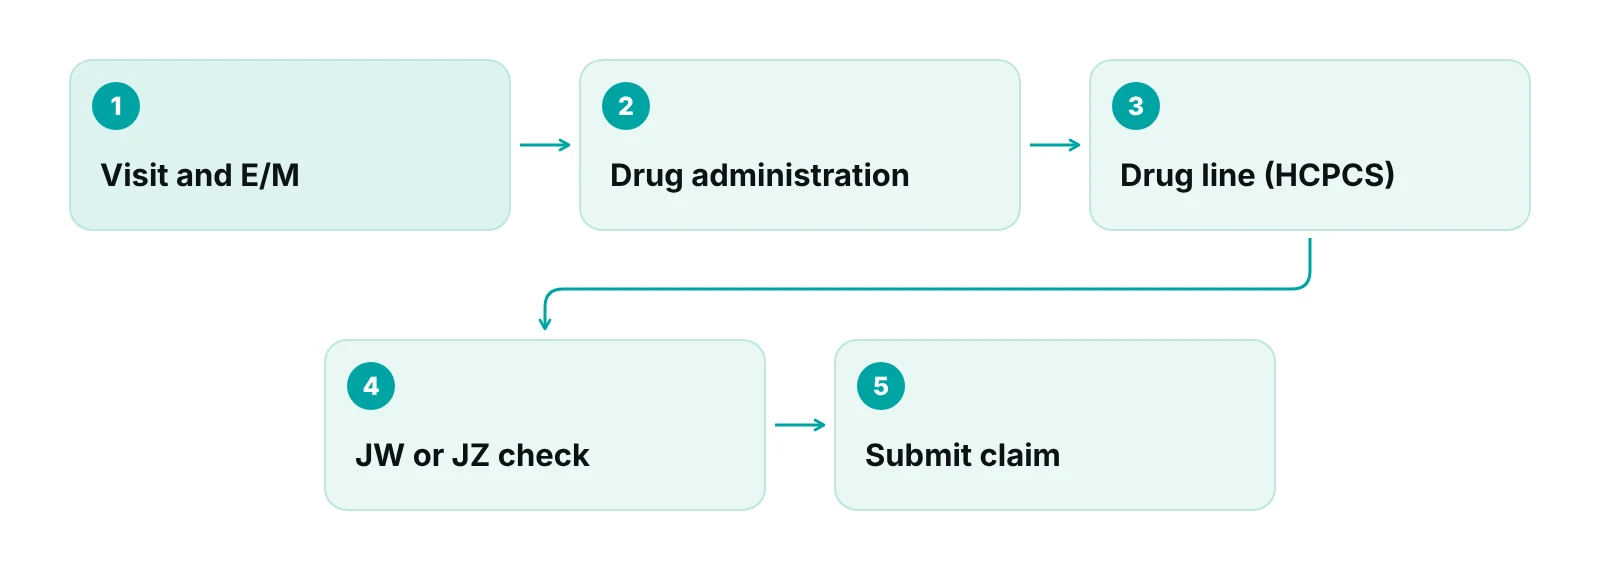
Two things sit beside CPT on every oncology claim. The first is the diagnosis, reported with ICD-10-CM. The second is the drug itself, which is billed with a HCPCS drug code on its own line, separate from the CPT code for giving it. Medicare’s drug waste instructions describe exactly that structure: a line with the drug’s HCPCS code and the units given, with a second line for any discarded amount (CMS transmittal R12067CP). If the difference between the two code sets is fuzzy, our guide to HCPCS versus CPT codes covers it, and the J-codes billing guide goes deeper on drug codes.
Why code lists on the web go wrong
Many published oncology code lists mix up neighbouring numbers, include deleted codes or leave out whole families such as drug administration. A wrong example in a training document becomes a wrong charge in the system. Take every code and descriptor from the current CPT book and your payer’s fee schedule, and re-check each January.
How do oncology services map to code families?
Think in five buckets. Each bucket answers a different question on the claim: what visit happened, how was the drug given, what was the drug, what radiation was delivered, and what was tested. The table below shows where to look for the rules in each bucket. It lists code families and rules we verified in the Medicare sources named in the notes, not a full code list.
| Service type | What is billed | Where the rule lives |
|---|---|---|
| Office or clinic visit | An evaluation and management (E/M) code, with modifier 25 when it is separate from drug administration on the same day | Medicare NCCI Policy Manual, Chapter 11, sections B.8 and N.3 |
| Chemotherapy administration | Codes such as 96409 and 96413 (initial chemotherapy services) and add-on or pump codes such as 96416 and 96425 | NCCI Chapter 11, section N |
| Non-chemotherapy infusion or injection | The therapeutic and diagnostic infusion and injection family (96360 to 96379), for example 96365 and 96374 | NCCI Chapter 11, section B |
| The drug | A HCPCS drug code with units, plus JW or JZ for separately payable single-dose Part B drugs | CMS transmittal R12067CP |
| Radiation oncology | Planning, delivery and treatment management codes, including 77427 (management, per five treatments) | NCCI Chapter IX, section F, and Chapter I |
| Tumor marker and other labs | Laboratory codes in the pathology and laboratory section, subject to national and local coverage rules | Example: Medicare NCD 190.28 for the CA 125 test |
Source: CMS, NCCI Policy Manual for Medicare Services, Chapter 11 (2026); CMS Transmittal R12067CP; CMS NCCI Policy Manual (2025); CMS Medicare Coverage Database, NCD 190.28. Code families only; get descriptors from the CPT book.
This is also why the same patient visit can produce four or five claim lines that must agree with each other. A visit code that the payer allows, a drug administration code that passes the bundling edit, a drug line with correct units and a waste modifier, and a diagnosis that supports all of them. When one line fails an edit, the whole claim often stalls.
What are the main chemotherapy administration billing rules?
The main rule is that only one ‘initial’ drug administration code is reportable per patient encounter. In Medicare’s NCCI manual, 96360, 96365, 96374, 96409 and 96413 are all initial service codes, and a second one is reportable only when the administrations happen at separate IV access sites and are medically necessary, with the appropriate NCCI modifier (CMS NCCI Policy Manual, Chapter 11, 2026).
| Situation | What the manual says | Billing impact |
|---|---|---|
| Two initial codes in one encounter | Only one initial service code per encounter, unless separate IV sites and medical necessity | A second initial code without modifier support will be denied or bundled |
| Hydration given with chemotherapy | Hydration concurrent with chemotherapy is not separately reportable; fluid that only carries a drug or keeps a line open is also not reportable | Do not add a hydration line for routine carrier fluids |
| Non-chemotherapy infusion alongside chemotherapy | A concurrent infusion may be reported with 96368, one unit per encounter | Cap units at one |
| Flushing an implanted port | Integral to the service; do not report 96523 | No separate charge for a routine flush |
| Pump filling and refills | 96416 and 96425 include the initial pump filling; 96521 and 96522 are for later refills and not reported with 96416 or 96425 | Check the pair before adding a refill code |
| Setting | 96360 to 96379 and 96401 to 96425 are reportable by physician offices but not in a facility setting; hospital outpatient departments may report them when appropriate | Site of service changes which rules apply |
Source: CMS, NCCI Policy Manual for Medicare Services, Chapter 11, sections B and N (2026).
These are Medicare rules. Commercial payers often follow NCCI logic but add their own edits and prior authorization requirements, so confirm payer policy before treating any row as universal. Use the current edition of the manual, since edits and policy are updated.
Because the setting matters, an oncology group that treats patients in the office and in a hospital outpatient department can have two different billing paths for similar visits. Document where each service was given before coding it. For single-injection coding in a clinic, the 96372 CPT code guide is a useful companion.
When can an E/M visit be billed on the same day as chemotherapy?
A separate E/M visit can be reported on the same day as drug administration only when it is significant and separately identifiable, and it then carries modifier 25. Under Medicare’s NCCI policy, the lowest-level E/M code, 99211, is treated as included in the drug administration codes and is not separately reportable (NCCI Chapter 11, sections B.8 and N.3, 2026).
In the hospital outpatient setting the rule has a facility twist. Under OPPS, hospitals may report a facility E/M code, including G0463, with drug administration and modifier 25 when the E/M is significant and separately identifiable. Facility emergency department codes 99281 to 99285 cannot be reported with drug administration unless the drug was given at a separate, non-facility encounter that day, per the same manual sections.
“A visit that only checks a patient in for infusion is part of the infusion. A visit that decides on a treatment change, orders new work-up or manages a new problem is a separate service, and the note has to show it.”
Documentation is what makes modifier 25 hold up. The note should show a problem-oriented assessment and decision-making that goes beyond the pre-treatment check. For how modifier 25 differs from modifier 59 and when each is appropriate, read modifier 25 versus 59 in medical billing.
How do JW and JZ modifiers work for oncology drugs?
For separately payable Medicare Part B drugs supplied in single-dose or single-use containers, claims must show either the discarded amount with JW or an attestation that nothing was discarded with JZ. JW has been required since January 1, 2017, and JZ became a claim requirement on July 1, 2023 (CMS transmittal R12067CP). Oncology drugs are often expensive single-dose products, so errors here add up fast.
| Situation | What to report | Notes |
|---|---|---|
| Part of the vial is discarded | Line 1: HCPCS drug code with units administered. Line 2: same code with JW and units discarded | Record the discarded amount in the patient’s medical record |
| Nothing is discarded | HCPCS drug code, units administered, with JZ | JZ attests to zero waste |
| Billing unit is larger than dose plus waste | Use JZ; JW cannot be used | CMS example: a 10 mg unit, 7 mg given, 3 mg discarded is billed as one unit with no JW line |
| Multiple-dose container, packaged OPPS or ASC drug, FQHC or RHC | JW and JZ do not apply | Check the drug’s labeling and payment status |
Source: CMS Transmittal R12067CP (JW and JZ modifier policy).
Two cautions apply. First, confirm whether the drug is single-dose in its FDA labeling and separately payable under Part B before you apply either modifier. Second, other payers have their own waste policies. Some follow Medicare, others do not, so check each contract. The J-codes billing guide explains how drug units and billing units relate.
How is radiation oncology coded and billed?
Radiation oncology has its own section in the NCCI manual, and a course of treatment is billed in parts: planning, delivery and management. The NCCI Chapter IX table of contents lists a radiation oncology section (F) within its radiology chapter covering CPT 70000 to 79999 (CMS NCCI Policy Manual, 2025).
One rule is easy to verify and worth flagging. Radiation treatment management, billed with 77427 for each group of five treatments, cannot be reported with modifier 59 under NCCI policy (same manual, Chapter I). If an edit blocks a management code, do not reach for modifier 59. Review the documentation and the payer’s policy instead.
We did not list individual planning, dosimetry and delivery codes here. Those codes change, and the exact pairings depend on the technique and the payer, so build that list from the current CPT book and the payer’s radiation oncology policy. For a general view of imaging and radiology coding, see our radiology CPT codes guide.
What about labs and tumor markers?
Tumor marker and other laboratory tests are reported with laboratory codes, and coverage often depends on why the test was ordered. Medicare’s national coverage determination for the CA 125 tumor antigen is a good example. It covers uses such as a baseline before surgery for a suspicious pelvic mass, tracking after surgery or chemotherapy, checking for residual disease at the end of chemotherapy, surveillance, and monitoring response in advanced or recurrent disease. It does not cover the test to evaluate signs or symptoms that suggest cancer or to help in the differential diagnosis of a pelvic mass (CMS NCD 190.28).
The lesson for billing teams is that the diagnosis and order reason must match the coverage policy. The version of the NCD we reviewed took effect in 2006 and the page notes a newer version exists, so confirm current coverage with your Medicare Administrative Contractor and the payer’s lab policy. Palliative and supportive services have their own coding questions, covered in our palliative care CPT codes guide.
What should be checked before an oncology claim goes out?
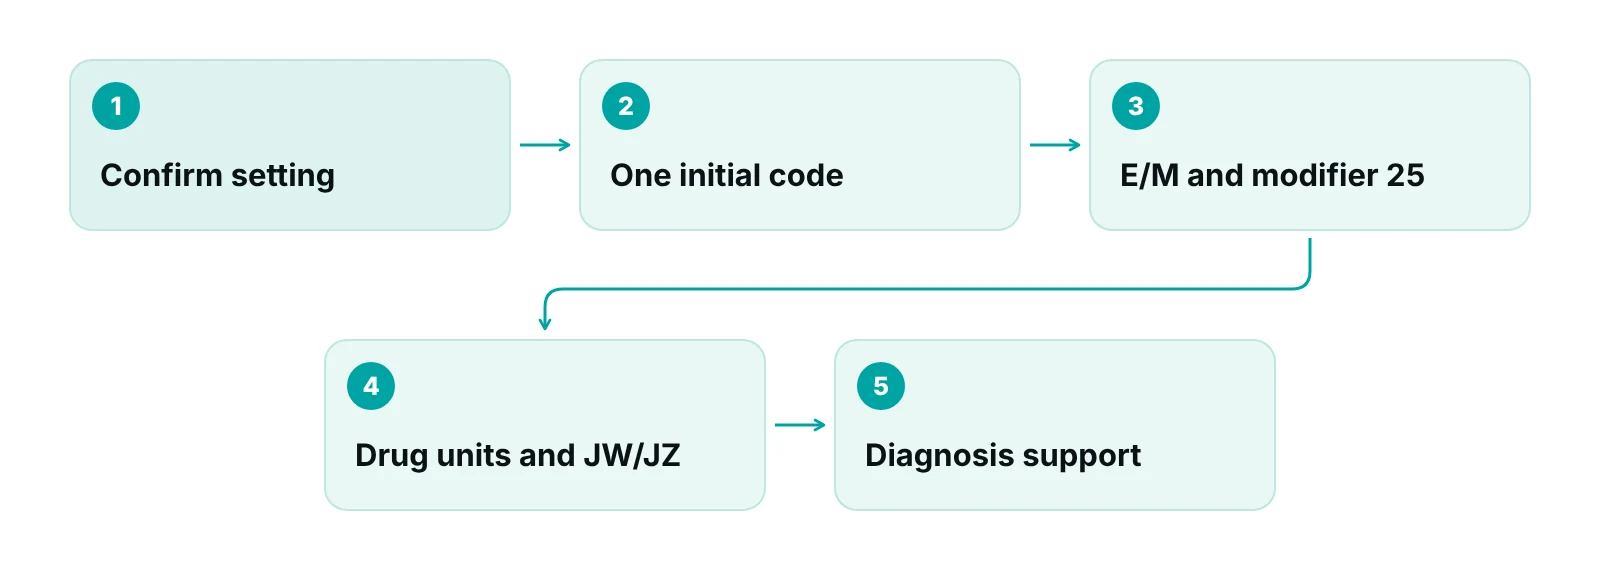
A short pre-submission check catches most avoidable problems. Use it as a checklist for the front end of billing, before the claim reaches the payer.
- Confirm the setting (office or hospital outpatient department) because it changes which drug administration rules apply.
- Check that only one initial drug administration code is on the claim, or that separate IV sites and medical necessity are documented.
- Remove hydration and flush charges that the payer treats as incidental to chemotherapy.
- Match the E/M visit to a note that shows a significant, separately identifiable service before adding modifier 25.
- Verify the drug code, units, and JW or JZ against the administration record and the vial size.
- Confirm the diagnosis and the order reason support medical necessity for labs and radiation management.
Where this check can be systematic, a practice management system that tracks claims by stage can hold a claim for review when required fields are missing or an expected payment is not met. It does not replace coder judgment, and it is only one way to organise the work. Clear charting also underpins every row above, which is why our post on documentation and medical billing is worth sharing with clinical staff.
How should a practice build and maintain its oncology code list?
The safest approach is to treat the code list as a controlled document with an owner and a yearly review, instead of a one-time spreadsheet. CPT codes change over time, so an unchecked list drifts out of date. Start from the practice’s actual service mix: the drugs it administers, the sites of service it bills, and the payers it contracts with.
Billing and coding support for a specialty with this many moving parts is an area where practices look for outside help. If that is where you are, our medical billing services page explains what a review of your current workflow looks like, and the revenue calculator gives a rough view of what denials may be costing you.
See where oncology claims are slowing down
Request a free practice audit and we will look at how your drug administration, E/M and drug lines are coded and tracked.
Our recommendations
- Name an owner for the code list. We recommend one person owns the oncology code list and reviews it every January against the current CPT book and payer updates.
- Separate the five buckets in your charge capture. We recommend the charge screen shows visit, administration, drug, radiation and lab lines separately so each can be checked on its own rules.
- Record waste at the time of administration. We recommend the nurse or pharmacist documents the discarded amount when the drug is given, so the JW or JZ choice is not reconstructed later.
- Back up modifier 25 with the note. We recommend coders confirm a separate, significant assessment is documented before adding modifier 25 to a visit that falls on a treatment day.
- Read payer policies, not just Medicare's. We recommend keeping a short sheet of each major payer’s rules on hydration, waste and bundling, since they can differ from Medicare.
A claim-centred practice management system can hold oncology claims for review before they go out.
RCM Finder's portal tracks claims by stage with an owner, runs data-completeness checks before submission, and flags payments below expected amounts. It is not an EHR and does not replace a coder's judgment.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Oncology CPT codes are manageable once services are split into visit, administration, drug, radiation and lab buckets and the bundling and waste rules are checked on every claim. Start with the current CPT book, apply the CMS rules above, and confirm payer differences. If denials keep returning on these lines, our denial management services team can help trace the cause.
Frequently asked questions
What are oncology CPT codes?
They are the CPT codes used to report cancer care services, including visits, chemotherapy and other drug administration, radiation oncology and related lab work. They come from several CPT sections, not one oncology list. The drug itself is reported separately with a HCPCS code.
Can two chemotherapy administration codes be billed in one visit?
Under Medicare NCCI policy, only one initial service code is reportable per encounter. A second is allowed only when the administrations are at separate IV access sites and are medically necessary, with the proper modifier. Add-on codes follow their own pairing rules, and other payers may differ.
Is hydration billable with chemotherapy?
Under Medicare NCCI policy, hydration concurrent with chemotherapy is not separately reportable. Fluid that only carries a drug or keeps a line open is also not reportable. Therapeutic fluid given for a documented medical reason may be reportable, so check the manual and your payer.
When do I use JW and JZ?
For separately payable Part B drugs in single-dose containers, JW reports the discarded amount and JZ reports that none was discarded. JZ has been required since July 1, 2023. They do not apply to multiple-dose containers or packaged OPPS and ASC drugs.
Can I bill an E/M with chemotherapy on the same day?
Yes, if the visit is significant and separately identifiable, and modifier 25 is added. The lowest-level E/M code, 99211, is included in drug administration under Medicare policy. The note must show the extra work, such as a treatment decision or a new problem.
Where do I find the exact descriptors for oncology CPT codes?
In the current CPT code book or an AMA licensed product. The AMA controls the official wording, and codes change each year. Avoid copying descriptors from old web pages, since they may be out of date or wrong.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- NCCI Policy Manual for Medicare Services, Chapter 11 (Medicine) — CMS (2026)
- Transmittal R12067CP, JW and JZ modifier policy — CMS (2022)
- NCCI Policy Manual for Medicare Services (complete) — CMS (2025)
- NCD 190.28 Tumor Antigen by Immunoassay CA 125 — CMS Medicare Coverage Database (2006)
Disclaimer: This article is educational and is not legal, coding or compliance advice. Code descriptors belong to the AMA, and payer rules vary and change. Confirm current requirements in the CPT book, the Medicare NCCI manual and your payer contracts.
