
Pathology Specialty

Pathology Billing Services for Pathologist Groups and Independent Labs

Professional and technical splits, specimen and stain units, molecular date-of-service rules and denial follow-up, built on Medicare rules and your own contracts, with requisition checks and a claims portal.
  • Works inside your current EHR
  • US practice time zone, every shift
  • Weekly KPI reporting, or on your schedule
Pathology billing dashboard with professional and technical splits, units per specimen, denials by reason, A/R days and unbilled cases

Quick answer

Pathology billing services turn each accession into a payable claim: global, professional (26) or technical (TC) billing set by who did the work, units counted per specimen, stain or antibody, the correct date of service, a CLIA number and a diagnosis the payer accepts. RCM Finder adds requisition checks, client-facing marketing and a claims portal.

Disclaimer: This page is educational and is not legal, coding or compliance advice. Medicare rules, contractor policies, NCCI edits and commercial payer policies change often and vary by contractor, plan and state. Verify every code, modifier, date-of-service rule and limit against your Medicare contractor's current documents, your payer contracts, state law and the current CPT and HCPCS code sets before billing.

Why pathology billing is different

A pathology claim often joins work done by different people in different places. A lab prepares the slide, a pathologist reads it, and the specimen may come from a hospital patient. One wrong modifier can send the claim to the wrong payer.

Physician pathology services are paid on the Medicare physician fee schedule. Clinical laboratory tests are paid on the clinical laboratory fee schedule (CLFS). Molecular tests add coverage rules. For code primers, read our pathology CPT codes guide and our pathology modifiers explainer.

Where the laboratory fee schedule stands (October 2026)

CMS says the 2026 PAMA reporting period ran from May 1 to July 31, 2026, using private payor data from January 1 to June 30, 2025. Section 6226 of the Consolidated Appropriations Act, 2026, passed February 3, 2026, delayed the phase-in of cuts. There is no phase-in reduction in 2026. From January 1, 2027 through 2029, a test's payment may not fall more than 15% a year. The ADLM reported the same delay.

Reporting applies to independent, physician office and hospital outreach labs that meet CMS's Medicare revenue thresholds, including at least $12,500 in laboratory fee schedule revenue in the collection period. CMS has posted preliminary CY 2027 data and wants feedback before October 21, 2026.

The four pillars, built for a pathology group or lab

Revenue leaks at the handoffs: a requisition with no diagnosis, a technical component billed by the wrong entity, a stain counted twice. A pathology practice needs referrers who trust it, complete requisitions, correct splits and software that shows where each case stands.

Pillar 1 · Healthcare Marketing

Healthcare Marketing for pathology

Pathology volume comes from referring practices and hospitals, not patient ads. Our healthcare digital marketing builds what a practice manager or lab director checks before sending specimens. Clear any referral-source outreach with your compliance counsel.

  • Test menu and specimen-handling pages
  • Client onboarding pages
  • Recruiting pages for pathologists
  • KPI: qualified client inquiries
Explore Healthcare Marketing
Pillar 2 · Virtual Medical Assistants

Virtual Medical Assistants for requisition follow-up

Our virtual medical assistants for pathology work on your practice's time zone. They chase what a requisition left out, check eligibility and answer patient billing calls.

  • Missing insurance and ordering data chased
  • Eligibility checked before billing
  • KPI: accessions billed with complete data
Explore Virtual Medical Assistants
Pillar 3 · End-to-End RCM

End-to-End RCM for pathology claims

Our end-to-end pathology revenue cycle management covers charge entry, coding support, claim scrubbing, denials and A/R follow-up, with pathology checks on the split, units, date of service and CLIA number.

  • Global, 26 or TC set by who did the work
  • Units counted per specimen, block or antibody
  • KPI: denials by reason and A/R days
Explore End-to-End RCM
Pillar 4 · Practice Management System

Practice Management System for pathology billing

Our practice management system tracks every case by claim stage, applies specialty-aware billing logic per claim, checks data completeness before submission and flags underpayments. Billing companies get a client portal.

  • Rules that hold a claim missing a diagnosis or NPI
  • Underpayment flags against expected amounts
  • Role-based permissions and an audit log
  • Coming next: credentialing module
Explore Practice Management System

Find where your pathology claims leak

We review recent accessions, remittances and denials, then show where splits, units or missing data cost you.

Get a Free Practice Audit

Professional, technical and global billing: who bills what

Bill the global service only when one entity performs both the technical work and the interpretation. Otherwise the pathologist bills 26 for the reading and the entity that did the technical work bills TC.

Noridian defines modifier 26 as interpretation only. It says not to use 26 when the provider performed the global service, and to bill the two parts separately when they come from different enrolled locations. CMS's SE0587, an article about imaging, uses the same split: the professional component is the physician's interpretation and the technical component is practice expense: staff, supplies and equipment.

Independent lab or hospital pathologist?

Under 42 CFR 415.102, Medicare pays a physician's services to hospital patients on the fee schedule only if the physician personally furnishes them, they contribute directly to diagnosis or treatment, and they ordinarily require a physician. Services that fall short but relate to care the hospital furnishes are paid through the hospital under its own payment rules, and neither the hospital nor the physician may seek payment from the carrier, the patient or another insurer.

Fee schedule pathology under 42 CFR 415.130 includes surgical pathology, specific cytopathology, hematology and blood banking services, and qualifying clinical consultations. For services after June 30, 2012, an independent lab may not bill the Medicare contractor for the technical component of physician pathology services for hospital inpatients or outpatients. Noridian says the facility pays the technical portion. Read each hospital contract. Our post on pathology claim documentation covers records contractors request.

Counting units: surgical pathology, special stains and IHC

Each code counts a different unit: a specimen, a stain on a block or an antibody stain on a specimen. Count the wrong unit and you over-bill or under-bill.

The 2026 NCCI policy manual, chapter 10, defines a specimen as tissue submitted for individual and separate attention, examination and diagnosis. Separate containers usually mean separate specimens, but several biopsies of one polyp are usually one. Code 88305 is a level IV exam and 88307 a level V exam, per AAPC (secondary).

Pathology billing situations, Medicare rules and denial triggers
SituationCode or modifier (our wording)Medicare ruleTypical denial or overpayment trigger
Pathologist reads slides prepared elsewhere26 on the readingInterpretation only; no 26 if the same provider did the global service (Noridian)26 added to a global service
Independent lab, hospital patientTCNot billable to the Medicare contractor after June 30, 2012 (42 CFR 415.130(d)(2))TC billed for a hospital inpatient or outpatient
Surgical pathology specimens88305 (level IV), 88307 (level V)Unit is the specimen; gross exam is included (NCCI ch. X, sections M.8, L.9)Units counted by container or slide
Prostate needle biopsiesG0416One unit for all needle biopsies, not 88305 (NCCI section L.10)88305 billed for each core or site
Special stains88312 and 88313 (stain groups I and II)One unit per stain per tissue block; controls are not billable (NCCI section M.9)Extra units for one stain on one block
Immunohistochemistry88342 (first antibody), 88341 (each additional)Each antibody stain per specimen; several blocks of one specimen count once (NCCI section M.9)Units counted per block or per slide
Molecular pathology, Tier 1 or 281xxx codesOne unit per specimen from one source; one unit if one procedure covers several genes (NCCI sections M.4, F.8)Stacked codes; duplicate gene testing

Sources: CMS NCCI Policy Manual ch. 10 (2026); eCFR 42 CFR 415.130 (2026); Noridian JF modifier 26 page (2025); AAPC (secondary, code meanings). Rules vary by payer.

Set the unit rule per code in the billing system and compare billed units with the accession and block count.

Molecular and genomic tests: date of service, identifiers and documentation

A laboratory test usually takes the specimen collection date. For a hospital outpatient's molecular test, the test date replaces it only if all five conditions in 42 CFR 414.510(b)(5) are met.

Under 42 CFR 414.510, the date of service is generally the collection date. A specimen stored more than 30 days is archived, and its date is the day it was retrieved. CMS's date-of-service page says that when the molecular exception applies, the performing lab bills Medicare directly. The exception covers molecular pathology tests (not those run by blood banks) and certain advanced diagnostic tests. All five must be met:

  1. The test is performed after the hospital outpatient is discharged from the outpatient department.
  2. The specimen was collected during an outpatient encounter.
  3. Collecting it during that encounter was medically appropriate.
  4. The results do not guide treatment during that encounter.
  5. The test is reasonable and medically necessary to treat an illness.

The same policy applies to the technical component of physician pathology specimens (42 CFR 415.130(d)(3)). We flag every hospital outpatient specimen for a date review.

Identifiers and records, with two MAC examples

Noridian's MolDX policy, LCD L35160 (revision effective February 5, 2026), requires each molecular diagnostic test to carry a unique test identifier as extra claim documentation and covers only tests that pass MolDX's technical assessment. Novitas's billing article A58917 (revision effective July 1, 2026) adds these points:

  • Stacking or unbundling codes for one test brings rejection or denial.
  • A valid PLA code is used instead of Tier 1 or Tier 2 codes when one exists.
  • Tier 2 codes 81400 to 81408 need the analyte or gene in the claim narrative, and 81479 needs the gene in the claim field.
  • The record must show how the results were used.

Other MACs may differ. First Coast lists pathology and laboratory codes whose claims must carry medical records, and a listed code without them rejects (September 2026 page). Oncology practices often order tumor testing; see our oncology billing services.

Requisitions, medical necessity and the edits that deny pathology claims

Most avoidable denials start before the specimen is cut: a thin requisition, no diagnosis, no ABN or a missing CLIA number.

In a College of American Pathologists presentation (May 2023), prior authorization was the top anatomic pathology denial reason, rising from 28.9% of total denials in 2018 to 36.1% in 2021. Our prior authorization guide covers the process.
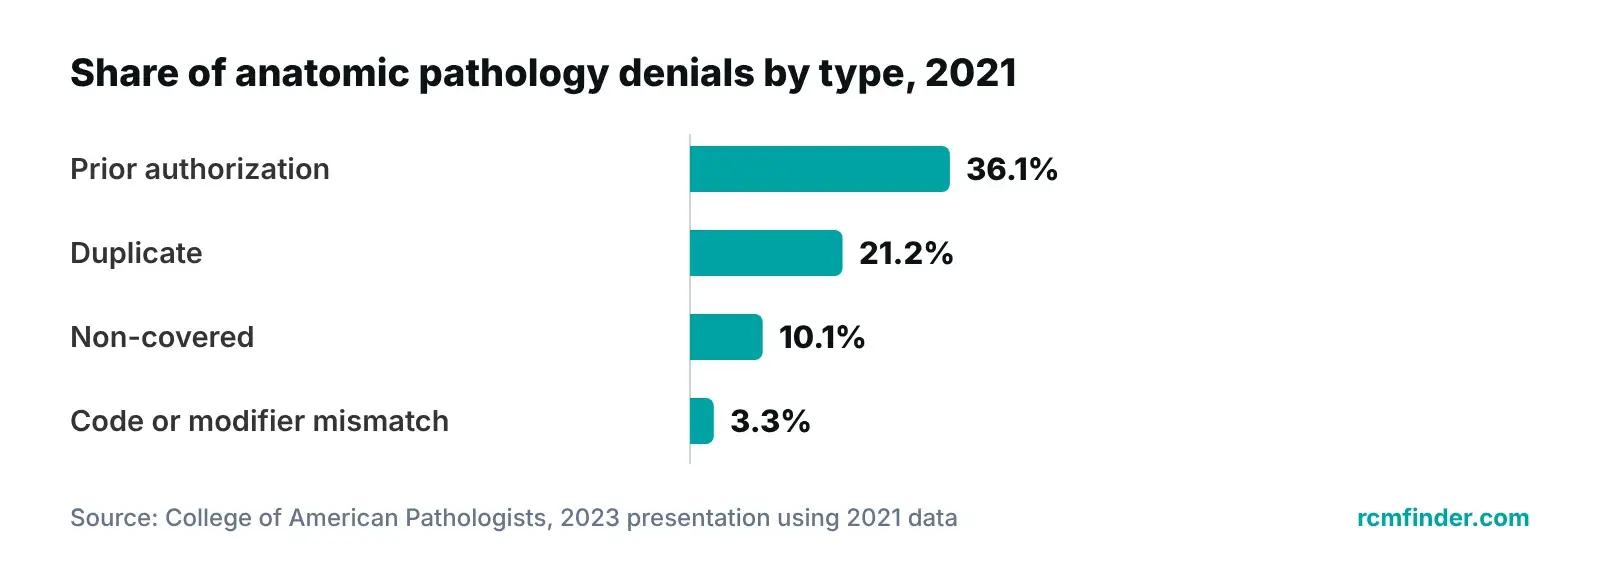
Bar chart of anatomic pathology denials by type in 2021: prior authorization 36.1%, duplicate 21.2%, non-covered 10.1%, code or modifier mismatch 3.3%
Prior authorization was the largest share of anatomic pathology denials in the College of American Pathologists' 2021 data.

Requisition and ordering-provider data

Under 42 CFR 493.1241, the requisition must ask for the requester, patient identifier, sex and age, tests, specimen source and collection date. Under 42 CFR 410.32, the claim must reflect what the orderer supplied.

Missing diagnosis codes

If CMS asks, the submitter must produce the diagnosis or narrative the orderer supplied. If it does not show the test was necessary, CMS requests the orderer's records and denies the claim if they do not arrive (42 CFR 410.32(d)(3)). MM14536 says MACs apply uniform edits to 23 laboratory NCDs; the October 2026 update changed ICD-10 lists for 11. Return requisitions with no diagnosis to the ordering practice.

ABNs and the CLIA number

Noridian says an ABN is required when a service is expected to be denied, physicians should forward ABNs to labs, and routine ABNs are prohibited. See also claims manual chapter 16, section 40.7, and our ABN guide.

Under 42 CFR 493.3, a lab must hold a certificate covering its tests or be CLIA-exempt, and CMS says labs must be certified to receive Medicare or Medicaid payment. First Coast says a missing or invalid CLIA number returns a claim (CO 16 tips).

See what denials and underpayments cost you

Enter your volume and denial rate to estimate what your pathology practice is losing.

Open the Revenue Calculator
Pre-claim checklist for each pathology accession
CheckWhy it mattersSourceWhat the VMA or biller does
Requisition completeLab needs requester, patient identifiers, tests, specimen source and collection date42 CFR 493.1241 (2026)Gaps chased with the ordering practice
Ordering practitioner, diagnosis, coverage editsClaim must match what the orderer sent; MACs apply NCD edits using ICD-10 lists42 CFR 410.32; CMS MM14536 (2026)Orderer's diagnosis saved; checked against the NCD or LCD
ABN when non-coverage is expectedNeeded before a test believed not reasonable and necessary; not routineNoridian (2026); CMS manual ch. 16, 40.7Ordering practice asked for the ABN
CLIA number on the claimMissing or invalid number returns the claimFirst Coast (2025); CMS manual ch. 16, 40.1.1Certificate matched to the performing lab
Date of serviceCollection date unless a rule moves it42 CFR 414.510 (2026)Hospital outpatient and stored specimens flagged
Molecular and MAC documentationIdentifiers and records differ by contractorNoridian L35160; Novitas A58917; First Coast (2026)Rules loaded per MAC and reviewed each quarter

Sources: eCFR 42 CFR 493.1241, 410.32 and 414.510 (current as of 10/08/2026); CMS MM14536 (2026); Noridian JF ABN page (March 2026); CMS Claims Processing Manual ch. 16 (April 2026); First Coast (2025, 2026); Novitas A58917; Noridian L35160. Check your own MAC.

Client billing and patient billing

For Medicare patients, a lab bills Medicare on assignment. Check who owes what before sending a statement.

CMS's chapter 16 says Part B pays for laboratory fee schedule tests only if the laboratory, physician or group accepts assignment (section 30.1). Neither the Part B deductible nor coinsurance applies to assigned clinical laboratory tests (section 30.2). That covers clinical laboratory tests; check how cost sharing applies to physician fee schedule pathology before you bill a patient.

For other payers, client billing (invoicing the ordering practice or hospital) and patient billing depend on the payer contract and state law. Have your attorney confirm the rules for each account.

In-house team, billing-only vendor or four-pillar partner?

Keep billing in-house if you have an experienced pathology coder and clean requisitions. Use a billing-only vendor if claims are your only gap. Choose a combined partner when problems start before the specimen arrives.

Decision table: which billing model fits a pathology group or lab?
JobIn-house teamBilling-only vendorFour-pillar partner (RCM Finder)
Requisition and ordering-provider follow-upStaff chase practices by phoneBills what the lab sendsVMA chases gaps; portal holds incomplete cases
Professional, technical and global splitDepends on one experienced coderVendor coders, after the factSplit checked against who did the work
Units for specimens, stains and antibodiesManual checks against the reportBilled from the charge sheetUnit rule per code; units compared with accession counts
Molecular tests and MAC rulesHard to track across contractorsOften generic rulesRules loaded per MAC, reviewed quarterly
Referring-practice and hospital visibilityRarely anyoneNot includedMarketing pillar for client and recruiting pages
Cost structureSalaries, benefits, turnoverVaries; ask how fees are setQuoted after a free practice audit

Whichever model you choose, track denials by reason and underpayments by payer monthly.

How it works

We start with a free audit and change nothing until you see the findings. We build our billing pipeline around how claims actually move through a practice: registration, charge entry, submission, payment and follow-up. For pathology, we add the checks on this page.

  1. 1

    Free practice audit

    We compare recent accessions, remittances and denials with your reports.

  2. 2

    Business Associate Agreement and access

    We put a Business Associate Agreement in place before accessing patient data. Then our team works with the billing data your lab or EHR system provides.

  3. 3

    Client and payer map

    We list each client account's billing route, each hospital contract's billing split and each payer's rules.

  4. 4

    Checks and billing go live

    VMAs close requisition gaps. Claims are coded from the report, scrubbed, submitted and worked to payment.

  5. 5

    Weekly KPI review

    Each week we review denials by reason, A/R days, unbilled accessions and underpayments, and adjust rules.
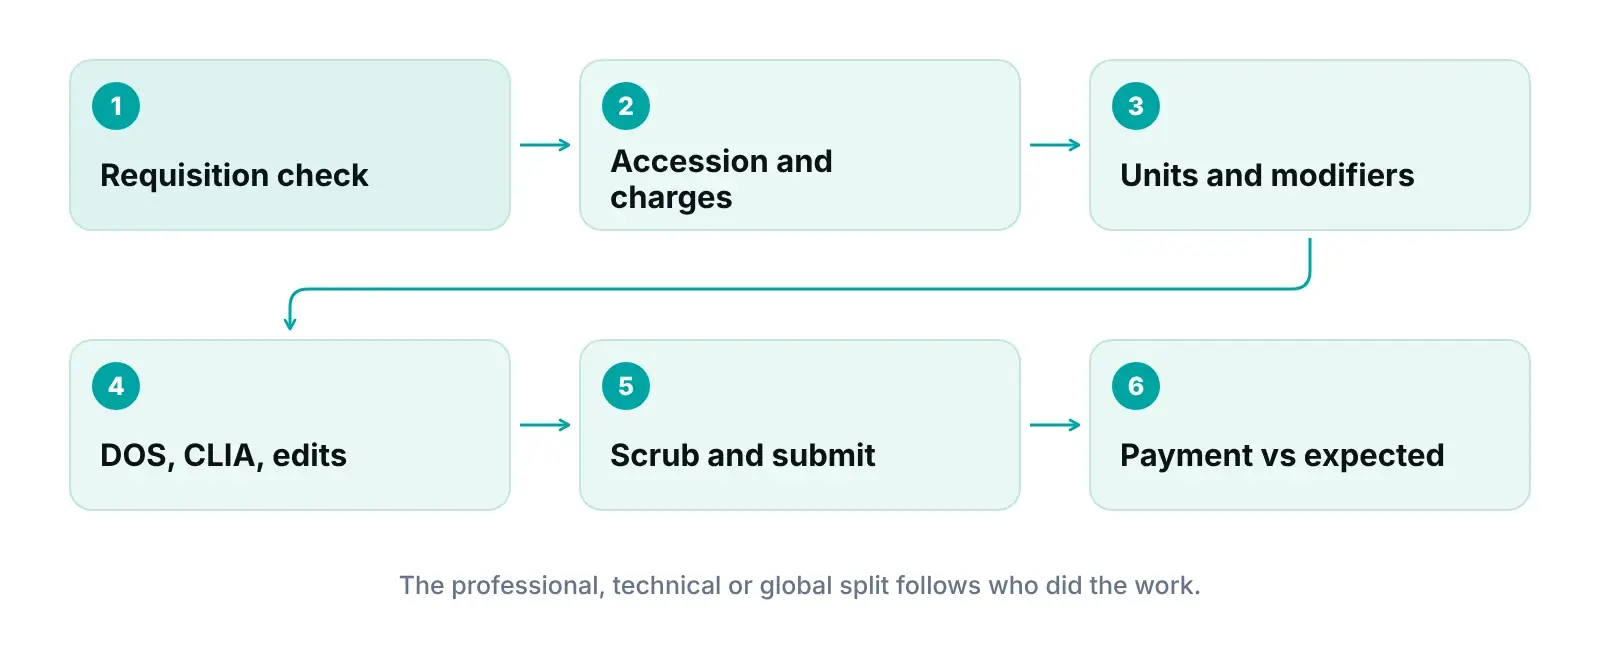
Diagram of a pathology accession moving from requisition check to charges, units and modifiers, edit checks, submission and payment review
How one pathology accession becomes a claim.

Talk to us about your pathology practice

Tell us your client mix, hospital arrangements and hardest payer. We will tell you honestly whether we fit.

Call +1 (302) 556-2288

Compliance: what to ask any pathology billing company

Any billing vendor that handles your patients' data is a HIPAA business associate. Get a Business Associate Agreement before any access.

HHS guidance names claims processing, billing and practice management as business associate work, and subcontractors need their own agreement. The minimum necessary standard limits use to what each task needs. The Security Rule's technical safeguards cover access control, audit controls, integrity, authentication and transmission security.

Questions to ask before you sign

  1. Will you and your subcontractors sign a Business Associate Agreement before any access?
  2. How do you limit each person's access, and can we see the audit log?
  3. Who codes our cases, and what credentials and pathology experience do they hold?
  4. How do you decide global, 26 or TC, and read our hospital contracts?
  5. How do you handle date of service for hospital outpatient and molecular specimens?
  6. Can we export our data if we leave?

We use role-based access, audit logging and encrypted (HTTPS) connections, and we put a Business Associate Agreement in place before accessing patient data. For your own side, use our HIPAA compliance checklist for medical practices.

Who this is for, and who it is not for

We would rather tell you now than after you sign. Here is where we fit and where we do not.

A good fit if you are

  • Pathologist groups reading for hospitals or clinics
  • Independent anatomic and clinical laboratories billing payers directly
  • Hospital outreach labs and subspecialty pathology groups
  • Labs billing molecular tests under MAC-specific rules
  • Billing companies serving several labs from one portal

Probably not a fit if you are

  • Hospital-employed pathologists whose billing the hospital controls
  • Labs unwilling to share reports and remittances
  • Practices looking for promised collection rates; we report measured KPIs instead
  • Groups that need a credentialing module in the portal today (coming next, not live)

Expert recommendations from our operations team

What we would do first if we were running your practice's revenue cycle tomorrow.

  1. 01

    Decide the split before you code

    For each accession we record who prepared the slide and who read it. That sets global, 26 or TC.

  2. 02

    Count the unit the manual counts

    Specimens, blocks and antibodies are different units. We load the rule per code and compare billed units with the accession.

  3. 03

    Treat the requisition as the first claim edit

    A requisition missing the ordering practitioner, specimen source or diagnosis goes back before billing.

  4. 04

    Flag dates of service on day one

    Hospital outpatient, stored and molecular specimens can carry a date other than collection. We flag them at intake.

  5. 05

    Keep a written rule list per MAC

    Policies such as L35160 and A58917 differ by contractor. We review them each quarter and note revision dates.

  6. 06

    Model 2027 laboratory fee schedule changes now

    Pull your top tests by volume and compare them with CMS's preliminary CY 2027 data.

Frequently asked questions

What do pathology billing services include?

They cover charge entry from the accession, coding, claim scrubbing, submission, payment posting, denial management and A/R follow-up. For pathology, that also means choosing global, 26 or TC for each claim, counting units per specimen, stain or antibody, setting the right date of service and putting the CLIA number on the claim. RCM Finder adds requisition follow-up, client-facing marketing and a claims portal.

What is the difference between the professional and technical component in pathology billing?

The professional component is the pathologist's interpretation, billed with modifier 26. The technical component is the lab work, such as staff, supplies and equipment, billed with TC. The global service combines both and needs no modifier. Noridian says not to use 26 when the provider performed the global service. After June 30, 2012, an independent lab may not bill the Medicare contractor for the technical component for hospital patients.

What is the status of PAMA laboratory fee schedule cuts in 2026?

As of October 2026, CMS says there is no phase-in reduction in 2026 after Section 6226 of the Consolidated Appropriations Act, 2026. From January 1, 2027 through 2029, a test's payment may not fall more than 15% a year. The 2026 reporting period ended July 31, 2026. CMS posted preliminary CY 2027 data and wants feedback before October 21, 2026.

How are units counted for special stains and immunohistochemistry?

Under the 2026 NCCI policy manual, a special stain is one unit per stain on a single tissue block. Immunohistochemistry is one unit per antibody stain per specimen, and multiple blocks from one specimen count once. A cocktail that gives one result counts as one stain. Controls are not billable. Payers and contractors may add their own edits, so check them as well.

Which date of service applies to a molecular test?

Usually the date the specimen was collected. For a hospital outpatient, the test date replaces it only if the test happens after discharge, the specimen was collected during an encounter, collecting then was medically appropriate, the results do not guide treatment during it, and the test is reasonable and necessary (42 CFR 414.510(b)(5)). Hospital outpatient specimens deserve a date review before billing.

Why do pathology claims deny for a missing diagnosis?

Medicare requires the claim to reflect the diagnosis information the ordering practitioner supplied, and the submitter must produce it if CMS asks. If it does not show the test was reasonable and necessary, CMS requests the orderer's records, and a claim is denied if they do not arrive. Return requisitions without a diagnosis to the ordering practice. Do not assign one yourself.

No cost, no commitment

Get your free practice audit

Tell us about your practice. A member of our operations team replies within one business day.

  • A review of your recent claims, denials and A/R aging
  • Where your front desk and prior authorizations slow payment
  • A prioritized fix list you keep, whether or not you hire us

Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.

Tell us about your practice

RCMFinder Master Intake Form
AA

About the author: Awais Afzal

Healthcare Operations & Data Analyst, RCM Finder

Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.

How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.

Sources

  1. Clinical Laboratory Fee Schedule: CLFS Reporting — CMS (accessed 2026-10-11)
  2. CMS opens new resources ahead of 2026 PAMA reporting window — Association for Diagnostics & Laboratory Medicine (The Lab Advocate) (2026 (March 1, 2026))
  3. CY 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F) fact sheet — CMS (2025 (October 31, 2025))
  4. CY 2027 Medicare Physician Fee Schedule Proposed Rule fact sheet — CMS (2026 (July 14, 2026))
  5. Modifier 26 (JF Part B) — Noridian Healthcare Solutions (Medicare contractor) (2025 (last updated May 9, 2025))
  6. SE0587: Multiple Procedure Reduction of the Technical Component (TC) of Certain Diagnostic Imaging Procedures — CMS (2005 (posted December 22, 2005))
  7. 42 CFR 415.102 Conditions for fee schedule payment for services of physicians in providers — eCFR (current (up to date as of 10/08/2026))
  8. 42 CFR 415.130 Conditions for payment: Physician pathology services — eCFR (current (up to date as of 10/08/2026))
  9. 42 CFR 414.510 Laboratory date of service for clinical laboratory and pathology specimens — eCFR (current (up to date as of 10/02/2026))
  10. Laboratory Date of Service Policy — CMS (accessed 2026-10-11)
  11. Medicare NCCI Policy Manual, Chapter 10: Pathology and Laboratory Services (CPT 80000-89999), revision date 1/1/2026 — CMS (2026)
  12. 42 CFR 410.32 Diagnostic x-ray tests, diagnostic laboratory tests, and other diagnostic tests: Conditions — eCFR (current (up to date as of 10/08/2026))
  13. 42 CFR 493.1241 Standard: Test request — eCFR (current (up to date as of 10/08/2026))
  14. 42 CFR 493.3 Applicability — eCFR (current (up to date as of 10/08/2026))
  15. Clinical Laboratory Improvement Amendments (CLIA) — CMS (accessed 2026-10-11)
  16. Medicare Claims Processing Manual, Chapter 16: Laboratory Services (Rev. 13746, issued 04-17-26) — CMS (2026)
  17. Tips to prevent RUC CO 16 — First Coast Service Options (Medicare contractor) (2025 (March 12, 2025))
  18. New process for pathology, laboratory and other codes — First Coast Service Options (Medicare contractor) (2026 (page dated September 8, 2026))
  19. Advance Beneficiary Notice (ABN) — Noridian Healthcare Solutions (Medicare contractor) (2026 (last updated March 23, 2026))
  20. MM14536: Laboratory NCD Edit Software October 2026 Update — CMS (MLN Matters) (2026 (released July 7, 2026))
  21. Billing and Coding: Molecular Pathology and Genetic Testing (A58917) — CMS Medicare Coverage Database (Novitas Solutions) (2026 (revision R23 effective 07/01/2026))
  22. MolDX: Molecular Diagnostic Tests (MDT) (L35160) — CMS Medicare Coverage Database (Noridian Healthcare Solutions) (2026 (revision R18 effective 02/05/2026))
  23. Collect Data to Fight Increased Denials and Documentation (presentation, May 2, 2023) — College of American Pathologists (2023 (data through 2021))
  24. Business Associates — HHS Office for Civil Rights (accessed 2026-10-11)
  25. Minimum Necessary Requirement — HHS Office for Civil Rights (accessed 2026-10-11)
  26. 45 CFR 164.312 Technical safeguards — eCFR (current (accessed 2026-10-11))
  27. CPT 88305 and CPT 88307 code pages — AAPC (accessed 2026-10-11)