
Pathology CPT codes describe specimen exams, stains, consultations and molecular tests. Surgical pathology uses 88300-88309 (gross only up to the most complex level), 88321-88325 cover consultations on referred slides, and modifiers 26 and TC split the physician reading from the technical work. Units depend on the code: per specimen, per stain or per antibody.
This guide replaces two older RCM Finder posts on the same topic and corrects several code descriptions that were wrong in them. It is written for practice managers, billers and pathology groups. For the specialty view, see our pathology billing and RCM page.
Key takeaways
- The 88300-88309 codes are levels of surgical pathology, assigned per specimen, and gross-only 88300 is not reported with the higher levels for the same specimen.
- CPT 88321 is a consultation on slides prepared elsewhere; 88323 is for referred material that needs new slides; 88325 is the comprehensive review.
- Unit rules differ by code family: per specimen, per stain, per antibody, or one unit regardless of specimens.
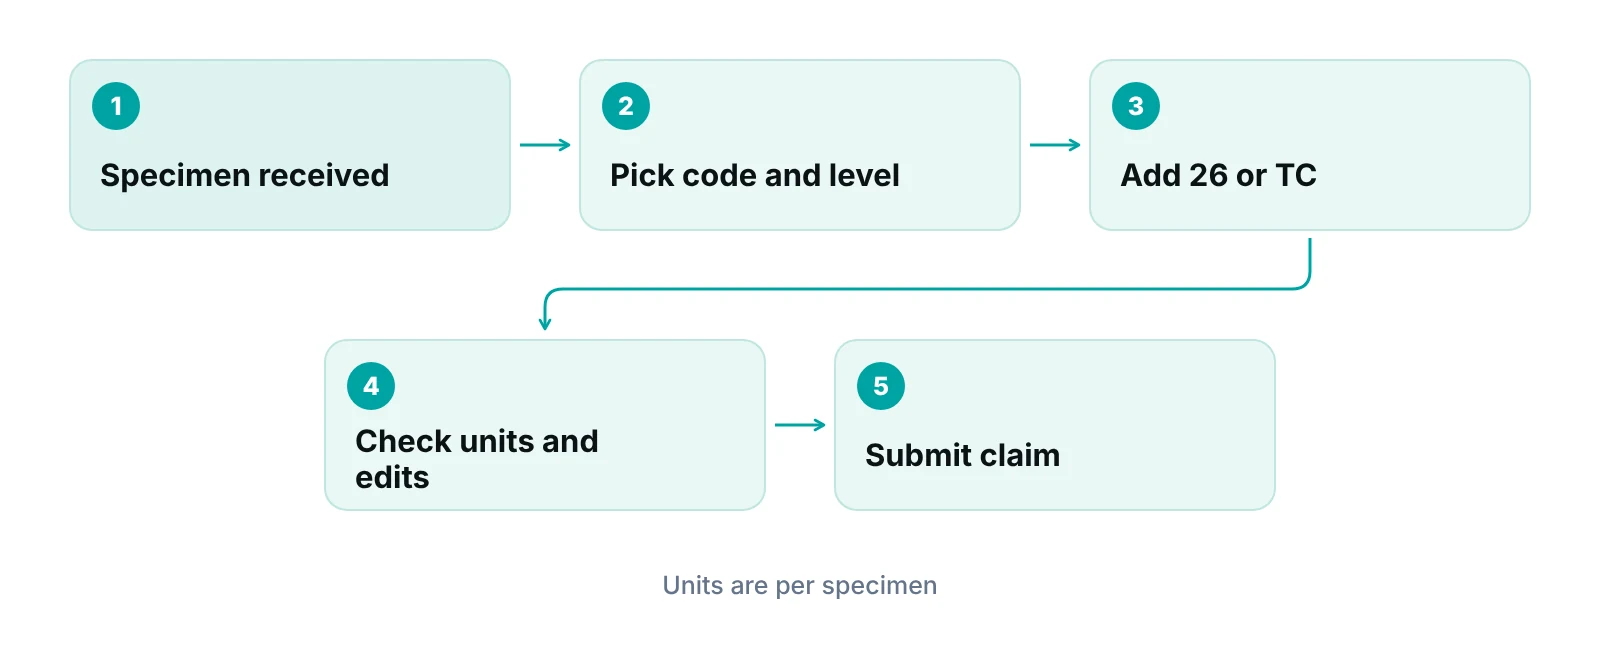
- Modifier 26 and TC apply only to codes that split into professional and technical parts. Check the fee schedule indicator first.
- Modifiers do not raise a payment. They describe what was done so the claim pays the right component.
What pathology CPT codes are and how they are organized
Pathology CPT codes are the five-digit codes that tell a payer which pathology service was performed on a specimen. CPT is published by the American Medical Association (AMA) and sorted into Category I, II and III codes, according to a CPT code set reference. Category I reports services and procedures, Category II reports performance measures, and Category III is for temporary codes covering emerging technology.
Pathology and Laboratory is a section of Category I. The reference above places proprietary laboratory analyses (PLA codes, which end in the letter U) after code 89398, which marks the end of the standard section. Most pathologist billing sits in the 88xxx block, with some work in the 81xxx molecular block.
Two points to keep in mind. First, the AMA owns the CPT descriptors, so this guide gives plain-language summaries, not the official wording. Check the current-year code book before you build a charge master. Second, a code is only half of a claim line. Whether it needs modifier 26 or TC, how many units are allowed and which codes can sit beside it all change what a payer will pay. If your practice is deciding who should own that work, our medical billing services page explains the options.
What is the difference between CPT and HCPCS here?
CPT codes come from the AMA. HCPCS Level II codes, such as G0416 for prostate needle biopsies, come from CMS. Pathology claims to Medicare often carry both. Our guide to HCPCS vs CPT in medical billing covers the difference.
Surgical pathology codes 88300-88309: what the levels mean
The 88300-88309 codes are levels of surgical pathology, and the level reflects the type of specimen, not how long the pathologist took. The gross-only code is 88300. The CMS NCCI Policy Manual, Chapter 10 says gross examination is part of the gross and microscopic exam reported with 88302-88309, so 88300 is not reported with those codes for the same specimen.
Level 88304 and above include a microscopic exam. The table below gives common examples as listed by a coding reference. The AMA code book holds the authoritative specimen list that assigns each tissue to a level, so confirm any specimen you are unsure about there. 88305 is the code many biopsies land on, which is why it is the most commonly searched of the group.
| CPT code | Level | Typical specimen examples | Billing note |
|---|---|---|---|
| 88300 | I (gross only) | Calculus, foreign body, teeth | Not reported with 88302-88309 for the same specimen |
| 88302 | II | Appendix removed incidentally, fallopian tube for sterilization, hernia sac | Gross and microscopic exam |
| 88304 | III | Gallbladder, skin cyst or tag, abscess | Gross and microscopic exam |
| 88305 | IV | Colon or colorectal polyp biopsy, skin biopsy, cervix biopsy, lymph node biopsy | Prostate needle biopsies to Medicare use G0416, not 88305 |
| 88307 | V | Breast excision with margins, thyroid, partial nephrectomy | Bone biopsy may be reported with 88307 under NCCI policy |
| 88309 | VI | Colon resection for tumor, radical prostatectomy, lung lobectomy for tumor | Most complex level |
Source: specimen examples from a coding reference (codingahead.com, accessed 2026-10-14); gross-only and bundling rules from CMS NCCI Policy Manual, Chapter 10 (2026). Confirm levels in the current AMA CPT book.
Two billing rules matter more than the level list. One, the unit of service for gross and microscopic surgical pathology is the specimen. Separate specimens are usually in separate containers, and several biopsies of the same polyp are usually one specimen. Two, the NCCI manual says all prostate needle biopsy specimens from one patient are reported with one unit of HCPCS G0416 instead of 88305. Billing a unit of 88305 per core is a common way to trigger a Medicare denial.
CPT 88321 description: pathology consultation codes 88321-88325
CPT 88321 is a consultation and report on referred slides that were prepared elsewhere. In short, a pathologist reviews slides made at another facility and writes a report. The CMS NCCI Policy Manual, Chapter 10 describes 88321-88325 as surgical pathology consultation services to review slides, tissues or other material.
The three codes differ by how much work the consulting pathologist does, as summarized in a university pathology handbook:
- 88321: consultation and report on referred slides prepared elsewhere.
- 88323: consultation and report on referred material that requires preparation of slides. This is the opposite of an advisory service with no slide work, which an older RCM Finder post wrongly said.
- 88325: comprehensive consultation with review of records and specimens, with a report on the referred material.
The NCCI manual sets four rules that catch billers out:
- Each code is reported with one unit regardless of the number of specimens.
- Do not report them when a pathologist in the same provider group has also examined and reported the material (a second opinion inside the group).
- They are not reported with a face-to-face evaluation of a patient.
- Special stains and IHC (88312, 88313, 88341, 88342, 88344) can be reported with them only if the consulting physician performs the staining and interprets the newly stained slides.
Medicare also allows only one unit of 88321, 88323 and 88325 per beneficiary on a date of service, and modifiers cannot be used to get around that limit.
“A consultation code describes work on someone else's material. If the same group already read the case, the claim line is probably a duplicate, not a consult.”
Units of service: special stains, IHC and molecular codes
Most payment errors in pathology are unit errors, not code errors. The unit of service changes by code family, so a single rule such as “one per slide” will be wrong for some of them.
| Code family | What counts as one unit | Source rule |
|---|---|---|
| Surgical pathology, gross and microscopic (88302-88309) | One specimen | NCCI Ch. 10, section M.8 |
| Consultations (88321, 88323, 88325) | One unit regardless of the number of specimens | NCCI Ch. 10, sections L.2 and M.3 |
| Special stains (88312-88319) | Each stain; not more than one unit for a stain run on a single tissue block; controls are not separate units | NCCI Ch. 10, section M.9 |
| IHC (88341, 88342, 88344) | Each single or multiplex antibody stain procedure per specimen; an antibody cocktail that cannot be interpreted separately is one unit | NCCI Ch. 10, section M.9 |
| Prostate needle biopsy (HCPCS G0416) | One unit for all needle biopsy specimens from one patient | NCCI Ch. 10, section L.10 |
| Quantitative or morphometric IHC (88360, 88361) | One unit per specimen; not reported with 88341, 88342 or 88344 | NCCI Ch. 10, section M.10 |
Source: CMS NCCI Policy Manual for Medicare Services, Chapter 10 (2026).
For IHC, a stain with several antibodies that produces a single reportable result is not a multiplex stain. It is reported with a single-antibody code. Qualitative grading of an IHC stain is also reported with the IHC codes, according to the same chapter.
Molecular pathology codes
The 81xxx molecular codes need a different habit. Many are specific to one gene or one test, and others are tiered or unlisted. Do not choose one from a summary table, including the tables in older versions of this post, which described several of them too generally. Look the code up in the current AMA CPT book and the payer policy for that test. Our laboratory billing and coding guide and the post on documentation rules for pathology and laboratory claims go further on lab claims.
Pathology billing modifiers: 26, TC, 91 and 59
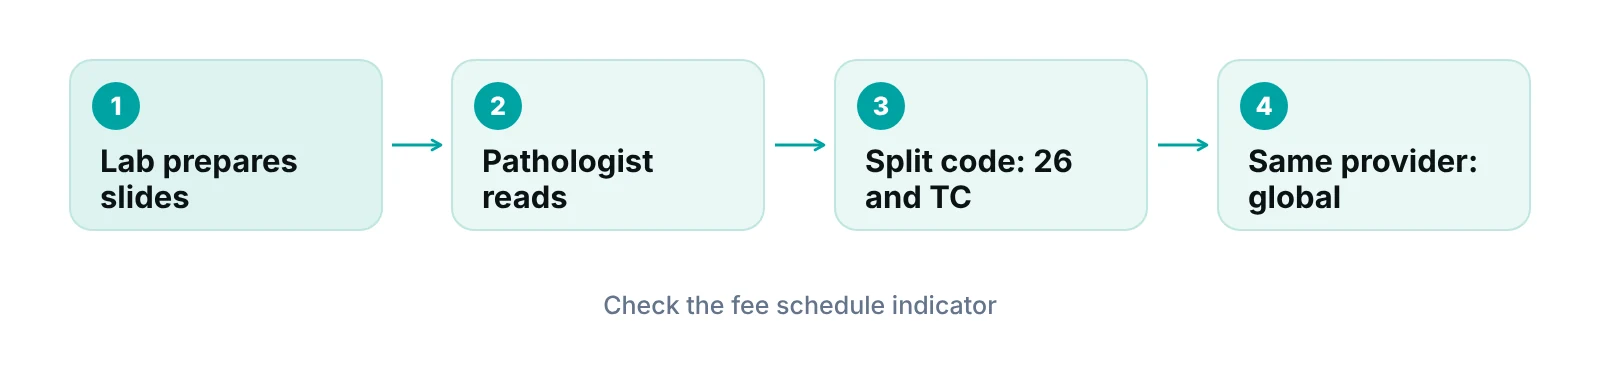
Modifier 26 means the professional component, which is the physician interpretation. TC means the technical component, which is the laboratory work and equipment. Modifiers describe what was billed; they do not raise the rate. A global claim pays for both parts, and a split claim pays each part to the party that did it.
| Modifier | What it tells the payer | When it fits | Watch for |
|---|---|---|---|
| 26 | Professional component only: the physician interpretation | Code is split into professional and technical parts and the pathologist bills the reading | Not used with E/M or anesthesia codes |
| TC | Technical component only: slide preparation, staining, equipment | Code is split and the lab bills the technical part | Independent labs cannot bill the TC for hospital inpatients or outpatients |
| None (global) | Both parts, billed together | The same provider performed the whole service | Do not add 26 or TC to a global service |
| 91 | Repeat clinical laboratory test on the same day | Medically necessary repeat of a lab test, not to confirm an initial result | Needs documented reason; see the modifier 91 guide |
| 59, XS, XU | A distinct service, separate site or different method | Documented separate specimens, sites or methods where NCCI otherwise bundles | Use the most specific modifier; payers watch 59 closely |
Source: Noridian Medicare modifier 26 page; Medicare Claims Processing Manual Chapter 12 section 60 (via CMS transmittal R2714CP); CMS NCCI Policy Manual Chapter 10 (2026), sections C, H.3, L.1, L.3.
Modifier 26 fits only codes that Medicare splits. A Medicare administrative contractor page on modifier 26 tells billers to check the Medicare Physician Fee Schedule indicator to see whether a code is split. It also says to bill the 26 and TC separately when they were furnished at different enrolled practice locations, and to bill no modifier when the same provider performed the whole global service.
Setting matters for technical components. The Medicare Claims Processing Manual, Chapter 12 says the physician fee schedule can pay the professional component of a pathology service for hospital patients, but not the technical component in institutional settings. Since July 1, 2012, an independent laboratory cannot bill the technical component of a pathology service for a hospital inpatient or outpatient. Only the hospital may bill it.
On modifiers 59 and 91, the NCCI manual says repeat panel testing must be medically reasonable and necessary and cannot be done to confirm initial results. It also allows 59 or XS for two separately necessary bone biopsies and for different specimens in cytopathology, and 59 or XU when two methods are both needed and documented. Our guides on modifier 91, modifiers 25 vs 59 and modifier 59 go deeper.
Older advice to drop
Earlier versions of this page listed modifiers 24 and 79 as common pathology modifiers. They are not pathology-specific, and no fetched source supports them here, so they have been removed.
Why pathology claims get denied, and what to check before submission
Pathology denials usually trace back to the same few gaps: a missing or wrong modifier, units that do not match the specimen count, a code combination the NCCI edits block, or a service billed by the wrong party for the setting. The checks below target those gaps. No single denial-rate figure fits every practice, so measure yours by payer instead of relying on a published average.
- Registration and eligibility. Capture accurate patient and insurance details, and confirm coverage for the date of service. Our guide to insurance verification explains the process.
- Code and level. Assign the code from the final pathology report, not from the requisition. Confirm the level against the specimen.
- Component and modifier. Decide global, 26 or TC based on who did the work and where.
- Units and edits. Check units against the rules in the table above, and review NCCI edits for the code pair.
- Submit, then follow up. Track unpaid claims and appeal by denial reason. Our posts on clean claims and denial management cover this stage.
Documentation supports every step. The report should name the specimen, the procedures and stains performed and the findings, so a reviewer can match each billed unit to a line in the record.
When to get help with pathology billing
Pathology groups often bring in outside billing support when the mix of professional claims, technical claims, hospital contracts and send-out consults becomes hard to track in-house. Whether it fits depends on volume and staffing, not on a rule. If you consider it, ask any vendor:
- Which of your claims are professional only, technical only and global, and how are they billed today?
- How does the team check units for stains, IHC and prostate biopsies before submission?
- Will the vendor sign a Business Associate Agreement before accessing patient data?
- What reporting will you receive on denials by payer and by reason?
- Do they work inside the EHR or lab system you already use?
Want a second set of eyes on your pathology claims?
Request a free practice audit. We review how your pathology claims are coded and billed, and tell you what we find.
Our recommendations
- Keep a current-year code book and a payer sheet. Check descriptors and specimen levels in the AMA CPT book each year, and record where each payer differs from Medicare.
- Bill units from the report, not the requisition. Count specimens, stains and antibodies from the final report so each unit ties to a line in the record.
- Check the fee schedule indicator before adding 26 or TC. Only split codes take these modifiers, and the setting decides who may bill the technical part.
- Treat modifier 59 as a last resort. Use XS or XU when they describe the situation, and document why the service was separate.
- Audit denials by code and modifier each quarter. Patterns by payer and code show whether the problem is coding, units or setup.
- Do not copy a code list from a summary. Descriptors and levels change, and a general table, including older versions of this one, can be wrong for a specific code.
Bottom line
Pathology CPT codes follow unit and modifier rules that differ by code family, so read the rule before you pick the code. If you want help reviewing how your claims are built, see our pathology billing page or ask about denial management services, and use the revenue calculator to size the issue.
Frequently asked questions
What is CPT code 88321?
CPT 88321 is a consultation and report on referred slides prepared elsewhere. A pathologist reviews slides from another facility and writes a report. It is one unit regardless of the number of specimens, and Medicare allows one unit per beneficiary per date of service. If the lab prepares new slides from the referred material, 88323 applies instead.
What is the difference between 88321, 88323 and 88325?
88321 covers referred slides made elsewhere. 88323 covers referred material that needs new slides prepared. 88325 is a comprehensive consultation with review of records and specimens. Per the NCCI manual, none of them is reported for a second opinion inside the same provider group or with a face-to-face patient evaluation.
What do the 88300-88309 levels mean?
They are levels of surgical pathology, assigned by specimen type. 88300 is gross examination only, and 88302-88309 include gross and microscopic exam at rising complexity. The unit is the specimen. Confirm any specimen’s level in the AMA CPT book, since the code book holds the authoritative list.
When do I use modifier 26 versus TC?
Use 26 when the pathologist bills only the interpretation, and TC when the lab bills only the technical work, on a code that is split. If one provider did all of it, bill global with no modifier. Check the Medicare fee schedule indicator, and remember a hospital bills the TC for its own patients.
Do modifiers increase pathology reimbursement?
No. Modifiers describe the service so the claim pays correctly. Modifier 26 and TC divide a payment between the reading and the technical work, and 59, XS or XU explain why a service is separate. Using one without support can trigger a denial or audit.
How many units can I bill for special stains and IHC?
Special stains are billed per stain, with no more than one unit for a stain on a single tissue block. IHC is billed per single or multiplex antibody stain procedure per specimen, and a cocktail that cannot be separately interpreted is one unit. Check the payer’s edits as well.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Medicare NCCI Policy Manual, Chapter 10 (Pathology and Laboratory Services) — CMS (2026)
- Medicare Claims Processing Manual transmittal R2714CP (Ch. 12 section 60; Ch. 16 section 80.2.1) — CMS (transmittal text, accessed 2026-10-14)
- Modifier 26 — Noridian Healthcare Solutions (Medicare Part B contractor) (accessed 2026-10-14)
- Surgical Pathology Consultations — University of Iowa Hospitals and Clinics Pathology Handbook (2026)
- CPT Code 88305 reference — Coding Ahead (secondary coding reference) (accessed 2026-10-14)
- CPT Code Set overview — FindACode (secondary coding reference) (accessed 2026-10-14)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT is a trademark of the American Medical Association, and the code descriptions here are our own summaries. Payer rules and contracts vary, and code sets change each year. Check the current AMA, CMS and payer sources before you bill.
