

Clean claims in medical billing are claims a payer can process and pay without asking the practice for anything more. Medicare contractors and state Medicaid rules word the definition differently, so your clean claim rate is only useful if you choose one definition, measure it the same way every month, and fix errors before submission.
Almost every billing team says it wants clean claims. Fewer can say what their payer means by the term, or how their own clean claim rate is calculated. Without those two answers, a target like “95%” is a number on a slide, not a control.
This guide covers the definition, the difference between a rejected, a returned and a denied claim, the formula, and the fixes to try first. For step-by-step handling, see our clean claim submission process guide; for rules and tools, see our guide to claim scrubbing.
Key takeaways
- A clean claim is one the payer can process without more information from you; the exact wording differs between Medicare contractors, Medicaid and commercial plans.
- A claim that is rejected or returned as unprocessable before adjudication is not the same as a denial, and it is counted differently.
- Pick one clean claim rate definition, write it down and track it monthly; do not rely on a borrowed benchmark.
- Most of the work happens before submission: complete patient, provider and coverage data, and a check against payer rules.
- Track rejections, denials and resubmissions separately so you can see which step is leaking.
What is a clean claim in medical billing?
A clean claim is one the payer can adjudicate without coming back to you. It is accurate, complete and supported, so nothing stops it from being paid or denied on its merits.
The wording is not uniform. CGS Medicare, a Medicare Administrative Contractor, describes it as a claim that “does not have any circumstance or defect that would inhibit timely payment,” and says a claim for which it has requested medical records is not considered clean. The Medicaid regulation at 42 CFR 447.45 defines it as one that can be processed without obtaining additional information from the provider.
| Source | What it says | What it means for your team |
|---|---|---|
| Medicare contractor (CGS) | A claim with no circumstance or defect that would inhibit timely payment; correct, complete and containing all information the contractor requires. A claim for which records were requested is not clean. | Missing data and record requests both break cleanliness, even if the claim was filed on time. |
| Medicaid (42 CFR 447.45) | A claim that can be processed without obtaining additional information from the provider of the service. | A follow-up question from the state agency means the claim was not clean. |
| Commercial plans | Defined in each provider contract and, in many states, in prompt-payment law. | Read your contract and state rules; do not assume the Medicare wording applies. |
Source: CGS Medicare (accessed 2026); eCFR, 42 CFR 447.45 (current as of 2026)
Two points follow. First, “clean” describes the claim’s condition when the payer receives it, not whether it is eventually paid. Second, a clean claim can still be denied for a covered-benefit or medical-necessity reason. Clean means processable, not guaranteed.
Clean, rejected, returned and denied: what is the difference?
A rejected claim never reached a payment decision; a denied claim did. Mixing them up inflates your denial rate or hides rework that costs staff time.
Medicare contractors describe a claim “returned as unprocessable” as one that does not meet the criteria to be considered a claim. It is not denied, so it has no appeal rights, and the fix is to correct it and submit again. Commercial payers and clearinghouses use their own vocabulary, so ask each one how it labels these outcomes. Our guides to clearinghouse rejection codes and the CO-16 denial code explain what the codes on each side look like.
| Outcome | What happens | Typical next step |
|---|---|---|
| Rejected by clearinghouse or front-end edits | Errors are caught before the claim goes to the payer for adjudication (this is the stage where a scrubber or clearinghouse reports problems). | Correct and resubmit; no payer decision exists yet. |
| Returned as unprocessable (Medicare) | Does not meet the criteria to be considered a claim; it is not denied and is not afforded appeal rights. The remittance carries message MA130. | Correct the errors and submit a new claim. |
| Denied | The payer processed the claim and decided not to pay all or part of it. | Review the reason code, then appeal or correct and resubmit as the payer allows. |
Source: Noridian Medicare (accessed 2026), claim submission terminology. Terms and appeal rights vary by payer.
Count each outcome on its own line
Report rejected, returned, denied and resubmitted claims as separate counts. If they are blended into one number, you cannot tell whether the fix belongs at the front desk, in coding or in the claim file.
Why clean claims matter for cash flow
Clean claims are paid on a predictable clock; unclean ones are not. Government payers publish that clock, which makes it easier to see what a clean claim buys you.
- Medicare: CGS says all Medicare Administrative Contractors have up to 30 days to process clean claims without paying interest, citing the CMS Medicare Claims Processing Manual, chapter 1, section 80.2.1.1. It also notes a 14-day payment floor, so a claim cannot be released sooner than 14 days after submission.
- Medicaid: the federal rule requires the state agency to pay 90 percent of clean claims from practitioners within 30 days of receipt and 99 percent within 90 days, for practitioners in individual or group practice or shared health facilities.
- Filing window: Medicare claims must be submitted no later than 12 months after the date of service, per First Coast Service Options. Commercial limits differ; see our state-by-state billing time limits.
Those timelines apply to clean claims. A claim that needs more information from you stops the clock while you answer, and a denial starts a longer path through denial management.
How common are denials? KFF found that insurers on HealthCare.gov denied 20% of in-network claims in 2023, with a range from 1% to 54% across insurers. That is marketplace data, not a figure for every payer or specialty, and KFF notes reason data is limited: only some plans reported reasons. Fewer than 1% of denied claims were appealed.
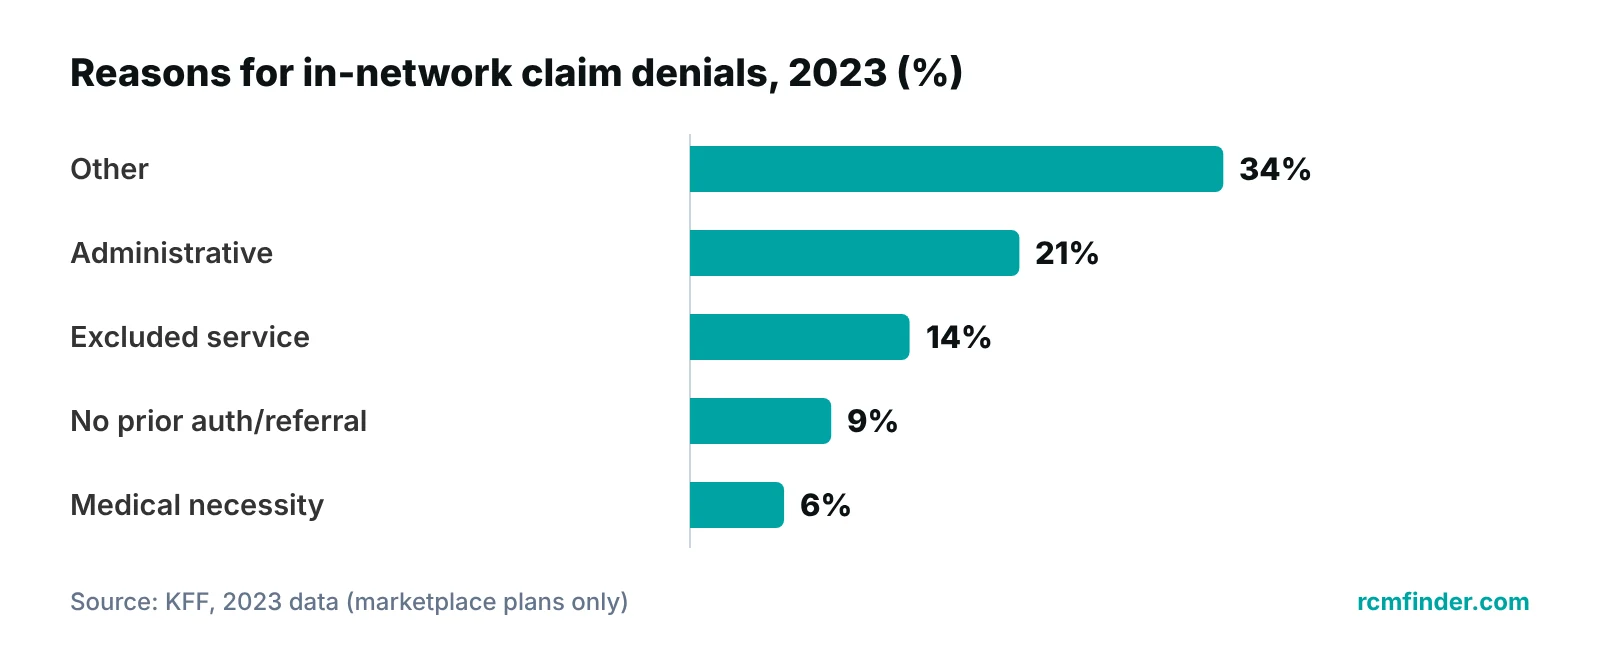
Read the chart carefully. The largest bucket is “other,” which tells you how little standardized reason data exists. Treat it as direction, not as a benchmark for your practice.
What makes a claim unclean?
Most unclean claims fail on basic data, not on complex coding. CGS publishes the top return-to-provider categories for Part B claims, and they are mostly ordinary fields: a procedure code that is invalid on the date of service, missing or invalid ordering or referring provider details, a mismatch between the patient’s Medicare ID and name, and missing or invalid patient or group practice information. See the CGS error list.
| Error source | Examples | Best place to catch it |
|---|---|---|
| Patient and coverage data | Name or ID mismatch, missing or inactive coverage, wrong payer order | Front desk at check-in; eligibility check before the visit |
| Provider data | Missing or invalid rendering, ordering/referring or group information | Billing setup; payer enrollment records |
| Coding and charges | Procedure code invalid for the date of service, bad code and modifier combination | Coder review and scrubber rules before submission |
| Authorization and referral | Required approval not obtained or not attached | Scheduling and prior authorization workflow |
| Documentation | Records requested by the payer to support the service | Clinical documentation review before billing |
Source: CGS Medicare Part B return-to-provider categories (page updated 2026); RCM Finder analysis. The CGS list is regional and undated, so use it for the kinds of errors, not for rates.
Some failures are structural. A wrong entity or identifier can stop a claim at the front end; our guide to entity code rejections shows what that looks like. How the claim travels from your system to the payer matters too, and our overview of the EDI claim flow walks through those handoffs.
“If the same error shows up three times a week, it is not a billing mistake any more. It is a process that nobody owns.”
How do you calculate a clean claim rate?
Clean claim rate is clean claims divided by claims submitted, for the same period. The hard part is choosing what counts as “clean,” so decide that first and write it down.
Choose a definition
- First-pass acceptance: claims accepted by the payer or clearinghouse without a rejection, divided by claims submitted.
- First-pass payment (no-touch): claims paid or adjudicated on the first submission with no rework, divided by claims submitted.
- Initial denial rate (the inverse view): HFMA’s Claim Integrity Task Force defines initial denial claims as only the first denial on a given claim, and divides total initial denial claims by total claims submitted. It also defines a dollar version using gross charges.
HFMA’s guidance gives a useful rule even if you pick a different metric: count a claim once, at its first outcome, so later appeals do not blur the number. (HFMA)
Worked example (illustrative numbers only)
A practice submits 500 claims in a month. 20 are rejected before adjudication, and 40 of the 480 accepted are denied on first adjudication. Under first-pass acceptance, the rate is 480 / 500 = 96%. Under first-pass payment, the rate is 440 / 500 = 88%. Same month, same claims, two different answers. This is why the definition has to be written down.
You may see “95% or higher” quoted as the industry standard for clean claim rate. We could not find a primary source that sets that figure, and it depends on which definition is used, so we do not treat it as a rule. Track your own trend by payer and by specialty instead.
How to improve your clean claim rate
Fix the earliest step that can prevent the error, then measure again. Work in the order below, because upstream fixes remove more rework than downstream ones.
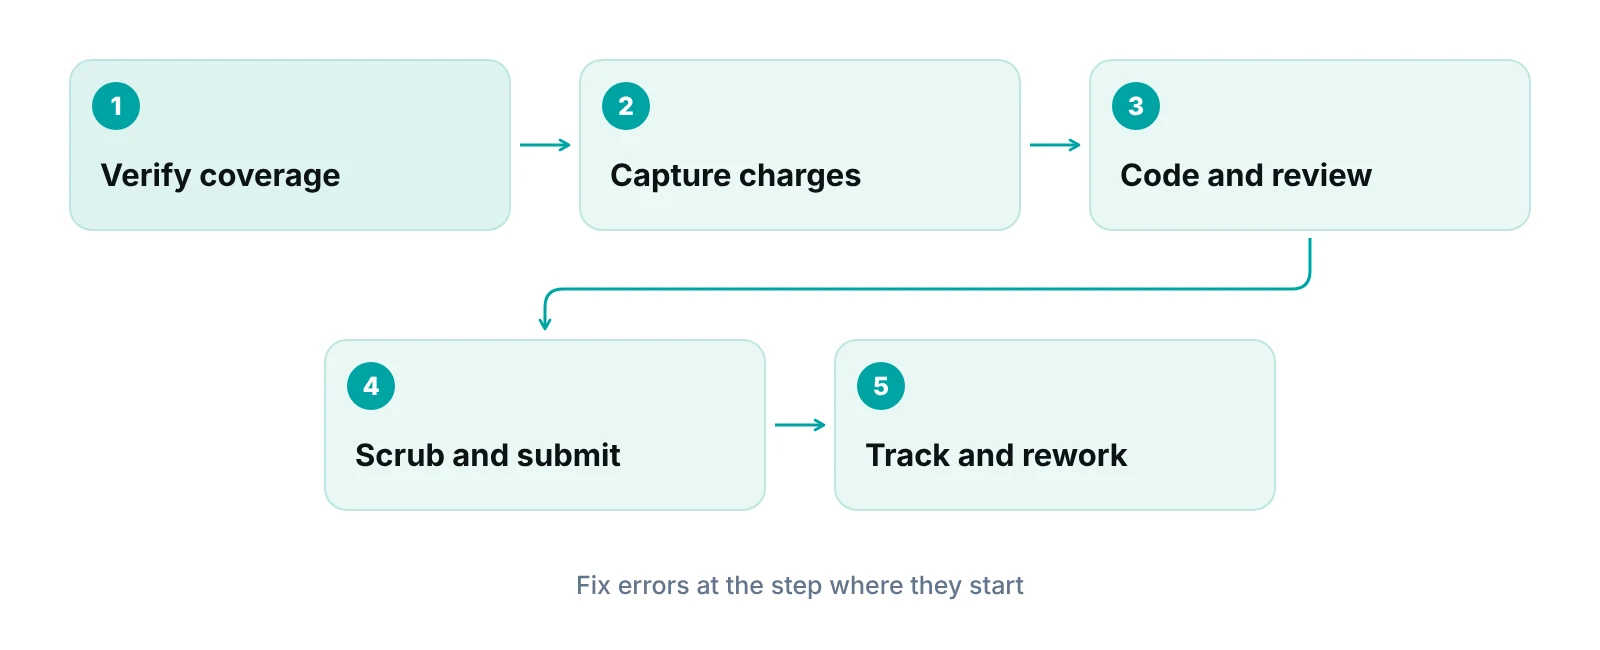
- Pull your last 90 days of rejections and denials. Group them by cause (patient data, provider data, coding, authorization, documentation) and by payer. Do not start with tools; start with what is actually failing.
- Tighten intake and coverage checks. Capture the card, ID, plan and payer order at scheduling and check-in. Errors born at the front desk are the cheapest to prevent.
- Standardize charge capture and coding review. Agree who confirms codes, modifiers and diagnosis links before billing, and keep payer rule changes in one shared place.
- Add pre-submission edits. Run claims through rules that flag missing fields, invalid combinations and payer-specific edits. Our guide to claim scrubbing covers what to check.
- Work rejections the same day. A rejected claim has no payer decision yet, so it is the cheapest to fix. Assign an owner and a deadline.
- Review monthly and update the rules. Re-run your error groups each month and retire or add edits based on what changed.
Some patterns are specific to a specialty, for example claims that rely on prior authorization or modifier use; see specialty-specific billing patterns before you copy another practice’s rules. If your team lacks the time, medical billing services can take on charge entry, submission and rejection follow-up, and a practice management system that tracks claims by stage can show you which stage each claim sits in and who owns it.
See where your claims are failing
Send us a sample of recent rejections and denials. We will group them by cause and show you which step to fix first. No obligation.
What to ask before you hand off claim cleanup
Whether you fix this in house or with a partner, ask for the same things. A clear answer to each question below tells you whether the work will be measurable.
- Which definition of clean claim rate will you report, and how do you count a resubmitted claim?
- Do you separate rejected, returned and denied claims in reporting?
- Who owns each error category, and what is the deadline to work a rejection?
- Can I see the edits applied before submission and add payer-specific ones?
- Will you sign a Business Associate Agreement before touching patient data, and what access controls and audit logs do you keep?
If the answers are “a percentage” and “we handle it,” keep asking.
Estimate what rework is costing you
Use our revenue calculator to put a number on slow or denied claims in your own practice.
Our recommendations
- Write down your definition. We would rather see a modest rate on a strict definition than a high rate on a loose one. Put the definition in your billing policy.
- Report outcomes separately. Show rejected, returned, denied and resubmitted claims as four lines. It is the fastest way to find where the leak is.
- Fix intake before coding. Demographic and coverage errors are common and cheap to prevent. Start at check-in.
- Work rejections inside one business day. There is no payer decision yet, so every day of delay is pure waiting.
- Review by payer, not only in total. One payer’s edits can distort an overall rate. Split the report so you see it.
A practice management system built around claims, not charts.
RCM Finder's portal tracks every claim by stage with an owner, runs data-completeness checks before submission and applies workflow rules to hold or advance claims. It is a claims system, not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
A clean claim is one the payer can process without asking you for more. Define it, measure it one way, and fix errors at the step that creates them. If rework is piling up, our denial management services team can review your rejections and denials with you, and our medical billing services cover submission and rejection follow-up with the EHR you already use.
Frequently asked questions
What is a clean claim in medical billing?
A clean claim is one the payer can process without asking the practice for additional information. Medicare contractors describe it as having no defect that would inhibit timely payment, and the Medicaid rule says it can be processed without further information from the provider. Clean means processable, not guaranteed to be paid.
What is the difference between a rejected claim and a denied claim?
A rejected claim is stopped before adjudication because of errors, so no payment decision exists and you correct and resubmit. A denied claim was processed and the payer decided not to pay. Medicare also uses the term returned as unprocessable, which carries no appeal rights. Payers and clearinghouses label these differently, so confirm each one’s terms.
How do I calculate my clean claim rate?
Divide clean claims by claims submitted for the same period. First decide whether clean means accepted without rejection or paid on first submission without rework, because the same month can give two different rates. Count each claim once at its first outcome so appeals do not change the number.
Is 95% a good clean claim rate?
You will often see 95% quoted, but we could not find a primary source that sets it as a standard, and it depends on the definition used. A more useful approach is to track your own rate by payer and specialty over time and look for the direction of travel.
How long does Medicare take to pay a clean claim?
CGS states that Medicare Administrative Contractors have up to 30 days to process clean claims without paying interest, and that a claim cannot be released sooner than 14 days after submission. Actual timing depends on the contractor, claim type and payment method, so check your own contractor’s guidance.
Does a clean claim guarantee payment?
No. A clean claim is processable, but it can still be denied for reasons such as a non-covered service or lack of medical necessity. Clean claims reduce avoidable rework and delay, but coverage and documentation still decide the outcome.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Payment timeframes for clean claims — CGS Medicare (2026)
- 42 CFR 447.45 Timely claims payment — eCFR / HHS (2026)
- New provider roadmap: Claims submission — First Coast Service Options (2026)
- Incomplete or invalid claims processing terminology — Noridian Healthcare Solutions (2026)
- Claim Submission Error (CSE) Data — CGS Medicare (2026)
- Standardizing denial metrics — HFMA (n.d.)
- Claims Denials and Appeals in ACA Marketplace Plans in 2023 — KFF (2023)
Disclaimer: This article is educational and is not legal, coding or compliance advice. Payer rules, appeal rights and prompt-payment timelines vary by payer, contract and state; confirm them with each payer and your own advisers.
