
Medicare billing for chiropractors rests on one rule: Medicare covers only manual manipulation of the spine to correct a subluxation. Other services a chiropractor furnishes or orders are not covered, and maintenance care is not payable. Send each claim within one calendar year of the service date.
Most guides on this topic mix Medicare rules with general chiropractic billing advice. This one sticks to what CMS publishes: what Medicare covers, where the active-versus-maintenance line sits, how to build a claim and how long you have to file it. It draws on the Medicare Benefit Policy Manual, the Medicare Claims Processing Manual and the federal timely-filing regulation. It is general information, not coding or compliance advice.
Key takeaways
- Medicare covers only manual manipulation of the spine to correct a subluxation; other chiropractic services are not covered.
- Maintenance therapy is not payable, so your notes must show active, corrective care.
- Section 240 of Chapter 15 of the Benefit Policy Manual is the checklist for your documentation.
- Medicare claims generally must be filed within one calendar year of the date of service.
- Take modifier rules from your Medicare Administrative Contractor, not from a generic template.
What does Medicare cover for chiropractors?
Medicare covers one chiropractic service: treatment by manual manipulation of the spine to correct a subluxation, where state law allows it. That comes from the Medicare Benefit Policy Manual, Chapter 15, section 30.5. The same section says all other services a chiropractor furnishes or orders are not covered, including any other diagnostic or therapeutic service.
That narrow rule shapes every part of the billing process. A front desk that treats a chiropractic visit like a primary care visit will build claims Medicare cannot pay. The table below shows how the manual treats the services a chiropractic office usually deals with.
| Service | Medicare treatment | Billing consequence |
|---|---|---|
| Manual manipulation of the spine to correct a subluxation | Covered, if legal in the state where it is performed | The only chiropractic service Medicare pays for |
| Other diagnostic or therapeutic services furnished or ordered by the chiropractor | Not covered | Do not expect payment; tell the patient before the visit |
| X-ray used to show a subluxation | May serve as documentation; not separately payable | Keep it in the record, but do not bill it to Medicare for payment |
| Hand-held manual device used during a covered manipulation | Allowed; no separate payment | Do not bill the device as its own line |
| Maintenance therapy | Not medically reasonable or necessary; not payable | Needs a plan for how it is identified on the claim and discussed with the patient |
Source: CMS, Medicare Benefit Policy Manual, Chapter 15, section 30.5 (chiropractors’ services)
Two other points from the same chapter matter for practice owners. First, the chiropractor must be licensed or legally authorized by the state where the service is furnished. Second, chiropractors are not included in the manual’s opt-out definition of a physician or practitioner, so a chiropractor cannot opt out of Medicare and bill Medicare patients under a private contract (section 40.4). Medicare patients are billed within the rules above or not at all.
If you run a chiropractic office, our chiropractic billing and RCM page covers how we set up the full billing workflow around these rules, including payers other than Medicare.
Active care or maintenance care: where Medicare draws the line
Medicare pays for corrective treatment, not maintenance. The manual says chiropractic maintenance therapy is not considered medically reasonable or necessary. It defines maintenance therapy as a treatment plan that seeks to prevent disease, promote health and prolong and enhance quality of life, or maintain or prevent deterioration of a chronic condition.
The manual also describes the point at which care becomes maintenance: when further clinical improvement cannot reasonably be expected from continuing the treatment. At that point the care is supportive rather than corrective, and Medicare does not pay for it.
Why this is the first thing to audit
A visit that was once corrective can become maintenance care as a patient plateaus. If your charge entry sends every visit out the same way, the claim can misstate the nature of the care. Build a clinical check into your process, not just a billing check.
What the AT modifier is
The Medicare Claims Processing Manual, Chapter 12 names an AT modifier, labelled acute treatment, in its fee schedule rules (section 20.5). Chiropractic billers know it as the modifier that marks a visit as active, corrective care. Your Medicare Administrative Contractor (MAC) publishes the instructions for when it goes on a claim and which codes need it. Build your charge entry rule from those instructions, not from a general template or an old blog post.
Where the detailed rules live
The detailed coverage rules for chiropractic care sit in section 240 of Chapter 15 of the Benefit Policy Manual. The section headings alone tell you what Medicare expects a record to answer.
| Section | Topic | Question your record should answer |
|---|---|---|
| 240.1 | Coverage of chiropractic services | Is the service one Medicare covers at all? |
| 240.1.1 | Manual manipulation | Was the treatment manual manipulation of the spine? |
| 240.1.2 | Subluxation may be demonstrated by x-ray or physician’s exam | How was the subluxation shown? |
| 240.1.3 | Necessity for treatment | Why is this care needed, and is it active or maintenance? |
| 240.1.4 | Location of subluxation | Which spinal area is being treated? |
| 240.1.5 | Treatment parameters | What is the plan, and how often? |
Source: CMS, Medicare Benefit Policy Manual, Chapter 15, table of contents (section 240 headings)
Read section 240 in full before you write your documentation templates. The headings above are the structure; the text under each one holds the requirements your auditors and your MAC will apply.
How a Medicare chiropractic claim should move through your office
A clean Medicare chiropractic claim is built before the visit, not after it. Most denials we would expect here come from a gap between what the clinician did and what the claim says, so the workflow below puts a check at each handoff.
- Confirm the patient is on Original Medicare. Coverage rules differ for other plans, so do not apply this guide to a patient on a different plan type without checking.
- Tell the patient what Medicare will not pay for. Because only spinal manipulation is covered, x-rays, other therapies and ordered tests are not covered by Medicare. Tell the patient before the visit, in plain words, and ask your MAC how to document that notice.
- Record why the care is needed. Capture how the subluxation was shown, where it is, the treatment plan and whether the care is active or maintenance, using the section 240 headings as your template.
- Build the claim from the record. The services billed, the modifiers used and the diagnosis should all trace back to the note. Follow your MAC’s published chiropractic instructions for modifiers.
- Scrub before you send. A pre-submission check catches missing modifiers and mismatches. See our guide to claim scrubbing.
- Track every claim to payment, and work every denial. Unworked denials turn into write-offs once the filing window closes.
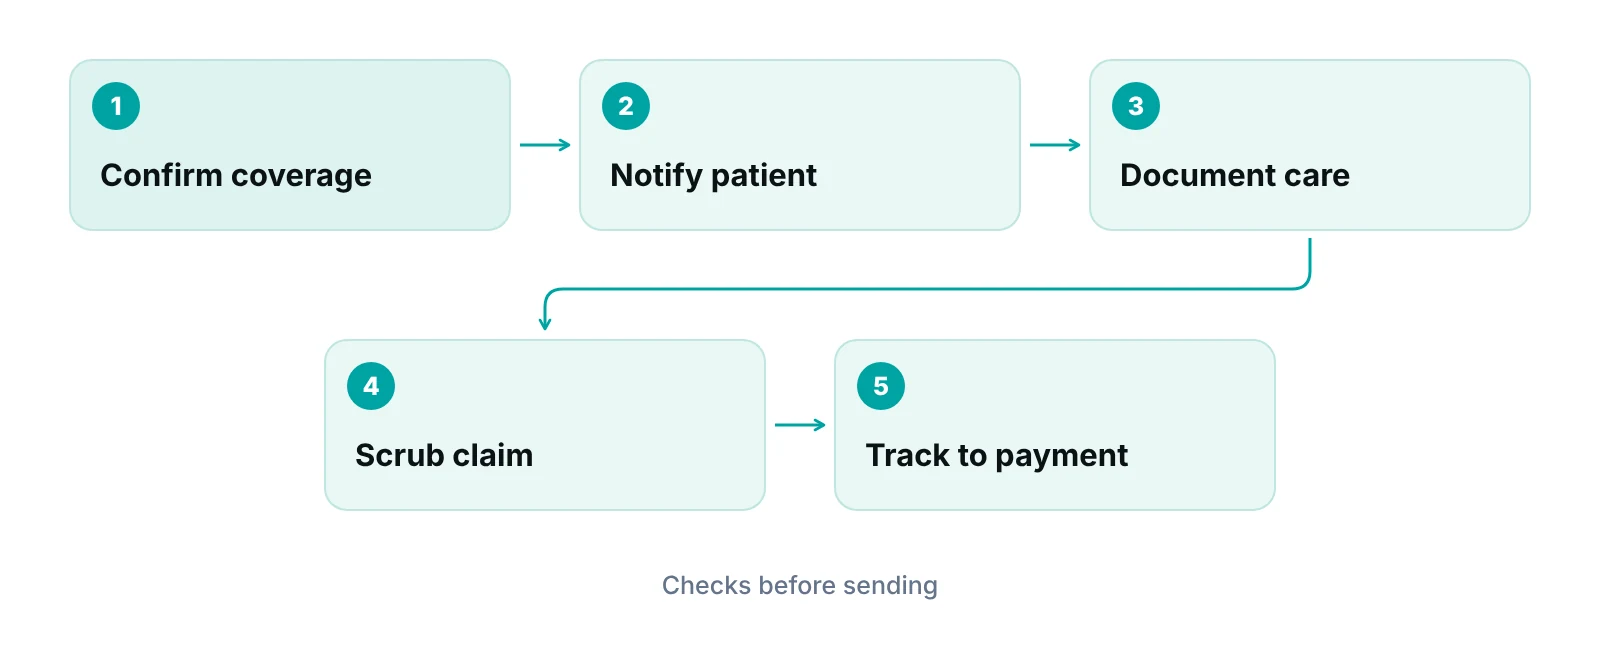
Our medical billing services team builds this kind of checklist into the claim flow, working inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth).
What your documentation has to support
Your note is the only evidence that the claim is true. Medicare treats the x-ray as supporting documentation, not a billable item, so the clinical record carries the weight of the claim.
Build your note template around the questions in section 240 rather than around what the software offers by default. A template that defaults to the same entry for every patient is a risk when the manual asks why this patient needs this care.
- How the subluxation was shown. Section 240.1.2 allows either an x-ray or a physician’s exam. State which one you used.
- Where it is. Section 240.1.4 asks for the location of the subluxation.
- Why treatment is necessary. Section 240.1.3 covers necessity. Active, corrective treatment and maintenance care should read differently in the note.
- The plan. Section 240.1.5 covers treatment parameters, so the note should set out the plan, not just the day’s visit.
Do not copy a note forward without reading it. In our view, a note that does not match the patient’s current condition is a weak record, whatever the template says.
Check your MAC's local policy
Your MAC may publish local coverage and billing articles that add detail to the national manual. We recommend reading your MAC’s chiropractic pages once a year and after any notice from them, then updating your templates.
How long do you have to file a Medicare chiropractic claim?
For services furnished on or after January 1, 2010, a Medicare claim must be filed no later than the close of the period ending one calendar year after the date of service (42 CFR 424.44). The practical consequence is simple: a claim filed after the deadline is at risk of not being paid unless an exception applies.
| Item | What the regulation says | What it means for your office |
|---|---|---|
| General rule | Claim filed within one calendar year after the date of service (services on or after January 1, 2010) | Track claims by service date, not by when they were sent |
| Weekend or federal holiday | If the deadline falls on a federal nonworkday, it moves to the next workday | Do not rely on this; file well before the deadline |
| Contractor or agent error | Extensions are possible when Medicare error or misrepresentation caused the delay, in defined circumstances | Keep records that show when and how you tried to file |
| Retroactive Medicare entitlement | Extensions are possible in defined circumstances for patients later found entitled | Ask the patient about changes in coverage |
Source: 42 CFR 424.44 (eCFR text as published by Cornell Legal Information Institute)
In practice, the one-year limit means the real risk is not the first submission. It is a denied or rejected claim that no one works for months. Age your open claims by service date and work the oldest first.
Where Medicare chiropractic claims go wrong
Based on the rules above, five points explain most avoidable denials and payment problems on Medicare chiropractic claims. We have not found a reliable published denial rate for chiropractic claims, so we do not quote one.
- Billing a service Medicare does not cover. Anything other than spinal manipulation is not covered, so claims for it will not pay.
- Billing maintenance care as active care. The manual says maintenance therapy is not payable.
- Missing or wrong modifiers. The claims manual names the AT modifier; follow your MAC’s rules for using it.
- Thin or copied notes. The record has to match section 240.
- Late or unworked claims. The one-year filing rule applies.
When a denial does arrive, read the remittance codes, fix the cause and resubmit or appeal within the deadlines on the notice. See our guide to medical billing denial management and our denial management services. For ideas beyond Medicare, our chiropractic reimbursement guide and chiropractic CPT codes and modifiers guide go deeper on codes and commercial payers.
Should you keep Medicare chiropractic billing in-house?
Keep it in-house if one person owns the Medicare workflow, knows the manual and your MAC’s rules, and has time to work denials. Look at outside help if billing is a side duty for your front desk, or if denials sit unworked.
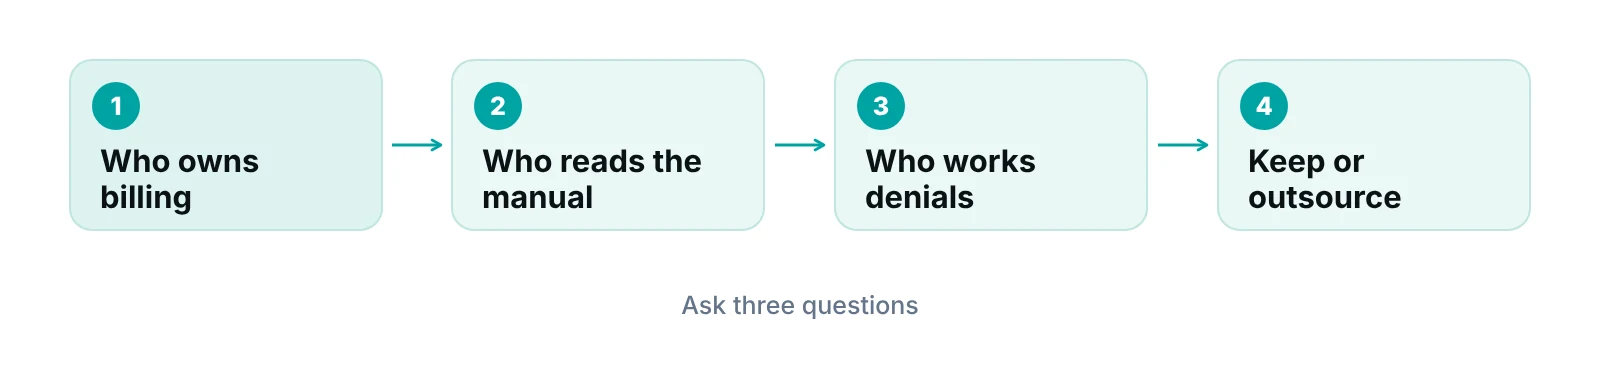
- In-house: you keep control and know the clinicians, but you carry the training, turnover and coverage risk.
- Outsourced: a specialist handles claims and follow-up, but you need clear reporting and a say in how Medicare rules are applied.
- Hybrid: the front desk handles intake and verification and a billing team handles claims and denials.
Whichever you choose, ask who is accountable for each step in the workflow above and how you will see it. For the wider Medicare picture, see our overview of Medicare fee-for-service claims.
Want a second pair of eyes on your Medicare chiropractic claims?
Send us your claim workflow and a sample of recent denials. We will review where the process could break, using the rules above. Pricing is quoted after the audit.
Our recommendations
- Read section 240 before you build templates. We would print the section 240 headings and make each one a required field or prompt in the chiropractic note.
- Separate active care from maintenance in your process. We would add a review point where the clinician confirms the nature of the care, so billing does not guess.
- Tell patients early what Medicare will not pay. We would script a short notice for the front desk covering x-rays, ordered tests and other non-covered services.
- Take modifier rules from your MAC, not from a template. We would save your MAC’s chiropractic instructions with a review date, and update charge entry rules when they change.
- Track by date of service. We would age open claims against the one-calendar-year filing limit and work the oldest first.
- Scrub before every submission. We would run a pre-submission check for modifiers and note-to-claim mismatches rather than fixing them after denial.
Bottom line
Medicare billing for chiropractors comes down to a narrow coverage rule, clear notes and a claim filed on time. Build your process around those three, check your MAC’s instructions for modifiers, and work every denial. If you want help, see our denial management services or our chiropractic specialty page, contact our team, or use our revenue calculator to see where claims may be stalling.
Frequently asked questions
What does Medicare cover for chiropractors?
Medicare covers treatment by manual manipulation of the spine to correct a subluxation, where state law allows it. All other services a chiropractor furnishes or orders are not covered, including other diagnostic or therapeutic services. A chiropractor’s x-ray can document a subluxation but is not separately payable.
Does Medicare pay for chiropractic maintenance care?
No. The Medicare Benefit Policy Manual says chiropractic maintenance therapy is not medically reasonable or necessary, so it is not payable. Maintenance therapy aims to prevent disease or maintain a chronic condition, rather than correct a problem. Your notes should show whether care is active or maintenance.
What is the AT modifier on a Medicare chiropractic claim?
The Medicare Claims Processing Manual names an AT modifier, labelled acute treatment. Chiropractic billers use it to show active, corrective care. Your Medicare Administrative Contractor publishes when it is required and for which codes, so follow those instructions rather than a general guide.
How long do I have to file a Medicare chiropractic claim?
For services on or after January 1, 2010, a Medicare claim must be filed no later than the end of the period ending one calendar year after the date of service, under 42 CFR 424.44. Limited extensions exist, such as for contractor error, but plan to file well before the deadline.
Can a chiropractor opt out of Medicare?
No. The Medicare Benefit Policy Manual says chiropractors are not included in the opt-out definition of a physician or practitioner. They cannot opt out and bill Medicare patients under a private contract. Services are billed within Medicare’s rules.
When should a chiropractic practice outsource Medicare billing?
Consider it when billing is a side duty for front-desk staff, denials go unworked, or no one has time to follow Medicare and MAC updates. Ask any billing partner who handles each step, how you will see claim status, and how they apply Medicare’s chiropractic rules.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Medicare Benefit Policy Manual, Chapter 15: Covered Medical and Other Health Services — CMS (current)
- Medicare Claims Processing Manual, Chapter 12: Physicians/Nonphysician Practitioners — CMS (current)
- 42 CFR 424.44: Time limits for filing claims — eCFR / Cornell LII (current)
Disclaimer: This page is general educational information for practice owners and managers. It is not legal, coding, billing-compliance or medical advice. Medicare rules, local coverage policies and payer requirements change; confirm current requirements with CMS, your Medicare Administrative Contractor and a qualified advisor before acting.
