
Burnout in healthcare is a work-related syndrome of exhaustion, cynicism and reduced effectiveness, driven mainly by workload, administrative burden and too little control over the day. Practices cannot fix it alone, but they can remove avoidable paperwork, billing rework and phone tasks.
The word is used loosely, so we start with the World Health Organization definition and then look at current numbers. After that we focus on the part a practice manager can change: how much clerical, billing and front-desk work lands on clinicians and staff. This is an operations view. It is not clinical or mental health advice, and it does not replace support for anyone who is struggling.
Key takeaways
- The WHO defines burn-out as an occupational phenomenon tied to chronic workplace stress that has not been successfully managed. It is not a personal failing.
- AMA data put physician burnout at 53% in 2022, 48.2% in 2023 and 43.2% in 2024. It is improving, but it is still high.
- A 2016 time-and-motion study found physicians spent about twice as much time on EHR and desk work as on direct face time with patients.
- Practices can reduce avoidable admin load with task delegation, cleaner claims, and a clear owner for every recurring task.
- Staffing and workflow changes help, but they sit beside, not in place of, support for the people who are already exhausted.
What burnout in healthcare actually means
Burnout is defined by the WHO as a syndrome resulting from chronic workplace stress that has not been successfully managed. In ICD-11 it is listed as an occupational phenomenon, and the WHO states it is not classified as a medical condition. It applies to the work context, not to other areas of life (World Health Organization, 2019).
The WHO describes three dimensions. They are useful because they translate directly into things a manager can notice on a normal week.
| WHO dimension | What it can look like at work | What a manager might notice |
|---|---|---|
| Energy depletion or exhaustion | Dreading the start of a clinic day; finishing charts late at night | More sick days, late notes, a growing backlog of unfinished tasks |
| Mental distance, negativism or cynicism toward the job | Short answers, withdrawal from the team, less patience with routine tasks | Fewer ideas offered in huddles; friction between front desk, billing and clinical staff |
| Reduced professional efficacy | Feeling that the work no longer makes a difference | More careless errors, rework and missed follow-up |
Source: World Health Organization, ICD-11 burn-out statement (2019). The third column is our operations interpretation, not WHO text.
A note on the old five-stage model
You may see burnout described as five stages, from a honeymoon phase to habitual burnout. That model is popular, but it is not part of the WHO definition and we have not found a primary source that establishes it, so we do not use it here.
How common is burnout among physicians right now?
In the AMA’s national comparison, 43.2% of physicians reported burnout in 2024, down from 48.2% in 2023 and 53% in 2022. The AMA drew on nearly 18,000 physician responses from 43 states, collected through more than 100 health systems and organizations (AMA, July 2025).
That is real progress, and it is still more than four in ten physicians. The same report shows the rate is not even across a career.
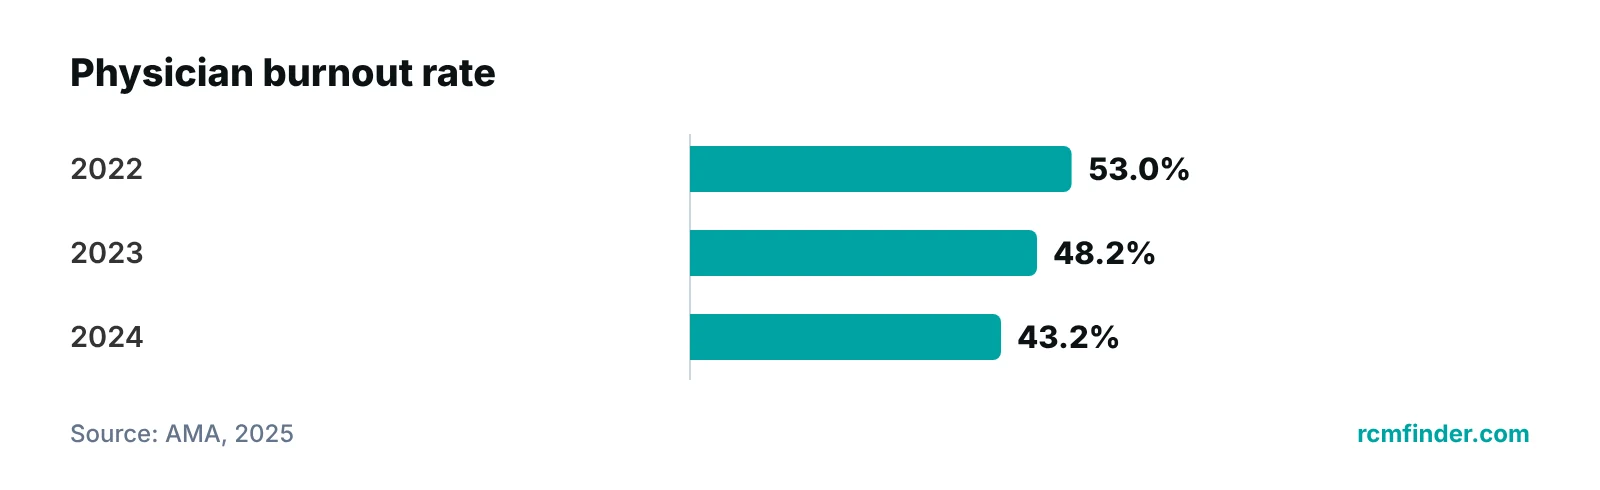
| Career stage | 2024 burnout rate | 2023 burnout rate |
|---|---|---|
| 1 to 5 years | 39.3% | 46.7% |
| 6 to 10 years | 48.4% | 55.1% |
| 11 to 15 years | 49.4% | 55.3% |
| 16 to 20 years | 46.5% | 50.8% |
| 20+ years | 38.3% | 41.3% |
Source: AMA, Organizational Biopsy findings reported July 2025.
Two cautions. These are physician figures; we did not find an equally current primary source for medical assistants, billers or front-desk staff, so we do not quote one. And the AMA article does not attribute the decline to any single cause, so it would be wrong to say that admin changes alone explain it.
What causes burnout in healthcare?
The U.S. Surgeon General’s 2022 advisory describes burnout as the result of an imbalance between work demands and the time and people available to meet them. It points to burdensome administrative tasks, a rapidly changing environment and a fragmented system as contributing causes (HHS, 2022).
Administrative and documentation load
This is the cause a practice can influence most. In the 2016 Annals of Internal Medicine time-and-motion study, 57 physicians in four specialties (family medicine, internal medicine, cardiology and orthopedics) were observed for 430 hours. Across the office day they spent 27.0% of their time on direct clinical face time and 49.2% on EHR and desk work. The researchers also noted one to two hours of after-hours work most nights, mostly EHR tasks. The HHS advisory cites the same pattern: about 2 hours of EHR and other administrative work for every hour of direct patient care, and nurses spending up to 41% of their time on the EHR and documentation.
The study is from 2016, so treat it as a benchmark for the pattern, not a measure of your clinic today.
Prior authorization and insurer requirements
The HHS advisory notes that administrative requirements such as prior authorizations can delay patient care. Inside a practice, that work is usually split between a clinician who has to justify the order and a staff member who chases the payer. Our prior authorization guide explains the workflow.
Inefficient workflows and low autonomy
The advisory also links inefficient work processes, burdensome documentation and limited autonomy to worse outcomes. In practice, that is the clinic where nobody is sure who owns a rejected claim, so it ends up on the physician’s desk.
What we have left out
The earlier version of this post listed policy change, technology frustration, patient expectations and reimbursement cuts as causes, each with a statistic. We could not trace those figures to a primary source, so we removed them. These pressures are real and widely reported, but we will not attach a number we cannot verify.
Why burnout is a business problem, not only a wellbeing problem
Burnout shows up in the numbers a practice manager already tracks: turnover, errors, rework and schedule gaps. We are describing mechanisms here, not quoting a statistic, because the older figures on medical errors, nurse turnover and depression rates in the previous version of this post could not be verified.
- Turnover. When someone leaves, the remaining team absorbs their tasks. That raises the strain on the people who stay.
- Errors and rework. A rushed registration, a missed modifier or an incomplete note becomes a rejected claim weeks later. See our guide to medical billing denial management.
- Late documentation. Notes finished at night are harder to code accurately. We cover this in why timely documentation matters.
- Patient experience. Longer phone waits and slower callbacks usually trace back to an overloaded front desk.
None of this means every billing problem is a burnout problem. But if the same few people are carrying the clerical load every week, it is worth asking whether the workload is part of the picture.
What a practice can change about the administrative load
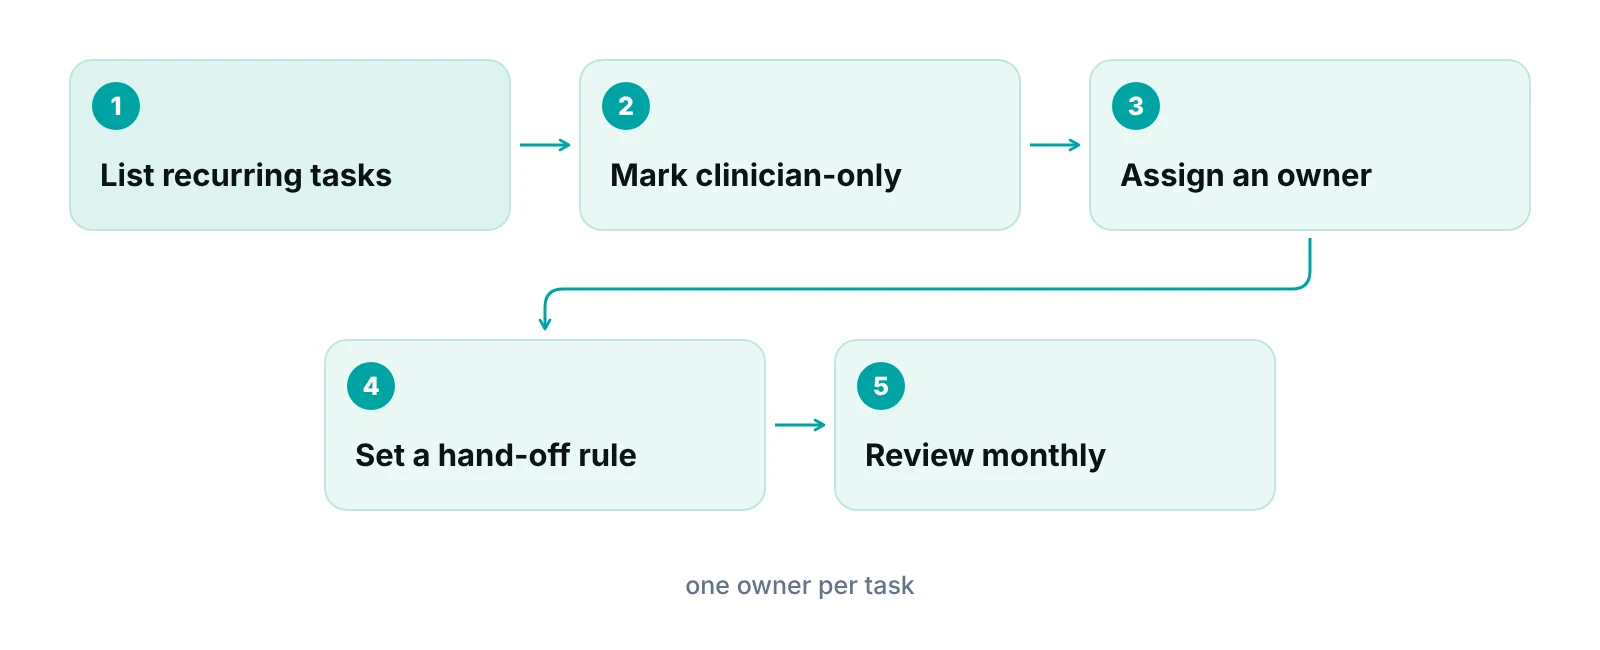
Practices cannot remove payer rules, but they can decide who does each task and how many times it gets touched. Start by listing the recurring non-clinical tasks that reach physicians and clinical staff, then sort them by whether they truly need a clinician.
| Task | Needs a clinician? | Usually better owned by |
|---|---|---|
| Appointment reminders, scheduling, intake forms | No | Front desk or a virtual assistant |
| Insurance eligibility checks before the visit | No | Front desk or a virtual assistant |
| Prior authorization submission and follow-up | Only to supply clinical rationale | Authorization coordinator, with a clinician sign-off |
| Charge entry, claim submission, payment posting | No | Billing team, in-house or outsourced |
| Denial follow-up and appeals | Sometimes, for a clinical letter | Billing team, with a clinician on request |
| Clinical documentation and sign-off | Yes | Clinician (with support from templates and scribes) |
Our operational view; payer and state rules vary. Not legal or compliance advice.
A virtual medical assistant for medical practices can take scheduling, eligibility checks and intake calls off a stretched front desk. Our team works with the EHR you already use, in your practice’s time zone. On the billing side, medical billing services can take claims, follow-up and denials off the clinic floor, and a practice management system that tracks claims by stage gives each open claim a stage and an owner, so work is not passed around by memory or sticky notes.
Hand-off needs rules, not just headcount
Moving work to a vendor or a new hire without a clear hand-off rule can create a second inbox. Decide what the outside team can resolve alone, what comes back to you, and how fast. Any vendor who touches patient data should put a Business Associate Agreement in place first.
Different specialties carry different admin burdens, from prior authorization-heavy ones to high-volume ones. See our billing and operations by specialty for how that plays out.
What staffing and billing changes will not fix
Operations changes reduce avoidable load. They do not treat burnout, and they do not replace support for the person who is exhausted. The HHS advisory also recommends giving health workers more schedule flexibility and autonomy and building in paid leave, which are management decisions rather than billing ones.
- Use regular one-to-one check-ins and ask what task takes the most time without adding value.
- Make time off easy to take, with coverage plans in place before it is needed.
- Make sure staff know how to reach your employee assistance or mental health resources. If anyone is in crisis, direct them to a licensed professional or local emergency services.
- Keep the conversation about workload and systems, not individual resilience.
“If the same two people clear every rejected claim, the problem is the process, not their stamina. Fix the hand-off first.”
How to start in the next 30 days
Start with a task inventory, because you cannot redistribute work you have not measured. Ask each team member to log recurring tasks for two weeks, noting who did them and how long they took.
- List every recurring non-clinical task that reaches a physician or nurse.
- Mark the ones that truly require a licensed clinician.
- Assign one named owner for each remaining task.
- Pick two or three KPIs to watch, such as denial rate and days in A/R, using our revenue cycle KPIs guide.
- Review the list monthly and adjust.
Not sure where your admin time is going?
Our free practice audit looks at your billing, claims follow-up and front-desk workflow and shows where avoidable work is landing on clinicians. Pricing for any service is quoted after the audit.
Our recommendations
- Measure before you delegate. We ask practices to log recurring tasks for two weeks first. Most managers are surprised by which tasks are reaching clinicians.
- Keep clinicians for clinical work. If a task does not need a license, we would assign it to someone else with a named owner.
- Give every open claim an owner. An unowned rejected claim travels to whoever notices it. That is usually the busiest person.
- Fix the front end of the claim. Complete registration and eligibility data prevents rework later, which means fewer interruptions for the team.
- Write the hand-off rule down. Whether the helper is a new hire or an outside team, record what they can resolve alone and what comes back.
- Treat wellbeing as separate work. Workflow changes are not a substitute for flexibility, time off and access to professional support.
Give every open claim a stage and a named owner.
Our practice management portal tracks claims by stage with an owner, so rejected claims are not left on a clinician's desk by default. Role-based permissions and an audit log show who handled what.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Burnout in healthcare has many causes, and administrative load is one a practice can actually move. Start by finding the tasks that should not be reaching clinicians, then give each one an owner. If billing and front-desk work are the main sources of rework, our medical billing services and virtual medical assistants are built for that hand-off. You can also estimate the revenue at stake with our revenue calculator, or read about how front-desk staff affect the revenue cycle and strategies for physician burnout.
Frequently asked questions
What is burnout in healthcare?
The WHO describes burn-out as a syndrome resulting from chronic workplace stress that has not been successfully managed. It has three dimensions: exhaustion, mental distance or cynicism toward the job, and reduced professional efficacy. The WHO treats it as an occupational phenomenon and not a medical condition.
What percentage of physicians experience burnout?
The AMA reported that 43.2% of physicians experienced burnout in 2024, down from 48.2% in 2023 and 53% in 2022. The data came from nearly 18,000 physician responses across 43 states. Rates differ by career stage, with mid-career physicians reporting the highest levels in 2024.
How does administrative work contribute to burnout?
A 2016 time-and-motion study of 57 physicians found they spent 49.2% of their office day on EHR and desk work versus 27.0% on direct face time with patients. The HHS advisory also cites about 2 hours of administrative work per hour of patient care. These are older figures, so measure your own clinic.
Can outsourcing billing reduce burnout?
It can reduce one source of strain by moving claims, follow-up and denial work away from clinicians and front-desk staff. It is not a cure for burnout, and results depend on clear hand-off rules and good communication. We do not promise any specific outcome.
What are early signs of burnout in a medical practice?
Look for more sick days, late documentation, rising rework, short tempers between teams, and people who stop suggesting improvements. These map to the WHO’s three dimensions but are not a diagnosis. If someone is struggling, encourage them to speak with a qualified professional.
Where should a small practice start?
Start with a two-week log of recurring non-clinical tasks, noting who does them and how long they take. Then assign a single owner to each task and review monthly. If billing or front-desk tasks dominate, a free practice audit can show where avoidable work sits.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Burn-out an 'occupational phenomenon': International Classification of Diseases — World Health Organization (2019)
- Burnout eases for doctors at every career stage as support rises — American Medical Association (2025)
- Physicians spend two hours on EHRs and desk work for every hour of direct patient care (summary of Annals of Internal Medicine study) — PNHP (2016)
- Addressing Health Worker Burnout: The U.S. Surgeon General's Advisory — U.S. Department of Health and Human Services (2022)
Disclaimer: This article is educational and is not medical, mental health, legal, coding or compliance advice. Payer rules and state requirements vary. If you or a colleague is in distress, contact a licensed professional or local emergency services.
