
The biggest radiology billing challenges are splitting one study into its technical and professional parts correctly, clearing prior authorization before the scan, keeping up with yearly Medicare payment and MIPS changes, and fixing the root cause of denials instead of reworking each one.
This update replaces older statistics with sourced Medicare and AMA information, and adds a decision guide for in-house, outsourced and hybrid billing. It is written for practice owners and billing managers. It is educational, not coding or legal advice.
Key takeaways
- Most imaging codes split into a technical (TC) and professional (26) component, and the owner of the equipment and the reader decide who bills what.
- Medicare has modifier-linked reductions for film X-rays (FX), computed radiography (FY) and some CT equipment (CT).
- For 2026, CMS states a negative 2.5% efficiency adjustment on non-time-based services and a 75-point MIPS threshold.
- Authorization problems begin before the scan, so check approvals against the code, date and site.
- Work denials by reason and fix the upstream rule.
Why is radiology billing harder than most specialties?
Radiology is hard to bill because one study often involves two different parties and two different payment components: the equipment, staff and facility on one side, and the radiologist’s interpretation on the other. Who owns each part decides who bills, with which modifier, and where the payment comes from.
That split sits on top of the usual pressures: orders from outside referrers, payer authorization rules, medical necessity edits and yearly rate changes. A radiology group can code every study correctly and still lose money if the order, the authorization or the modifier is wrong. The sections below take each pressure point in the order a claim meets it.
This guide covers the operations side. For the codes themselves, use our radiology CPT codes guide and our radiology CPT code reference rather than repeating them here. For the specialty overview, see our radiology billing and RCM page.
How do the technical and professional components work?
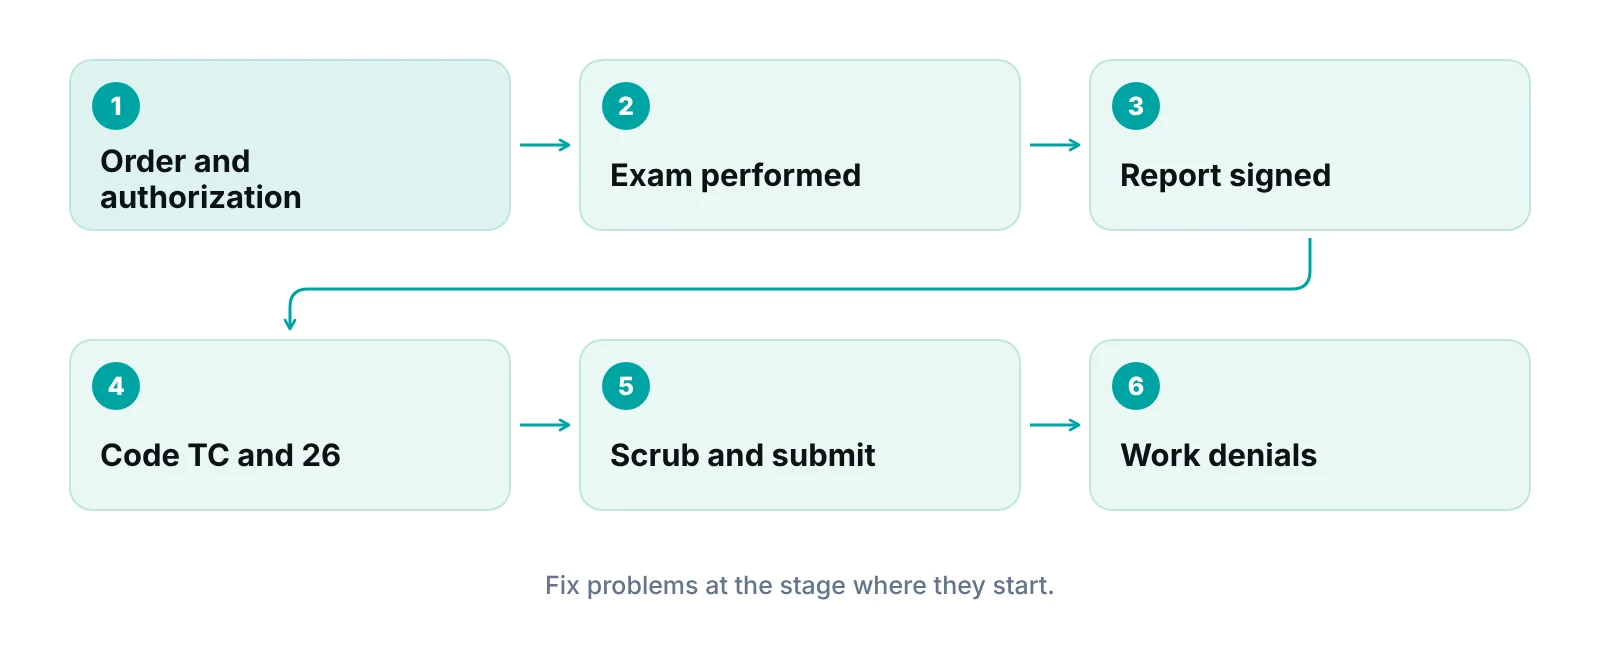
Most imaging codes can be billed three ways: global (both parts), professional component only (modifier 26) or technical component only (modifier TC). Which one applies depends on who owns the equipment and who reads the study. Getting this wrong is a leading source of rejected and underpaid radiology claims.
In Medicare’s fee schedule, diagnostic tests and radiology codes are flagged as usually having both parts. For those codes, the Medicare payment policy indicator guidance published by a Medicare contractor (2024) explains that the 26 version carries the work, practice expense and malpractice values, the TC version carries only practice expense and malpractice values, and the unmodified code is the sum of the two. Other codes are standalone professional-only or technical-only codes where neither modifier is allowed.
| Billing option | Modifier | What it covers | Typical billing party |
|---|---|---|---|
| Global | None | Technical and professional parts together | One party that owns the equipment and employs or contracts the reader, billing both parts |
| Professional component only | 26 | The radiologist’s interpretation and written report | The reading radiologist or group, when someone else bills the technical part |
| Technical component only | TC | Equipment, supplies and technologist staff | The owner of the equipment, such as a freestanding imaging center |
| Hospital patient | Varies | Hospital inpatient technical component is not paid to suppliers under Part B | Hospital for the facility part; radiologist bills the professional part |
Source: Novitas/First Coast Medicare PFS payment policy indicators page (2024); CMS Medicare Claims Processing Manual, Chapter 13, sections 20.1 and 20.2. Payer rules vary; confirm each contract.
The CMS Medicare Claims Processing Manual, Chapter 13 says Part B pays the professional component of radiology services furnished by a physician in all settings, and that the interpretation includes a written report. Outside hospitals, such as a physician office or freestanding imaging center, the technical component is paid under the fee schedule. For hospital inpatients, the manual says the technical component may not be paid to suppliers. The same chapter says a physician or supplier may bill for a component it contracts another party to perform, and that anti-markup rules apply when the performer does not share a practice with the biller.
Where this goes wrong in daily billing
- A group reads studies done at an outside site, but the claim goes out global instead of with modifier 26.
- Both the imaging center and the reading group bill the technical part, producing a duplicate denial.
- The place of service on the claim does not match where the exam was performed.
- A contract or lease changes who owns the equipment, but the billing setup still reflects the old arrangement.
None of these is a coding problem. They are setup problems, which is why they repeat on every claim until someone fixes the rule. Fixing them once, in the billing setup for each site, prevents the same denial from repeating.
Which Medicare payment reductions affect imaging claims?
Medicare applies several imaging-specific payment reductions that depend on modifiers the claim must carry. If the modifier is missing, the payer may pay the full rate and recoup it later, or the claim may be flagged. The manual lists three that radiology billing teams should know.
| Modifier | Applies to | Reduction stated in the manual |
|---|---|---|
| FX | X-ray taken using film | 20% reduction |
| FY | X-ray taken using computed radiography | 10% for calendar year 2023 and later (7% for 2018 through 2022) |
| CT | CT services on equipment that does not meet the NEMA XR-29-2013 standard | 15% reduction from 2017 onward (5% in 2016) |
Source: CMS Medicare Claims Processing Manual, Chapter 13, sections 20.2.4 to 20.2.6. Confirm the current manual version before relying on these rates.
The manual also tells contractors to apply the multiple procedure reduction to certain diagnostic nuclear medicine codes. For CT, it says not to reduce or deny payment for medically necessary multiple CT scans of different body areas on the same day. Commercial payers set their own multiple-imaging rules, so check each contract rather than assuming Medicare’s rules carry over.
Why do prior authorization and denials hit radiology so hard?
Advanced imaging is a common target for payer authorization requirements, and a missing or mismatched approval is a straightforward denial reason. The authorization is usually obtained before the patient arrives, often by the referring office, so the radiology group depends on a step it does not control.
The American Medical Association’s 2024 prior authorization physician survey (all specialties, not radiology only) found 94% of physicians reported that prior authorization delays access to necessary care, and nearly one in four (24%) reported it led to a serious adverse event for a patient. Physicians reported completing an average of 43 authorizations per week, equal to about 12 hours of physician and staff time, and 35% said they employ staff who work only on prior authorization. Those figures describe the administrative load around imaging orders, not radiology denial rates, which are not reported here.
“A denial is information about a process. The goal is to remove the cause, not just to resubmit the claim.”
A practical denial checklist for radiology
- Authorization match: the approved code, date range and rendering site match what was performed and billed.
- Order match: the exam billed is the exam ordered, with a documented reason that supports medical necessity.
- Component match: global, 26 or TC matches who owns the equipment and who read the study.
- Laterality, contrast and add-on codes: the report supports what the charge says.
- Patient and payer data: member ID, payer and referring provider are complete before the claim leaves.
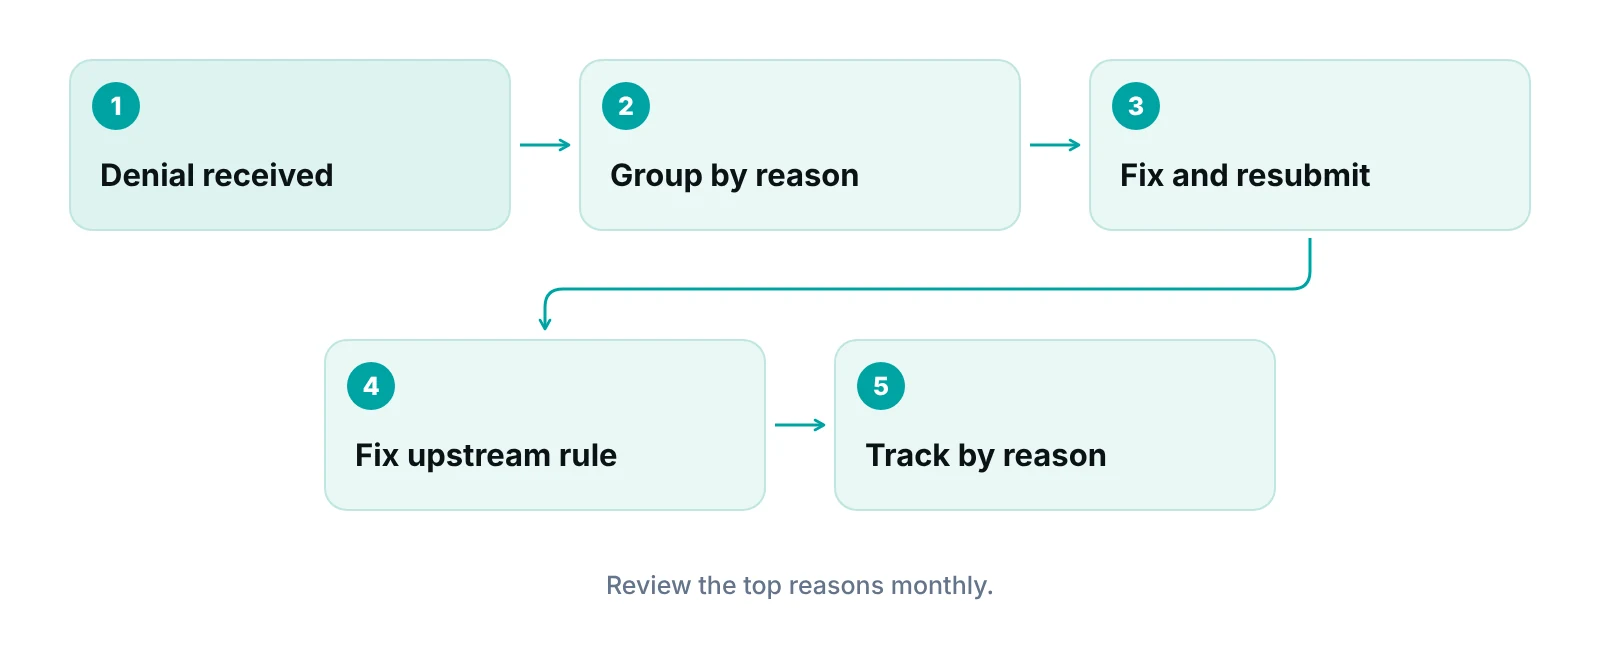
Work denials by reason, not claim by claim. If the same reason appears repeatedly, change the upstream rule. Our guides to prior authorization and denial management go deeper on each step, and our prior authorization services page shows how outside support can sit in front of the scan.
What payment and MIPS changes matter in 2026?
Two federal changes shape 2026 planning: the Medicare physician fee schedule final rule and the MIPS performance threshold. Neither source we reviewed gives a radiology-specific revenue figure, so each group should model its own code mix before drawing conclusions.
| Item | What the source states | What to check in your practice |
|---|---|---|
| Conversion factor | $33.40 for non-qualifying APM participants (up 3.26%) and $33.57 for qualifying APM participants, from $32.35 | Compare 2026 rates for your top ten codes against 2025, by component |
| Efficiency adjustment | Negative 2.5% for 2026, applied to non-time-based services; time-based codes such as E/M are exempt | Whether your highest-volume codes are in the affected group |
| Facility and office indirect costs | CMS finalized recognizing greater indirect costs for office-based than facility-based practitioners | Your mix of facility-based and office-based billing |
| MIPS threshold | 75 points for the 2026 performance period (2028 payment year); maximum negative adjustment 9% | Whether you are reporting, as a group or individually, and which measures apply |
Source: CMS CY 2026 Physician Fee Schedule final rule fact sheet (October 2025); CMS 2026 Quality Payment Program final rule fact sheet (reposted copy). Confirm against qpp.cms.gov.
The CMS CY 2026 fee schedule fact sheet also says CMS used hospital outpatient data for some technical services such as radiation treatment, instead of the AMA survey data. It does not give a radiology-wide impact, so look at code-level files for imaging codes you bill.
For MIPS, the CMS 2026 Quality Payment Program fact sheet states a 75-point threshold and a maximum 9% negative adjustment for the 2026 performance period, which feeds the 2028 payment year. For category scoring, see our MIPS categories and scoring guide, and confirm the current-year details before planning.
Should a radiology practice keep billing in-house or outsource?
The right answer depends on volume, systems and who can own the work. Compare three models against the radiology problems above rather than choosing on price alone.
In-house billing
Works when the team has radiology experience, a written rule for each reading site and contract, and someone who owns denial trends. Risk: one departure can leave modifier rules and payer knowledge undocumented.
Full outsourcing
Works when the group lacks capacity for charge entry, follow-up and appeals. Ask how component splits are set up per site, who works denials, what reporting you get, and whether the vendor signs a Business Associate Agreement before seeing patient data. Our medical billing services page lists what end-to-end support can include.
Hybrid
Keep charge capture and clinical questions in-house, and send follow-up, denials or accounts receivable to a partner. A denial management service is a common starting point.
Whatever the model, a claim-centred system helps. For example, a practice management system that tracks claims by stage can show who owns each claim, check data completeness before submission, apply specialty-aware billing logic and flag underpayments against expected amounts. It works with the EHR you already use and is not an EHR.
See where your radiology claims stall
Our free practice audit reviews a sample of your claims and denials, then shows which step costs you the most.
If you want to see what denied or delayed claims may cost your group, try the revenue calculator.
Our recommendations
- Write down the component rule for every reading site. For each site and contract, record who owns the equipment, who reads, and which of global, 26 or TC is billed. Review it whenever a lease or contract changes.
- Check authorization before the exam, not after the denial. Confirm the approval matches the code, date and site. Build a hold for scans that need approval and have none.
- Group denials by reason every month. Rank the top five reasons and assign each an owner and an upstream fix.
- Add imaging modifier checks to claim review. Make FX, FY and CT a standing item for the equipment you use, and confirm current rules in the Medicare manual.
- Model 2026 rates with your own code mix. Pull your top codes by volume, compare rates by component, and plan around the results rather than headlines.
- Decide your reporting path for MIPS early. Confirm whether you report as a group or individually, and which measures apply to your work.
- Run a trial before choosing a vendor. Ask any billing partner to show how it handles a split-component study from order to payment, and sign a BAA before it sees patient data.
Track each radiology claim by stage, with an owner, from charge to payment.
Our portal tracks claims by stage with an assigned owner, runs data-completeness checks before submission, applies specialty-aware billing logic and flags underpayments against expected amounts. It works alongside the EHR you already use and is not an EHR.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Radiology billing challenges come from splitting components correctly, controlling authorization, working denials at the source and tracking yearly rule changes. A group that fixes those four things usually spends less time on rework. If you want a second pair of eyes, start with a free audit, see our radiology specialty page, or explore denial management services.
Frequently asked questions
What is the difference between modifier 26 and modifier TC in radiology?
Modifier 26 marks the professional component, the radiologist’s interpretation and report. Modifier TC marks the technical component, covering equipment, supplies and technologist staff. A global claim, with neither modifier, covers both. Which one you use depends on who owns the equipment and who reads the study. Confirm payer-specific rules before billing.
Why are radiology claims denied for prior authorization?
The most common causes are no approval on file, an approval that does not match the code, date or site billed, or an approval obtained under the wrong payer. Because referring offices often request the approval, check it before the exam, not after the claim is denied.
Does Medicare reduce payment for some imaging claims?
Yes. The Medicare claims manual describes reductions tied to modifiers: FX for film X-rays (20%), FY for computed radiography (10% for 2023 and later) and CT for CT services on equipment that does not meet the NEMA XR-29-2013 standard (15% from 2017). Verify the current manual before relying on these figures.
How do MIPS penalties apply to radiologists?
For the 2026 performance period, CMS states a 75-point threshold and a maximum negative adjustment of 9%, applied in the 2028 payment year. Your reporting path and measures depend on whether you report individually or as a group, so confirm with the Quality Payment Program resources.
Should a small radiology group outsource billing?
It can help when the group lacks capacity for follow-up and denials, or lacks radiology-specific knowledge. Compare in-house, full outsourcing and hybrid models, ask how component splits are handled, and require a Business Associate Agreement before any vendor accesses patient data.
How can a radiology practice reduce billing rework?
Fix upstream causes. Document component rules for each site, check authorization before the exam, review claims for modifier and data completeness before submission, and group denials by reason each month so the same error does not repeat.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- CY 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F) fact sheet — CMS (2025)
- Medicare Claims Processing Manual, Chapter 13 – Radiology Services — CMS (current manual)
- Medicare Physician Fee Schedule payment policy indicators — First Coast Service Options (Medicare contractor) (2024)
- AMA survey indicates prior authorization wreaks havoc on patient care — American Medical Association (2024)
- 2026 Quality Payment Program Final Rule Fact Sheet and Policy Comparison Table — CMS (reposted by AAHD) (2025)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. Payer rules, Medicare rates and quality program requirements change; verify current rules with your payers, MAC and official CMS sources before acting.
