
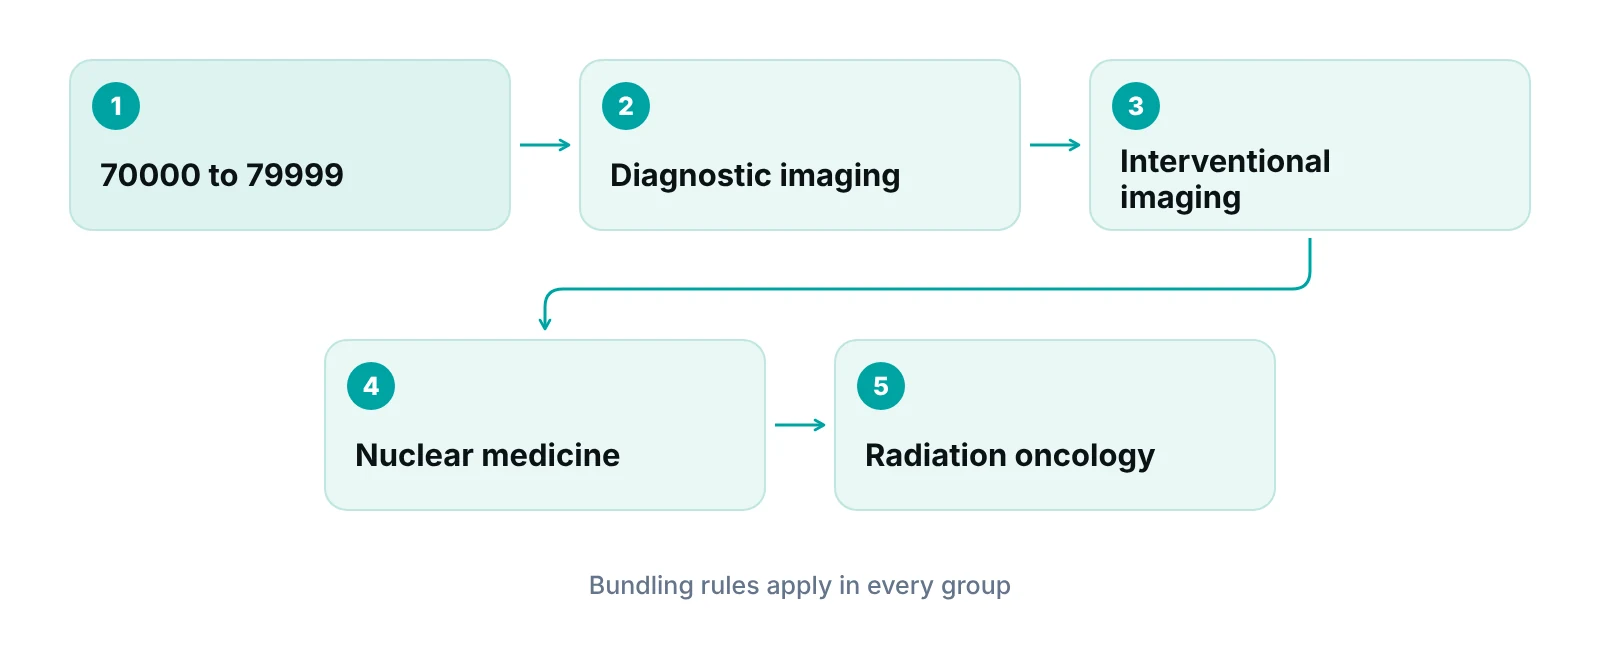
Radiology CPT codes are the 70000-series procedure codes, 70000 to 79999, that report imaging and radiation oncology services. Medicare's coding policy groups them into diagnostic imaging, interventional imaging, nuclear medicine and radiation oncology. Many split into a professional (26) and a technical (TC) component, and several services are bundled and cannot be billed separately.
This guide replaces the old range-by-range list with something more useful: how the series is organized, who bills which part of an imaging service, and which bundling rules produce denials. The rules come from the NCCI Policy Manual, Chapter 9 (revised 1/1/2026) and the Medicare Claims Processing Manual, Chapter 13. For a code-by-code lookup, see our separate radiology CPT code lookup guide.
Key takeaways
- Radiology CPT codes run from 70000 to 79999 and sit in four working groups for Medicare edit purposes: non-interventional imaging, interventional imaging, nuclear medicine and radiation oncology.
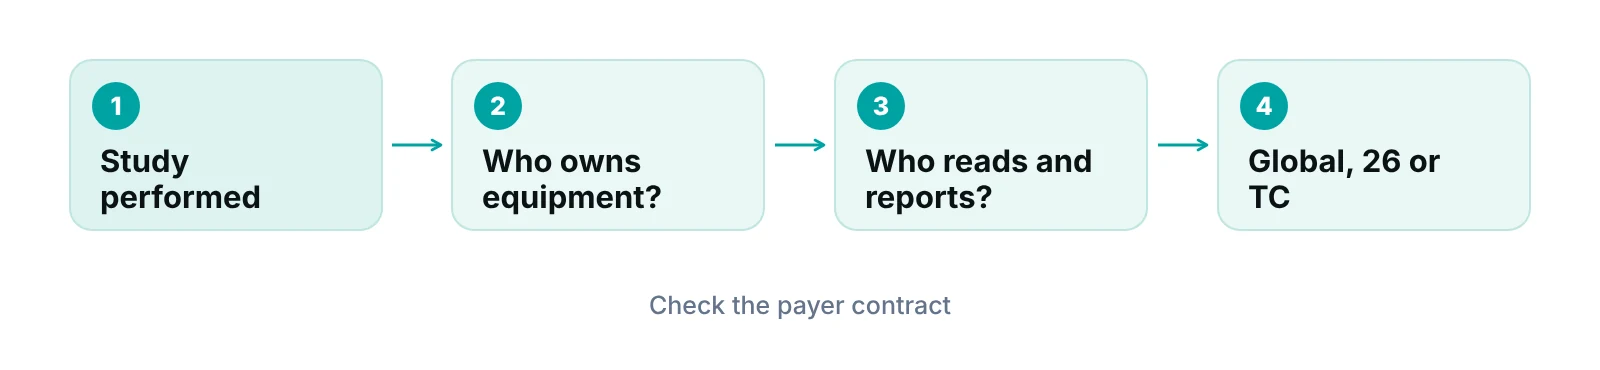
- Most imaging codes can be billed global, or split with modifier 26 (professional) and TC (technical). Which one you use depends on who owns the equipment and who reads the study.
- Contrast, fluoroscopy needed to finish a study, and many guidance services are bundled. Billing them separately is the most common unbundling error.
- Same-day screening and diagnostic mammography, and repeat films, have specific reporting rules in the NCCI manual.
- Check the current year’s code set and NCCI manual before building a charge master: both change, and this page does not replace them.
What radiology CPT codes are
Radiology CPT codes are five-digit procedure codes from the 70000 series that describe imaging and radiation oncology services. The NCCI Policy Manual, Chapter 9 covers the whole range, 70000 to 79999. CPT itself is maintained by the American Medical Association, which also owns the official code descriptors, so the descriptions on this page are our own short summaries.
A radiology code tells the payer what was done, not why. The reason comes from the diagnosis code, and the two must support each other. A CT head with a diagnosis that does not justify imaging is a medical necessity denial, not a coding error. If you are new to how the code sets fit together, our guide to how CPT codes work in medical billing and our explainer on HCPCS vs CPT cover the basics.
Two things make radiology different from office-visit coding. First, the same study is often performed by one party (a facility or imaging center with the scanner and technologists) and interpreted by another (a radiologist). Second, many services are packaged: the code descriptor already includes things like the radiographs needed to complete the study, so adding more codes is unbundling. The rest of this post covers those two ideas.
How the 70000 series is organized
Medicare’s radiology coding policy sorts the series into working groups. The 2026 NCCI Policy Manual chapter lists non-interventional diagnostic imaging, interventional or invasive diagnostic imaging, nuclear medicine and radiation oncology, with mammography and bone density handled as specific topics inside those groups. The table below uses those headings and shows example codes the manual itself uses, so you can see how a rule attaches to a code family.
| Working group | Examples named in the manual | What the manual says to watch |
|---|---|---|
| Non-interventional diagnostic imaging (X-ray, CT, MRI, ultrasound) | 73020 and 73030 (shoulder), 72081 to 72084 (spine views) | Report the one code that describes the full study. Three shoulder views are 73030 once, not 73020 plus 73030. |
| Interventional or invasive diagnostic imaging | 76942, 77002, 77003, 77012, 77021 (imaging guidance) | Contrast and vascular access for the procedure are integral. These guidance codes allow one unit per patient encounter. |
| Nuclear medicine | 78814 to 78816 (PET/CT) | The radiopharmaceutical injection is part of the procedure. CT done for attenuation correction and localization is included in PET/CT. |
| Radiation oncology | 77301 (IMRT planning), 77336 (per week of treatment), 77750 to 77790 (brachytherapy) | Several planning and management services are included in brachytherapy codes. 77336 is reported per week of therapy. |
| Mammography | 77063 (screening tomosynthesis), 77067 | 77063 is an add-on that may be reported with 77067 (since 2018). Same-day screening and diagnostic studies need modifiers. |
| Bone density | 77078, 77080, 77081 | One axial and one peripheral study per date. |
Source: CMS, Medicare NCCI Policy Manual, Chapter 9 (rev. 1/1/2026), sections C, D, E, F and H. Code descriptions are our own summaries.
The old versions of this page listed long code ranges with one-line descriptions. We removed them because several ranges overlapped and could not be checked against the current code set. Use the AMA’s CPT book or your coding software for the full list and exact descriptors, and use the table above to see which rules apply to each family.
Global, professional (26) and technical (TC) billing
Most diagnostic radiology codes can be billed three ways: global, professional component only (modifier 26), or technical component only (modifier TC). The Medicare fee schedule flags this with a PC/TC indicator. According to First Coast Service Options, a Medicare Administrative Contractor, indicator 1 covers diagnostic tests and radiology services that usually have both components and allow modifiers 26 and TC.
| How it is billed | Modifier | What it covers | Typical situation |
|---|---|---|---|
| Global | None | Both the equipment and staff (technical) and the physician interpretation (professional) | One practice owns the scanner and its radiologist interprets the study |
| Professional component | 26 | The physician’s interpretation and written report | A radiologist reads a study done at a facility or imaging center they do not own |
| Technical component | TC | Equipment, supplies and technologist staff | An imaging center performs the study while an outside radiologist reads it |
| No split allowed | Do not use 26 or TC | The code is already professional-only, technical-only or global-only | Codes with PC/TC indicators 2, 3 or 4 on the fee schedule |
Source: First Coast Service Options, Medicare Physician Fee Schedule payment policy indicators (page dated Sept. 11, 2024); CMS, Medicare Claims Processing Manual, Chapter 13.
The professional component includes a written report. Section 20.1 of the Medicare Claims Processing Manual, Chapter 13 states that the interpretation of a diagnostic procedure includes a written report. A study that is only viewed, with no report, is not a billable professional service. For the technical side, section 20.2.2 of the same chapter directs MACs to pay the technical component under the fee schedule for services furnished to non-hospital patients in settings such as a freestanding imaging center.
“Before you bill a split, decide who owns the scanner and who wrote the report. Those two facts usually settle global, 26 or TC.”
Two cautions. First, some payers have their own rules on global versus split billing, so check each contract. Second, the indicator is code-specific: a code that allows 26 and TC one year may be assigned differently after a fee schedule update, so look it up in the current fee schedule file rather than relying on memory.
Bundling rules that cause radiology denials
The most common radiology denials come from billing something the code already includes. The NCCI Policy Manual, Chapter 9 sets out the Medicare position, and many commercial payers use similar edits. The main patterns are below.
| Situation | What the manual says | What to check before billing |
|---|---|---|
| Contrast | Oral or rectal contrast, parenteral vascular access and contrast administration are integral, and contrast used for localization or guidance is integral to the interventional procedure unless CPT directs otherwise (section D.1, D.3). | Remove separate injection or administration lines unless a CPT note allows them. |
| Fluoroscopy | Fluoroscopy needed to complete a procedure and produce the permanent record is included (section C.5). 76000 is integral to many spinal, endoscopic and injection procedures (D.8). | Do not add a fluoroscopy line to a procedure that includes it. |
| Imaging guidance | 76942, 77002, 77003, 77012 and 77021 allow one unit per patient encounter (G.3). | Check units on every guidance line. Two needle passes are still one encounter. |
| Multiple views | Report the most comprehensive code. Three shoulder views are 73030 once (C.2). | Match the number of views in the report to the code descriptor. |
| Repeat films | Repeats for poor quality or added views are one unit of the code describing the total service (C.1). | Do not bill a second unit for a retake. |
| Same-day screening and diagnostic mammography | Diagnostic code takes modifier GG; screening code takes 59 or XU (C.16). | Confirm both studies were done and documented on the same date. |
| Bone density | One axial and one peripheral study per date (H.15). | Check for a duplicate line before submission. |
Source: CMS, Medicare NCCI Policy Manual, Chapter 9 (rev. 1/1/2026). Paraphrased; section letters in brackets.
The manual also warns against working around edits: it states that services should not be moved to different dates to avoid MUE or NCCI procedure-to-procedure edits (H.1). Modifier 59 and the X modifiers are for distinct services, not for getting around an edit. Our modifier 59 guide explains when they are appropriate.
Medicare rules are the baseline, not the contract
Commercial payers can publish their own edits, their own global and split rules, and their own prior authorization requirements for advanced imaging. Treat the CMS manual as the starting point and the payer’s policy and contract as the final word.
Radiation oncology and nuclear medicine: where the rules differ
These two groups are the least like office coding, so they are worth a short note.
For radiation oncology, the NCCI manual says an evaluation and management service is separately reportable only at the initial visit where the decision to treat is made (section F.1), and that 77336 is reported per week of therapy, generally after every five treatments (F.2). Brachytherapy codes 77750 to 77790 include several other services, with limited exceptions (F.4).
For nuclear medicine, the radiopharmaceutical injection is part of the procedure (E.1), and a planar and a SPECT study of a limited area are not both reported unless a single combined code exists (E.2). For PET/CT codes 78814 to 78816, the CT used for attenuation correction and localization is included (E.14).
If you run a radiation oncology program, our general post on the challenges of radiology medical billing covers the operational side, such as authorization and charge capture.
A workflow that keeps radiology claims clean
A short pre-bill routine catches most unbundling and modifier errors before the payer does. The steps below are general practice, not a CMS requirement.
- Confirm who performed the study and who wrote the report, then choose global, 26 or TC.
- Match the code to the study actually performed and documented, including the number of views.
- Remove lines that the main code already includes: contrast, access, completion fluoroscopy, repeat films.
- Check units on guidance codes and any code with a per-encounter or per-date limit.
- Check that the diagnosis supports the study, and that any required authorization is on file.
- Run a scrubber or edit check before submission, then review rejections by reason.
A practice management system that tracks claims by stage can make this routine visible. The RCM Finder portal assigns an owner to each claim, runs data-completeness checks before submission and can flag a claim for review through workflow rules. The coding judgment itself stays with your coders and radiologists. Our clean claim checklist and claim scrubbing guide go deeper on the edit step.
Have a coder look at your imaging claims
A free practice audit reviews how your radiology claims are coded, split and bundled before submission, and where denials start.
Our recommendations
- Decide global, 26 or TC in writing. Document, for each location and payer, who owns the equipment and who reads. Make the choice a rule in your billing system rather than a case-by-case decision.
- Update the charge master every January. CPT and the NCCI manual change by year. Compare your imaging charge lines against the new code set and the new NCCI manual before the first claim of the year goes out.
- Build bundling checks into the scrubber. Add edits for contrast lines, completion fluoroscopy, guidance units and repeat films, based on the current NCCI chapter, so the errors are blocked before submission.
- Require a signed report for every professional claim. The professional component includes a written report. Hold professional claims until a report is final, and track studies that are read but not reported.
- Work denials by reason, not by claim. Group imaging denials by cause (bundling, medical necessity, authorization, component mismatch). Fix the cause upstream and the same denial stops recurring.
- Read the payer policy for advanced imaging. Many payers add rules for CT, MRI and PET. Keep a one-page reference per major payer, updated when the payer posts changes.
Catch imaging claim errors before submission.
Our portal tracks each claim by stage with an assigned owner, runs data-completeness checks before submission and can flag a claim for review through workflow rules. Coding decisions stay with your coders and radiologists.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Radiology CPT codes are easier to manage once you see two things: the series falls into four working groups, and each service is either global or split between a professional (26) and a technical (TC) component, with bundling rules that limit what can be billed beside it. If imaging denials are costing your radiology practice revenue, start with the component split and the bundling checks, then send the exceptions to a coder. Our denial management and medical billing and coding support teams can review both. Start with a free practice audit.
Frequently asked questions
What range do radiology CPT codes cover?
Radiology CPT codes are the 70000 series, 70000 to 79999, according to the CMS NCCI Policy Manual chapter on radiology services. They cover diagnostic imaging, interventional imaging, nuclear medicine and radiation oncology. The exact codes and descriptors in each group are in the AMA’s CPT book for the year, so check it before billing.
What is the difference between modifier 26 and modifier TC?
Modifier 26 marks the professional component, the physician’s interpretation and report. Modifier TC marks the technical component, the equipment, supplies and technologist staff. Billing both with no modifier is a global claim. Some codes already represent only one part, and for those the fee schedule does not allow 26 or TC.
Can I bill contrast separately from an imaging study?
Usually not under Medicare. The NCCI manual says oral or rectal contrast, vascular access and contrast administration are integral to the imaging procedure, and contrast used for guidance is integral to an interventional procedure unless CPT says otherwise. Check payer policy, which may differ, and look for a CPT note before adding a separate line.
How do I bill screening and diagnostic mammography on the same day?
The 2026 NCCI manual says to report the diagnostic mammography code with modifier GG and the screening code with modifier 59 or XU when both are done on the same date. Both studies must be documented. Check your payer’s rule too, because some do not follow Medicare’s approach.
How many units of ultrasound or imaging guidance can I bill?
For 76942, 77002, 77003, 77012 and 77021, the NCCI manual allows one unit per patient encounter. Two passes or multiple needles in one session are still one unit. Other guidance codes have their own limits, so check the code descriptor and the manual.
How often should we review our radiology coding?
At least once a year when the CPT code set and NCCI manual update, and any time a payer announces a policy change or you see a cluster of imaging denials. The NCCI radiology chapter cited here is dated 1/1/2026, so a new edition will replace it.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Medicare NCCI Policy Manual, Chapter IX: Radiology Services (CPT 70000-79999) — CMS (2026 (rev. 1/1/2026; accessed 2026-10-14))
- Medicare Claims Processing Manual, Chapter 13: Radiology Services and Other Diagnostic Procedures — CMS (accessed 2026-10-14)
- Medicare physician fee schedule payment policy indicators — First Coast Service Options (Medicare Administrative Contractor) (2024 (page dated 2024-09-11))
- NCCI Policy Manual, Chapter IX (Version 7.3, older edition) — CMS (2001 edition)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT is a trademark of the American Medical Association, and the code descriptions here are our own summaries. Payer rules and contracts vary, and CMS updates its manuals each year. Check the current CPT book, CMS and payer sources before you bill.
