
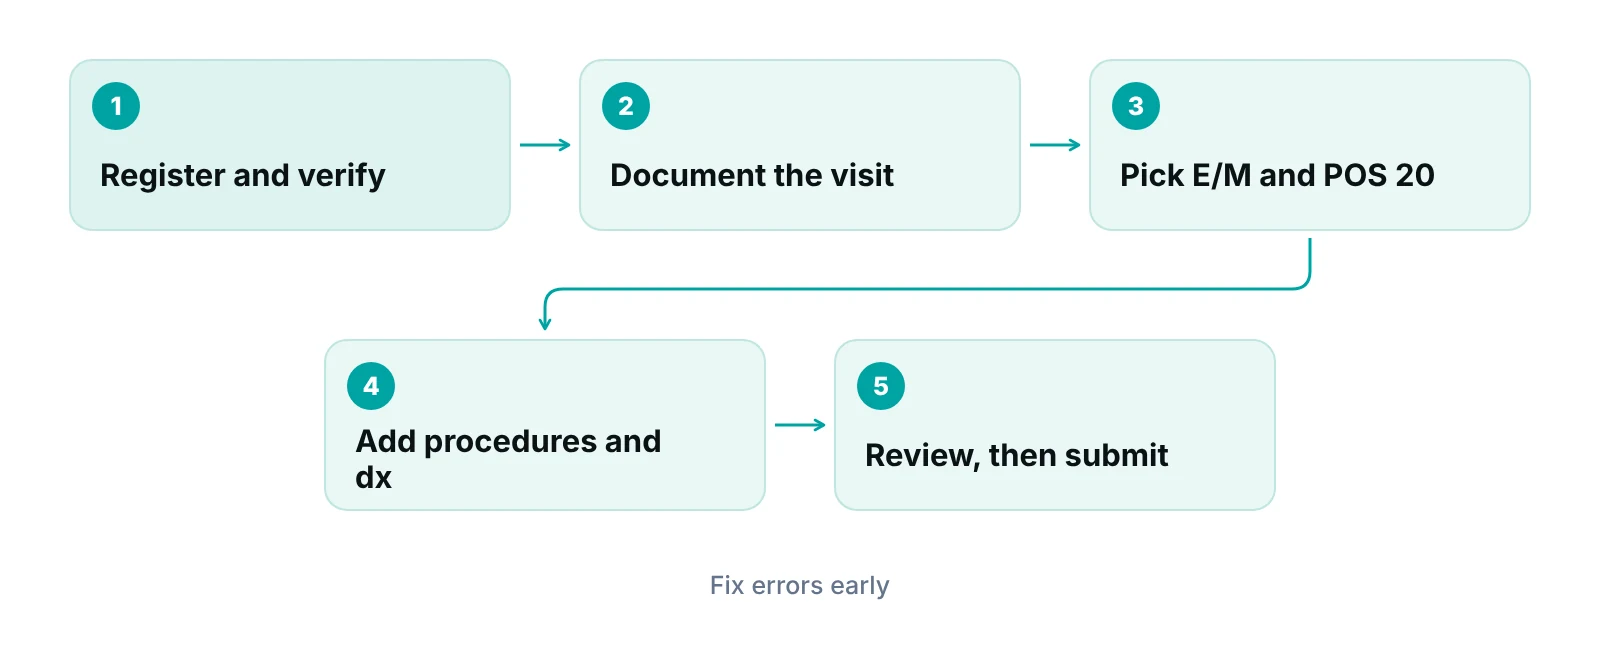
Urgent care billing and coding starts with POS 20 on the claim, an office E/M code (99202-99205 or 99211-99215) chosen by medical decision making or total time, and charges for any separately identifiable procedures. S9083 and S9088 are payer-specific codes, not Medicare codes. Your payer contract decides which of them you can bill.
Older guides on this topic mix long-standing rules with things that were never true. They call POS 20 a 2024 update, mislabel the E/M levels, describe S-codes as universal, and tell centers to get consent before billing. This guide fixes those four points using primary sources. We last checked them on October 14, 2026, and it is written for owners and managers of urgent care centers.
Key takeaways
- POS 20 has been the urgent care place of service since October 1, 2003. It is not a 2024 change.
- Since 2021, office E/M levels follow medical decision making or total time. 99202 is straightforward, 99203 low, 99204 moderate and 99205 high.
- S9083 and S9088 are payer-specific. S9083 is not payable by Medicare, and some plans treat both codes as informational.
- HIPAA does not require patient consent to send a claim for payment. Consent for treatment, payment and operations is optional.
- Your payer sheet and your documentation do more for clean claims than any single code.
What urgent care billing and coding covers
Urgent care billing and coding is the work of turning a walk-in visit into a claim a payer will pay. Most claims have four parts: the place of service, an evaluation and management (E/M) code for the visit, codes for any procedures, supplies or tests done that day, and diagnosis codes that support them. Each part has its own rules, and each can cause a denial on its own.
Urgent care adds two wrinkles that a standard office does not have. Some commercial payers use special urgent care codes and contract terms that Medicare never uses. This guide covers both, in the order a claim is built.
If you want the mistakes list rather than the building blocks, our urgent care billing mistakes guide covers that angle. For how this fits into the wider practice, see our page for urgent care centers.
Place of service 20: what it is and what it is not
Place of service (POS) 20 tells the payer the visit happened at an urgent care facility. The CMS memo that created it defines it as a location, distinct from a hospital emergency room, an office, or a clinic, that diagnoses and treats illness or injury for unscheduled, ambulatory patients seeking immediate medical attention. The code took effect on October 1, 2003.
That date matters. The old guide called POS 20 a 2024 change, and it was not. If a payer rejects an urgent care claim for POS, the cause is almost always a mismatch between the POS on the claim and how your location is enrolled, not a new code.
Some payers go further and require POS 20 together with office visit E/M codes. One example is a Blue Cross Blue Shield of North Dakota policy that applied to claims processed on or after June 1, 2022, which said urgent care services must be billed with POS 20 and the office visit E/M codes. That policy is now archived (December 1, 2024) and points to a newer E/M policy, so treat it as an example of how payers write these rules, not as a current rule for your plan.
Pending: a possible change to POS 20
The Journal of Urgent Care Medicine reported on November 13, 2025 that the 2026 Medicare Physician Fee Schedule did not change POS 20, and that CMS said comments asking for a separate code for enhanced urgent care would be considered for possible future rulemaking. Nothing has changed yet. Check CMS before you update any billing setup.
Choosing the E/M level for a walk-in visit
Urgent care visits are usually reported with the office or other outpatient E/M codes, 99202 to 99205 for new patients and 99211 to 99215 for established patients. Since January 1, 2021, providers may choose the level based on either medical decision making (MDM) or total time on the date of the encounter. CPT 99201 was deleted that year.
History and exam are still documented, but only as medically appropriate. They no longer decide the level. For visits on or after January 1, 2021, the 1995 and 1997 documentation guidelines no longer apply to these codes, according to the same Noridian Medicare page.
How MDM maps to the code
MDM has four levels: straightforward, low, moderate and high. The level is set by meeting two of three elements: the number and complexity of problems addressed, the amount and complexity of data reviewed, and the risk of management decisions. The table shows which code each level supports.
| MDM level | New patient | Established patient | Typical urgent care example (our illustration) |
|---|---|---|---|
| Straightforward | 99202 | 99212 | A minor, self-limited problem with little to review |
| Low | 99203 | 99213 | An uncomplicated injury or illness needing a simple test or treatment |
| Moderate | 99204 | 99214 | Several problems, or a problem with more risk and more data to review |
| High | 99205 | 99215 | A threat to life or bodily function that needs a high-risk decision |
Source: American Academy of Ophthalmology, E/M guideline changes (accessed 2026); Noridian Medicare E/M page (accessed 2026). The examples in the last column are our own illustrations, not CPT text. 99211 is also in the code set; the pages we read gave no MDM criteria for it.
Time works differently from MDM. Total time counts the provider’s own face-to-face and non-face-to-face work on that date, but time spent separately by clinical staff does not count. Minute ranges are set by the AMA in the CPT code book and have been revised, so use the current book rather than a chart copied from a blog. Our 99213 CPT code guide walks through one of the most common established-patient levels in detail.
What changed since 2024, and what did not
The real structural change in office E/M coding happened in 2021, not 2024: MDM or time now sets the level, and history and exam no longer do. POS 20 has been in place since 2003. Those are the stable parts of an urgent care claim.
What does change each year is the code book and the payer rules around it. CPT is updated by the AMA, ICD-10-CM diagnosis codes are updated each fiscal year, and payers publish their own policies. We do not list a year-specific change table here, because a table like that goes stale quickly and we could not source a single list from a primary body. Instead, build a calendar habit: each October, review the new ICD-10-CM code set, and each January, review the new CPT code set and the Medicare fee schedule, then update your charge master and your claim edits.
S9083 and S9088: payer-specific urgent care codes
S9083 and S9088 are HCPCS “S” codes that some commercial payers recognize for urgent care, and neither is a Medicare billing code. If you bill them the way the old guide described, you may be billing something your payer never pays.
S9083 has the long descriptor “Global fee urgent care centers” and is listed as not payable by Medicare. It is a flat, global fee used under certain commercial contracts. S9088 identifies services provided in an urgent care center and is reported in addition to the code for the service itself. We read one payer policy that shows how this can work: Premera and LifeWise describe both codes as informational, used to indicate the place where services are rendered, and not reimbursed whether billed alone or with other services. That plan asks for the service to be reported with a CPT code and POS 20.
The takeaway is not that these codes are always unpaid. It is that the answer sits in each payer contract. A payer may require S9083 as a global fee in place of itemized E/M lines, may ignore S9088, or may do neither. Because a global fee pays the same amount for a minor and a major visit, a global contract changes how you should judge your own revenue per visit.
| Item | What it tells the payer | Where the rule comes from | What to check |
|---|---|---|---|
| POS 20 | The visit took place at an urgent care facility | CMS place of service code set | That your location is enrolled and set up as urgent care with each payer |
| E/M code (99202-99215) | The level of the visit, by MDM or total time | AMA CPT guidelines; CMS and MAC guidance | That the note supports the level you picked |
| S9083 | A global fee for an urgent care visit under some commercial contracts | HCPCS Level II; payer contract | Whether the contract uses it, and what it pays |
| S9088 | The service was provided in an urgent care center | HCPCS Level II; payer policy | Whether the payer pays, ignores or denies it |
Source: CMS (2003 transmittal); Noridian Medicare (accessed 2026); hcpcs.codes; Premera/LifeWise payment policy (last approved 2025). Payer contracts vary.
Procedures, tests and other services on the same visit
If a patient gets an E/M visit plus a procedure, a test or supplies on the same day, each service can be reported only if the payer treats it as separately identifiable and the documentation backs it up. The North Dakota policy above says an urgent care center may bill for any additional services rendered during the visit that are separately identifiable from the E/M service, and that payment is subject to routine claim editing, including incidental or mutually exclusive logic.
In plain terms: a payer’s software may bundle a minor procedure into the visit, and a modifier is often how a biller tells the payer the two services really were separate. Which modifier applies, and when, depends on the payer. Our guide to modifiers 25 and 59 explains how the two differ, and the CMS-1500 claim form guide shows where these codes sit on a professional claim.
Check the note before the code
A procedure code on a claim is only as safe as the note behind it. If the note does not show a separate decision, a separate problem or a separate procedure, an auditor can treat the extra line as unsupported. Train providers to document the reason for each added service in their own words.
Upcoding and downcoding: why accuracy cuts both ways
Upcoding means billing a higher level than the visit supports. Downcoding means billing lower, which leaves earned revenue on the table. Both come from the same cause: the chosen code and the documentation do not match.
Regulators watch the high-level end. In a 2012 report on 2001 through 2010 data, the HHS Office of Inspector General found that physicians’ use of higher-level E/M codes grew across every type of E/M service, and it identified about 1,700 physicians who consistently billed higher-level E/M codes in 2010. OIG did not decide whether those claims were inappropriate, but it recommended continued physician education and contractor review of E/M billing. The report is old and not specific to urgent care. We cite it because it shows what reviewers look for: levels that sit above peers.
X fraud charges and fines. We do not give penalty amounts here, because they depend on the law, the payer and the facts of the case. If you are worried about a past billing pattern, talk to a healthcare attorney before changing anything.
“A coding level is a sentence the note has to finish. If the note and the code disagree, fix the note process first, not the code.”
HIPAA and billing: patient consent is not what many people think
HIPAA does not require a patient’s consent to use or share health information for treatment, payment or health care operations. The rule at 45 CFR 164.506 says a covered entity may use or disclose protected health information for treatment, payment, or health care operations, and that consent for these purposes is optional. A provider may obtain consent but is not required to.
The old guide told centers to always secure consent before disclosing health information to third parties. That is wrong for billing. Sending a claim to a payer is a payment use, and it does not need a signed consent under HIPAA. Other uses, such as marketing, can require a written authorization, and state law can add its own rules, so check those with counsel.
Good privacy practice still matters: limit access by role, log who views records, and use encrypted connections. If an outside company handles your claims, ask for a business associate agreement before it sees patient data. Our HIPAA compliance guide for medical billing goes deeper on vendor and staff controls.
In-house, outsourced or mixed: what to settle first
There is no single right answer for who should do urgent care billing. The right setup depends on your volume, your payer mix and whether you have a person who owns the process. Settle these questions before you compare vendors or hire.
| Setup | Where it fits | Main risk | Question to ask |
|---|---|---|---|
| In-house team | Centers with a stable biller and time to train | Coverage gaps when one person is out | Who checks the coder’s work? |
| Outsourced billing | Centers that want claims handled by a dedicated team | Less daily visibility into claims | How will we see each claim’s status? |
| Hybrid | Front desk in-house, claim follow-up outside | Handoffs between two teams | Who owns a claim when it is denied? |
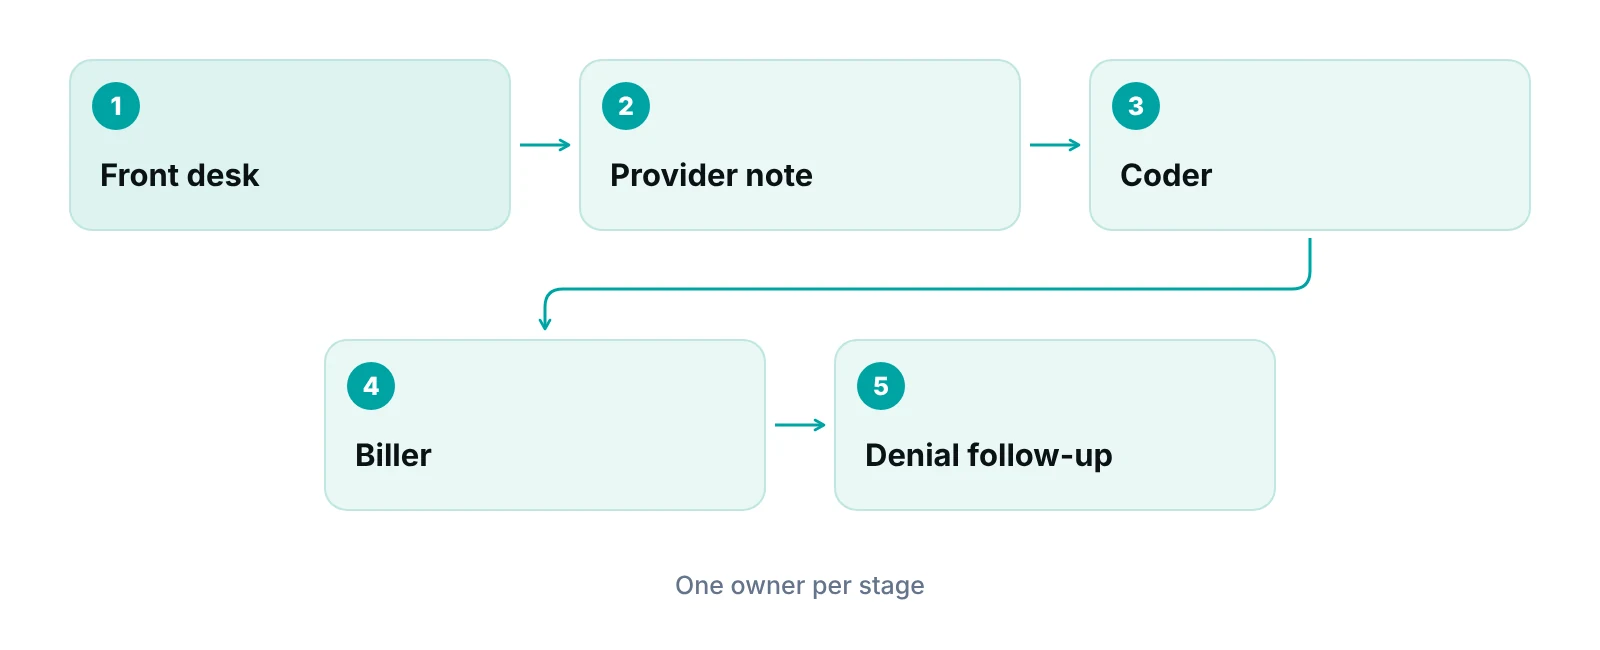
Whichever route you take, the claim data has to be complete before it leaves. A practice management system that tracks claims by stage can show who owns each claim and flag missing data before submission. Our clean claims guide covers the data points that most often decide whether a claim passes first time.
If you are weighing outside help, our post on why centers outsource urgent care billing lays out the reasons, and our medical billing services page describes how our team works with the EHR you already use. The EHR also affects billing quality; see how EHR systems help urgent care billing.
Estimate what your visit volume is worth
The free calculator turns your visits and payer mix into a rough view of where revenue may be leaking. It takes a few minutes and needs no account.
Our recommendations
- Start with a payer sheet. List each payer you bill, whether it pays S9083, S9088 or neither, and whether it requires POS 20 with office visit E/M codes. Write down where you found each rule. We would rather you have one page you trust than a memory of past calls.
- Match every E/M level to a sentence in the note. Pick MDM or time per visit and be able to show it. Train providers to document why the visit was moderate or high, not just that it was.
- Pull a small sample of notes each month. Have someone other than the coder compare ten or so charts against the codes billed. Look for levels that run high or low against what the notes support.
- Check your location setup with each payer. Confirm that your center is enrolled and loaded as urgent care. A POS mismatch is a setup error, and it repeats on every claim until someone fixes it.
- Do not bill S-codes on a hunch. If you are not sure a payer accepts S9083 or S9088, ask in writing. Keep the answer with the contract.
- Remove the consent myth from your front-desk script. Staff should not tell patients that billing needs a signed consent for HIPAA. Your notice of privacy practices and your state’s rules govern what you tell patients.
- Set a code-book review date. Put the January CPT review and the October ICD-10-CM review on the calendar with a named owner, and record what you changed.
Hold an urgent care claim until its data is complete.
Our portal tracks each claim by stage with an assigned owner, and it checks that required data is present before submission. Workflow rules can flag a claim for review or hold it at a stage.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Urgent care billing and coding comes down to a few steady parts: POS 20, an E/M level the note supports, the right treatment of payer-specific S-codes, and clear ownership of every claim. If you want a second reader on your process, see how our medical billing services and denial management services work, or ask for a free practice audit of your current setup.
Frequently asked questions
What is the POS code for urgent care?
The place of service code for an urgent care facility is 20. CMS defines it as a location, distinct from a hospital emergency room, an office or a clinic, that treats illness or injury for unscheduled, ambulatory patients seeking immediate attention. It has been in effect since October 1, 2003. Confirm each payer’s setup for your location.
Which E/M codes do urgent care centers use?
Most centers use the office or other outpatient E/M codes: 99202 to 99205 for new patients and 99211 to 99215 for established patients. Since 2021 the level is set by medical decision making or total time. Some payers have their own urgent care policies, so check each contract before you assume the same codes apply.
What are S9083 and S9088?
They are HCPCS Level II codes used by some commercial payers. S9083 is a global fee for urgent care centers and is not payable by Medicare. S9088 identifies services provided in an urgent care center. Some plans treat them as informational and do not pay them, so the contract decides how to use them.
Does HIPAA require patient consent before I send a claim to the insurer?
No. Under 45 CFR 164.506 a covered entity may use and disclose protected health information for treatment, payment and health care operations, and consent for those purposes is optional. Other disclosures can need written authorization, and state law may add rules. This is general information, so ask counsel about your situation.
Did urgent care coding change in 2024?
The big change to office E/M coding was in 2021, when MDM or time began to set the level. POS 20 dates from 2003. Code sets such as CPT and ICD-10-CM are updated every year, so review the current books and your payers’ notices instead of relying on a year-labeled article.
How do I know if I should outsource urgent care billing?
Start with who owns each claim today, how often claims are denied, and whether your team has time to follow up. If gaps show up in the same stage each month, outside help may fit. Ask any vendor how you will see claim status and whether it will sign a business associate agreement.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Place of Service Code for Urgent Care Facility (CMS Transmittal) — CMS (2003)
- Evaluation and Management (E/M) page — Noridian Healthcare Solutions (Medicare Administrative Contractor) (2026 (accessed 2026-10-14))
- E/M Guideline Changes — American Academy of Ophthalmology (2026 (accessed 2026-10-14))
- E/M Medical Decision Making payment policy — Louisiana Healthcare Connections (LDH repository) (2025)
- Payment policy: urgent care (S9083, S9088, POS 20) — Premera / LifeWise Health Plan of Washington (2025)
- HCPCS Code S9083 — hcpcs.codes (2026 (accessed 2026-10-14))
- Coding and billing guidelines for urgent care (archived) — Blue Cross Blue Shield of North Dakota (2022 (archived 2024-12-01))
- CMS May Refine Place of Service Code For Urgent Care — Journal of Urgent Care Medicine (2025-11-13)
- 45 CFR 164.506 — eCFR / HHS (2026 (accessed 2026-10-14))
- Coding Trends of Medicare Evaluation and Management Services (OEI-04-10-00180) — HHS Office of Inspector General (2012)
Disclaimer: This article is educational and is not legal, coding, billing or compliance advice. CPT is a trademark of the American Medical Association, and the code descriptions here are our own summaries. Payer rules and contracts vary, and rules can change. Check current CMS, AMA and payer sources before you bill.
