
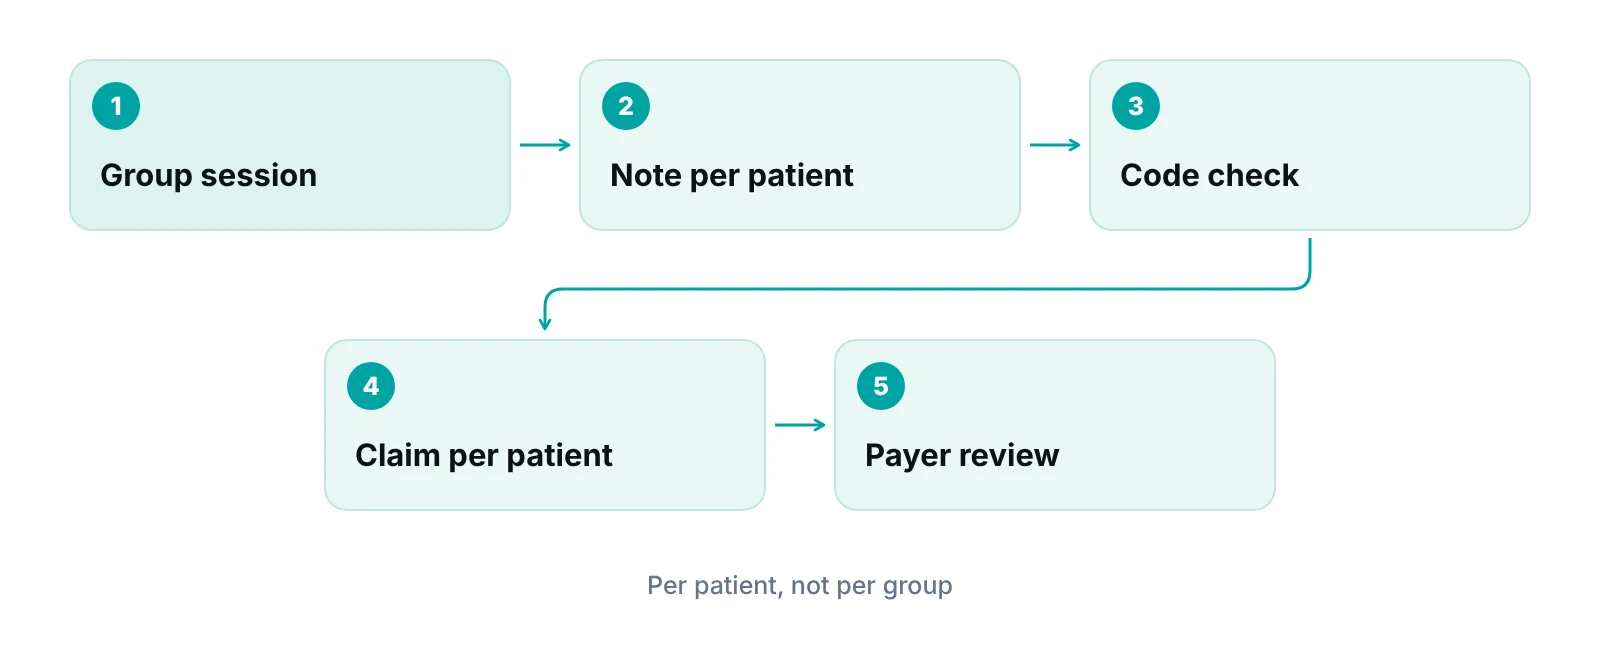
The 90853 CPT code description is group psychotherapy for several unrelated patients treated together, other than a multiple-family group. It is billed for each patient in the room, not once per group. Time limits, group size and note rules come from each payer, so check your contracts before you bill.
Most denials on group claims start with one of three things: the wrong code for who was in the room, a note that does not show treatment, or a payer limit nobody checked. This guide covers all three. It uses published payer documents, names the year of each, and leaves out dollar rates because they differ by contract. For the neighboring codes, see our guides to CPT 90832, CPT 90836 and the 90846 time range. For the whole code set, start with our mental health CPT codes guide.
Key takeaways
- 90853 reports group psychotherapy for patients who are not a multiple-family group; 90849 reports the multiple-family version.
- Payers bill and limit it differently: one county plan allows one unit per day, and one state manual lists a cap of 10 clients and billing per client.
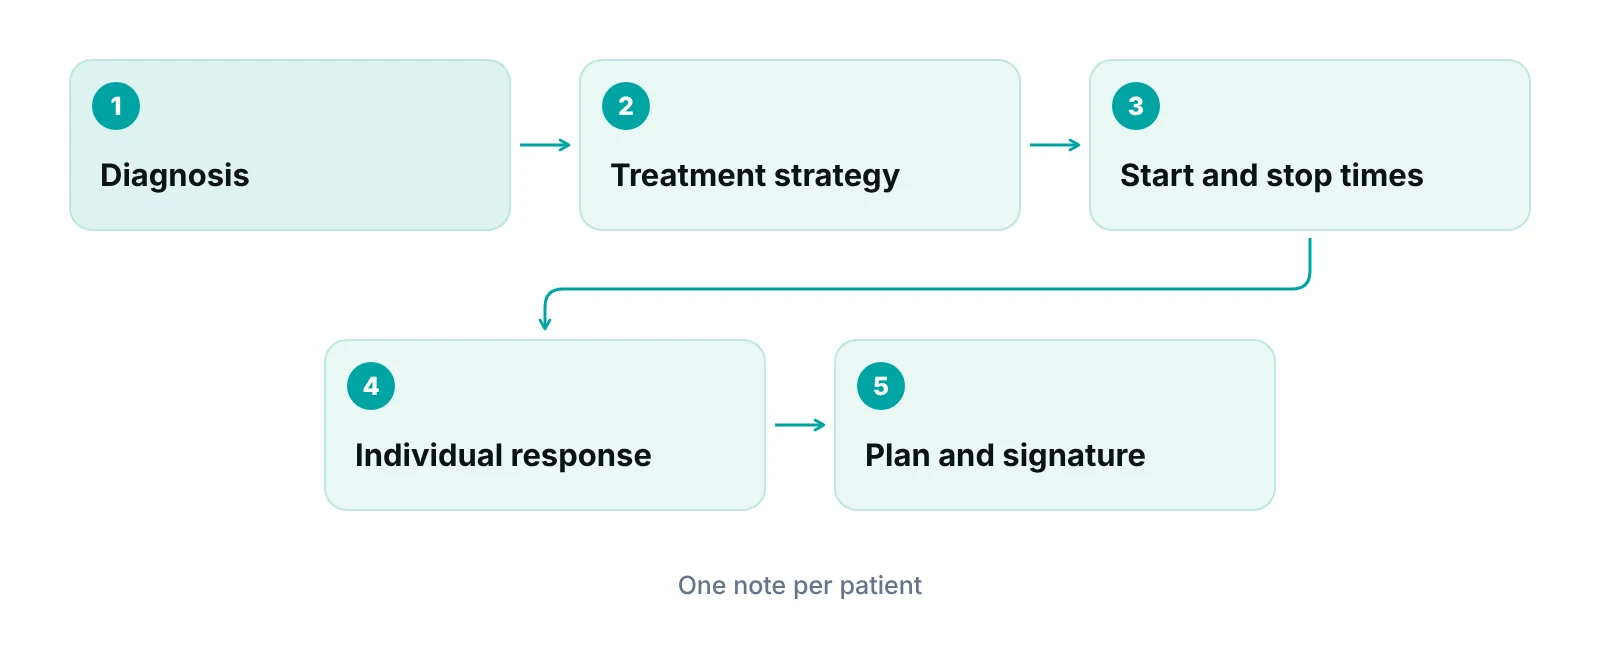
- A group note needs its own entry for each patient, with start and stop times, the diagnosis and that person’s response.
- A lecture with no interaction is not psychotherapy; show a treatment strategy and how it was used.
- Ask each payer in writing about telehealth modifiers, co-facilitators and same-day individual sessions.
What the 90853 CPT code description means
CPT 90853 reports group psychotherapy that is not a multiple-family group. Two payer documents word it almost the same way: a MassHealth provider manual lists it as group psychotherapy other than multiple-family group, and a San Francisco county behavioral health tip sheet lists it the same way (MassHealth; San Francisco Behavioral Health Services, 2024). We describe it in our own words because the AMA owns the official CPT text. Check the current CPT book for the exact wording.
In practice that means a licensed clinician treats several patients together, and the interaction among them is part of the treatment. The patients are not one family. Each person has their own diagnosis, their own goals and their own claim.
Therapy versus a class
A group that is mostly a lecture is a class, not psychotherapy. A 2026 audit tool published on a West Virginia utilization-review contractor’s site scores group notes on whether they show an identifiable group treatment strategy and a theoretical base for the interventions, and it scores the whole note zero if the note does not establish a behavioral health condition (Acentra Health, 2026). Whatever your payer, the safe reading is the same. Name the approach, show how the group used it, and tie it to each patient’s condition.
Who may lead it
The clinician types allowed to bill are set by the payer and by state licensure. Interns, trainees and peer facilitators are handled differently by each program. A peer-led support group is a different service from psychotherapy. Confirm the rendering clinician rules in your payer manual before you build a group schedule around anyone.
90853 vs 90849 and the family codes
Choose the code by who is in the room and who the treatment is for. If unrelated patients are treated as a group, 90853 fits. If several families are treated together as a group, 90849 is the multiple-family code (San Francisco Behavioral Health Services, 2024). Family therapy for one family uses 90846 or 90847.
A Medicare contractor’s fact sheet draws the line between the two family codes. It says the patient must be present for all or some of a family session, and it points to 90846 for family visits without the patient (CGS Administrators). Our post on the 90846 time range covers that code in detail.
| Code | Who is in the session | Typical example | What to check |
|---|---|---|---|
| 90853 | Several unrelated patients treated together | Anxiety group, grief group, skills group | Payer limits on size, minutes and units |
| 90849 | More than one family treated together as a group | Parent and teen groups run for several families | Medicare coverage; one 2012 contractor policy treats it as non-covered by default |
| 90847 | One family, with the patient present for all or some of the session | A couple or parent and child with the patient attending | Patient presence documented |
| 90846 | One family, patient not present | Parents learning to support a child | Time rules in the payer policy |
Sources: San Francisco Behavioral Health Services (2024); CGS Administrators fact sheet (2021); WPS policy PSYCH-014 (2012).
One caution on 90849. The 2012 policy from a Medicare contractor says 90849 is generally non-covered by Medicare and may be approved only on individual consideration (WPS policy PSYCH-014). That policy is old, so read the current local coverage determination for your contractor before you rely on it. Two sisters who happen to join the same anxiety group do not turn the session into 90849. The grouping is by clinical design, so document why the group was set up the way it was.
How payers limit 90853 claims
Payers set their own limits on units, minutes and group size, and the published numbers differ a lot. That is why a single rule of thumb, such as a fixed maximum group size, is risky. Table 2 shows four published examples. Use them as a reminder to look up your own contracts, not as a national standard.
| Payer document | What it says | Year |
|---|---|---|
| San Francisco county behavioral health tip sheet | One unit for 23 to 57 minutes of direct service; maximum one unit per day | 2024 |
| MassHealth LIBHC manual, subchapter 6 | Billed per client, not per group; maximum of 10 clients per group; 90 minutes listed as session length | See manual |
| Vermont Medicaid (DVHA) presentation | Unit is one session under the National Correct Coding Initiative; Medicaid allowed one group session per day from July 1, 2015 | 2016 |
| WPS Medicare policy PSYCH-014 | Covered diagnosis required; psychotherapy documentation rules apply; recording therapy time recommended | 2012 |
Sources: San Francisco Behavioral Health Services tip sheet (2024); MassHealth (Commonwealth of Massachusetts); Vermont DVHA (2016); WPS via CMS Medicare Coverage Database (2012).
Three lessons follow. First, units differ: one program counts a session, another counts a band of minutes. Second, per-client billing is common, so each patient’s claim must stand on its own note. Third, older policies stay online long after they are replaced, so confirm the date of anything you rely on (MassHealth; San Francisco, 2024; Vermont DVHA, 2016).
Do not copy a number from a blog
Group size, minutes and units are payer rules, not CPT rules. Pull them from your own contract, provider manual or Medicare contractor policy, and save the page with its date.
Money follows the same logic. Group payment is set per patient under each contract, so revenue depends on how many billable patients attend and how often. A small group may not cover a clinician’s time compared with individual sessions, and a full group may. Run your own payer fee schedule through our revenue calculator rather than relying on a generic range.
What a compliant group note includes
Every patient in the group needs their own note. Medicare contractor guidance says exact times must be documented, that the person performing the service must sign with credentials, and that late signatures should not be added to the record (CGS Administrators). A West Virginia reviewer’s 2026 tool adds checks for individualized response, interval history, a plan for continued group therapy and frequency matched to assessed need (Acentra Health, 2026).
| Element | What to write | Source |
|---|---|---|
| Medical necessity | The behavioral health diagnosis that the group addresses | WV Acentra tool (2026); WPS policy (2012) |
| Treatment strategy | The named approach used in this session | WV Acentra tool (2026) |
| Start and stop times | Exact times, date and location | CGS fact sheet (2021); WV Acentra tool (2026) |
| Individual response | How this patient took part and responded | WV Acentra tool (2026) |
| Plan and frequency | Whether to continue the group and how often | WV Acentra tool (2026) |
| Signature | Name, signature and credentials of the clinician | CGS fact sheet (2021) |
Sources: Acentra Health 90853 group psychotherapy audit tool (April 2026); CGS Administrators (2021); WPS policy PSYCH-014 (2012).
A weak note and a better one
A line such as “patient participated in group” tells a reviewer nothing. A better line names the topic and the patient’s part in it, for example: “Discussed boundary setting using the group’s assertiveness framework. Patient described difficulty declining requests from relatives and practiced a refusal statement with a peer.” The sentence is specific to the person, and it ties to the treatment plan. Copying one session summary into every chart removes exactly the individual detail that reviewers score.
“A group note that could belong to any member of the group does not support a claim for any one of them.”
For wider documentation habits, see our post on clear documentation in medical billing.
Common 90853 claim problems to prevent
Most group claim problems are preventable at the scheduling and charge-entry stage. If you want help with claim submission and follow-up for a behavioral health practice, our medical billing services cover charge entry, claim scrubbing and follow-up.
- Wrong code for the room. A session of several families is 90849, not 90853. Decide the grouping when the group is designed, not when the claim is built.
- Two clinicians, one group. Co-facilitated groups are handled differently by different payers. Ask each payer in writing which clinician may bill for which patients before both of you submit.
- Telehealth set-up. Place of service codes and modifiers for video groups depend on the payer. Our modifier 95 telehealth billing guide explains how that modifier is used, and each payer still decides what it accepts.
- Same-day individual and group sessions. Whether both can be paid on the same date is a payer rule. Keep separate notes and separate times, and check the payer’s policy first.
- Diagnosis that does not fit. The diagnosis should support why group treatment is appropriate for that patient. Review the clinical fit with the treating clinician, not only the code list.
- Missing signatures or times. These are the easiest edits to prevent and the hardest to fix after the fact.
When a group claim is denied anyway, our denial management services and the denial guides on this site can help you trace whether the cause was coding, documentation or a payer limit.
Is running groups worth the extra work?
Groups can make sense for a practice, but the benefit depends on attendance, payer rates and how much note time the clinician can protect. The trade-offs below are operational, not clinical.
- Capacity: one clinician treats several patients in a block of time, which can help access when individual slots are full.
- Paperwork: each attendee needs a note and a claim line, so documentation time grows with group size.
- Scheduling: a group needs enough patients free at the same time, and a few cancellations change the economics.
- Payer limits: units per day and group size caps may cap what a session can earn.
- Privacy: set expectations for confidentiality at intake and in the group agreement.
If your practice is mostly behavioral health, see how we think about these workflows on our page for behavioral and mental health billing operations.
Want a second pair of eyes on your group claims?
We can review how your group sessions are coded, documented and followed up, and show where denials start.
Our recommendations
- Save the payer rule with its date. For each payer, store the page or manual section that sets units, minutes and group size, plus the date you read it. Check it again at contract renewal.
- Build a group note template with locked fields. Make diagnosis, start time, stop time, treatment strategy, individual response and plan required fields. Leave the response field free text.
- Decide the code when the group is designed. Write down whether the group is unrelated patients (90853) or several families (90849), and keep that decision with the group description.
- Settle co-facilitator billing before the first session. Ask each payer in writing who may bill when two clinicians run a group, and keep the answer on file.
- Check the telehealth set-up per payer. Confirm place of service codes and modifiers for video groups with each payer before the first virtual session.
- Review a sample of group claims every quarter. Pull a few claims for each group and compare the note, the times and the claim line. Fix patterns, not single claims.
Bottom line
The 90853 CPT code description is simple to state and easy to get wrong: group psychotherapy, billed per patient, with limits and note rules set by each payer. Get the grouping, the times and the individual note right, and most group denials never happen. If you want help, our medical billing services and denial management teams work on behavioral health claims, and you can contact us to start with a free practice audit.
Frequently asked questions
Can I bill an individual session and a group session on the same day?
It depends on the payer. Some pay both when the sessions are separate with separate times and notes, and others limit sessions per day. Check the payer’s policy and document each session on its own. Do not overlap the times, and make sure each note can stand alone if the payer requests records for only one of them.
Is there a maximum group size for 90853?
The payer documents we reviewed set their own limits. One state manual lists a maximum of 10 clients per group, and another source we reviewed did not address size at all. Look up the limit in your own contract or provider manual.
Is 90853 a timed code?
Not in every program, and the sources disagree on the unit. A San Francisco county tip sheet allows one unit for 23 to 57 minutes, while a Vermont Medicaid presentation treats the unit as one session. Medicare contractors still expect exact times in the record. Document start and stop times either way, and confirm in your contract how the payer counts a unit before you set group length.
Can a peer-led support group be billed as 90853?
Billing depends on the payer’s list of eligible clinicians and on whether the session is psychotherapy. A peer-led support group is a different service. Confirm eligible rendering clinicians in your payer manual before billing, and keep that confirmation with the group’s records.
Which modifier do I use for a telehealth group?
Modifiers and place of service codes for video groups vary by payer, so ask each payer what it expects before the first virtual session. Our modifier 95 guide explains how that modifier is used.
Can two clinicians both bill for the same group?
Payer rules differ. Ask in writing before both clinicians submit claims for the same patients, because duplicate claims for one session can be denied. Keep the written answer in the payer file, and share it with both clinicians and the biller so everyone follows the same rule.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- SMHS CPT Code Tip Sheet — San Francisco Behavioral Health Services (sf.gov) (2024)
- Licensed Independent Behavioral Health Clinician (LIBHC) Manual, Subchapter 6 — MassHealth, Commonwealth of Massachusetts (undated)
- Outpatient Psychiatry & Psychology Services Fact Sheet (LCD L34353) — CGS Administrators, LLC (2021)
- Psychiatry and Psychology Services, policy PSYCH-014 (L30489) — WPS Insurance Corporation via CMS Medicare Coverage Database (2012)
- Group Therapy Presentation (H.875 workgroup) — Vermont Department of Vermont Health Access (2016)
- 90853 Group Psychotherapy audit tool (PP: 90853) — Acentra Health, West Virginia ASO (2026)
Disclaimer: This article is for educational purposes only. It is not legal, coding, clinical or compliance advice. Payer rules differ by contract, state and year. Confirm each requirement with your payer and a qualified coder before you bill.
