
Urology Specialty

Urology Billing Services, Front Desk and Patient Growth in One Plan

Coding and claims for office procedures, physician-administered drugs and in-office labs, plus prior authorization, patient marketing and a claims portal, built on CMS rules and your payers' own policies.
  • Works inside your current EHR
  • US practice time zone, every shift
  • Weekly KPI reporting, or on your schedule
Urology billing dashboard showing denials by reason, drug units with JW/JZ, pending authorizations, A/R days and consults

Quick answer

Urology billing services manage the claims a urology practice creates: office cystoscopy and urodynamics, prostate biopsy and pathology, physician-administered drugs billed by unit with the JW or JZ modifier, CLIA-certified lab tests, screening limits and prior authorization. RCM Finder pairs that billing with front-desk assistants, patient marketing and a claims portal.

Disclaimer: This page is educational and is not legal, coding or compliance advice. Medicare billing articles, NCDs, fee schedule rules, the WISeR Model and commercial payer policies change often and vary by contractor, state and plan. Verify every code, limit and rule against your Medicare contractor's current documents, your payer contracts and the current CPT and HCPCS code sets before billing.

Why urology billing is different

Urology billing is different because one practice runs several revenue streams at once: office procedures, diagnostic tests, physician-administered drugs, an in-office lab and preventive screening. Each stream has its own coding rule.

One morning can bring a cystoscopy with a global period, a urodynamic study with professional and technical parts, a hormone injection billed by unit and a screening PSA that depends on the date of the last one. For a plain-language checklist, see our do's and don'ts of urology billing.

What changed for urology in 2026

The AMA's CPT 2026 code set made 418 changes, including 84 deletions, effective January 1, 2026. CMS's CY 2026 fee schedule final rule (Federal Register, November 5, 2025) confirms that CPT deleted prostate needle biopsy code 55700 and added nine new codes, 55707 to 55715, that separate transrectal, transperineal, MRI-fusion and in-bore CT- or MRI-guided biopsy.

CMS's CY 2026 Physician Fee Schedule final rule fact sheet (October 31, 2025) set the conversion factor at $33.40 for clinicians who are not qualifying APM participants, up from $32.35, and $33.57 for those who are. It also cuts work RVUs of services that are not time-based by a -2.5% efficiency adjustment; E/M and other time-based services are exempt.

The four pillars, built for a urology practice

A urology practice needs patients coming in, a front desk that clears each visit, billing that gets units and modifiers right, and software that shows every claim.

Revenue leaks at the handoffs: a screening PSA drawn a month early, an injection billed without JZ, a prosthesis booked in a WISeR state with no request. We run all four pillars on one set of payer rules.

Pillar 1 · Healthcare Marketing

Healthcare Marketing for urology practices

Our healthcare digital marketing builds demand for kidney stone, prostate, incontinence and vasectomy care through local SEO, Google Ads and reputation work that fits Google's drug and sexual health ad policies.

  • A Google Business Profile per office
  • Condition and procedure pages, not drug names
  • KPI: booked consults by source
Explore Healthcare Marketing
Pillar 2 · Virtual Medical Assistants

Virtual Medical Assistants for urology front desks

Our virtual medical assistants for urology run your front desk on your practice's time zone, check eligibility and the last screening date, and start imaging, drug and WISeR authorizations.

  • Screening dates checked before the PSA draw
  • WISeR tracking numbers saved for the claim
  • KPI: visits cleared before the date of service
Explore Virtual Medical Assistants
Pillar 3 · End-to-End RCM

End-to-End RCM for urology claims

Our end-to-end urology revenue cycle management covers coding support, claim scrubbing, denials and A/R, with extra checks for cystoscopy bundling, drug units, JW or JZ, modifier 26 and CLIA on lab lines.

  • Drug units matched to the dose given
  • 2026 prostate biopsy codes in every template
  • KPI: denials by reason and A/R days
Explore End-to-End RCM
Pillar 4 · Practice Management System

Practice Management System for urology billing

Our practice management system tracks every claim by stage, applies specialty-aware billing logic per claim, checks data completeness before submission and flags payments below the expected amount.

  • Rules that hold a claim missing a modifier
  • Role-based permissions and an audit log
  • Early access: appointment booking with a calendar view
Explore Practice Management System

Find where your urology claims leak

We review recent procedure, drug and lab claims, denials and authorization logs, then show what to fix first. Pricing is quoted after the audit.

Get a Free Practice Audit

Urology service families: codes, global periods and denial triggers

Most urology denials trace to a few rules: cystoscopy bundling, same-day visits, drug units, screening frequency and lab certificate level. Codes are in our own words (the AMA owns CPT descriptors); check the current code set before billing. For diagnoses, see our ICD-10 urinary tract infection codes guide.

Urology service families: code examples, billing rules and typical denial triggers
Service familyCode examples (our wording)Billing rule to checkTypical denial trigger
Prostate cancer screeningG0102 (screening rectal exam); G0103 (screening PSA)Men over 50; at least 11 months after the month of the last paid testTest inside the 11-month window
Office cystoscopy52000 (diagnostic); 52332 (stent placement); 52310 (stent or stone removal from bladder or urethra)Diagnostic look included in surgical cystoscopy; 52310 not billed with other cystoscopy codesBoth billed together; catheter insertion (51701-51703) billed on top
Urodynamics51728, 51729 (pressure study with voiding pressures); 51741 (complex uroflow); 51797 (add-on)Highest-value study first, others with 51; residual included; 26 for hospital readingsSeparate residual or second flow charge; EMG billed with biofeedback
Prostate biopsy and pathology55707 (transrectal); 55708 (with MRI fusion); 55709 (transperineal); G0416 (pathology)55700 deleted for 2026; no separate guidance code if included55700 on a 2026 claim; guidance billed twice
Hormone therapyJ9217 (leuprolide depot, 7.5 mg); J9155 (degarelix, 1 mg); 96402 (injection)Whole billing units; JZ, or a JW line, on single-dose containersMissing JW or JZ; units that do not match the dose
Bladder instillation51720 (instillation); J9030 (BCG, 1 mg)0-day procedure; routine pre-instillation check is not a separate visitModifier 25 visit on routine instillation days
Bladder botulinum toxin52287 (cystoscopy with bladder injection); J0585 (onabotulinumtoxinA, 1 unit)Covered diagnosis group (Noridian A57185); dose given and discarded recordedDiscarded units undocumented or not on a JW line
In-office labDipstick urinalysis (waived); urine sediment microscopy (PPM)Certificate covers the highest complexity test you runTest above the certificate's level

Sources: 42 CFR 410.39; NCD 210.1; CMS NCCI Policy Manual Ch. VII (2026); CMS MLN907166 (2025); CMS CY 2026 PFS final rule, Federal Register (2025); AUA News (2023); AUGS (2018); Noridian modifier 26 page; Noridian A57185 (2026); CMS JW/JZ FAQ; 42 CFR 493; AAPC code summaries. Rules vary by contractor and payer.
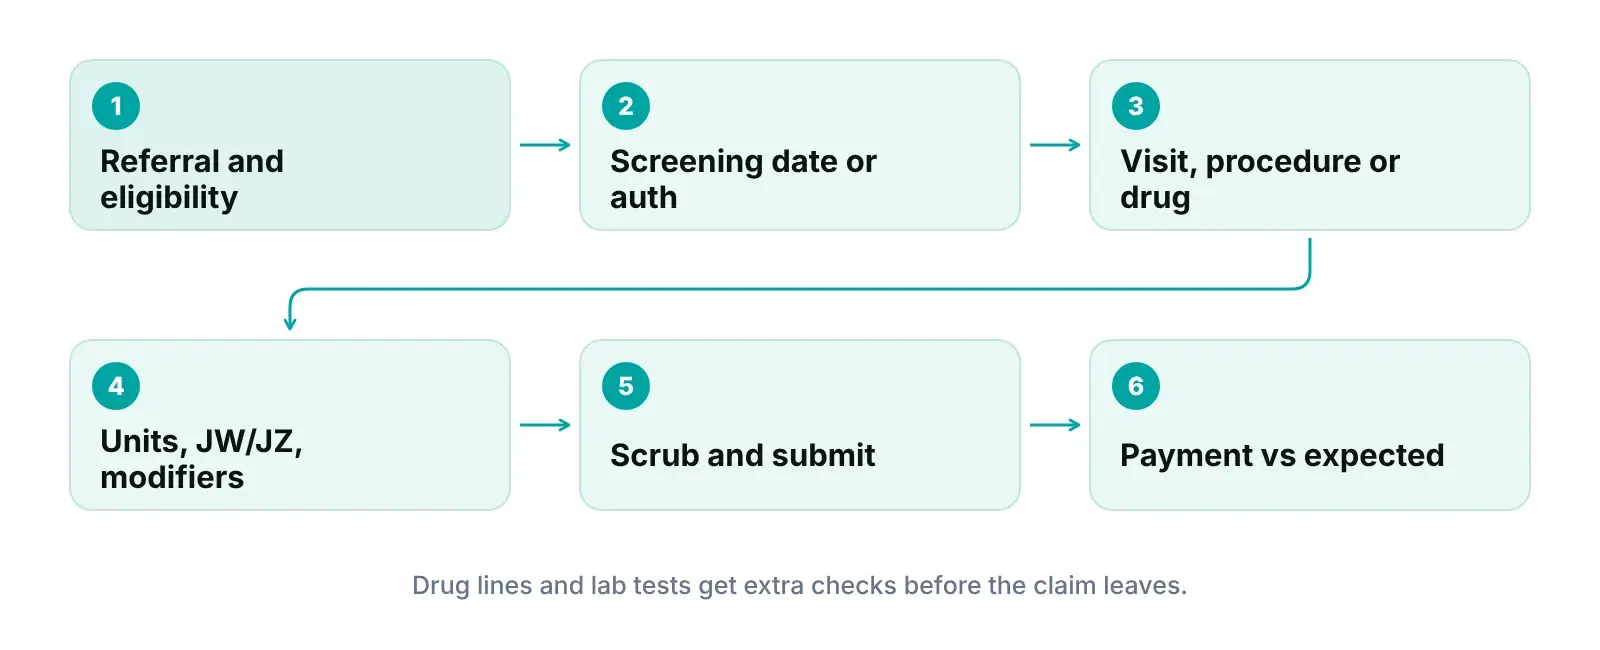
Diagram of a urology visit moving from eligibility and screening-date checks to drug units, modifiers and payment review
Where a urology claim is checked, from the referral to the payment review.

Global periods and same-day visits

CMS's global surgery booklet (December 2025) puts endoscopies and some minor procedures in a 0-day global period; other minor procedures carry 10 days and major ones 90. AUA News lists bladder instillation (51720) and urodynamics as 0-day office procedures. Confirm each code in CMS's fee schedule look-up tool.

The 2026 NCCI Policy Manual includes a same-day E/M, and the decision to do the procedure, in a minor procedure's payment. A significant, separately identifiable visit takes modifier 25, and new-patient status alone is not enough. For a 90-day procedure, the decision visit takes modifier 57. See our guide to modifiers 25, 59 and 91.

Urodynamics

The AUGS coding fact sheet (last updated January 2018) lists the highest-value study first, with modifier 51 on the others except add-on 51797. Post-void residual is included and one flow study is allowed per day. For a study done in a hospital, Noridian has the physician bill the reading with modifier 26 while the hospital bills the technical part. AUGS says the billing physician must be in the office; CMS's 2026 final rule now permanently allows direct supervision of diagnostic tests by real-time audio and video.

Prostate biopsy and pathology

For 2026 dates of service, stop using 55700. In CMS's CY 2026 final rule, 55707 is a transrectal, ultrasound-guided sextant biopsy, 55708 is the transrectal version with MRI-fusion guidance and 55709 is the transperineal, ultrasound-guided version. Later codes in the family cover transperineal fusion, targeted-lesion-only and in-bore CT- or MRI-guided biopsy. NCCI bars a separate guidance code when the descriptor includes it. HCPCS G0416 covers pathology for a prostate needle biopsy; check which payers accept it. Reading your own slides needs a CLIA certificate above waiver or PPM. See our pathology CPT codes guide.

Drugs and in-office labs: J-codes, JW and JZ, and CLIA

Drugs are billed by HCPCS unit, not by vial, with JW or JZ on single-dose containers. Lab tests are paid only when the CLIA certificate covers them.

Units and the J-code

Per AAPC's summaries, leuprolide depot J9217 is billed per 7.5 mg and onabotulinumtoxinA J0585 per unit, so units must match the dose. CMS does not use fractional units. Administration is coded separately, such as 96402 for a hormonal cancer drug injection or 51720 for a bladder instillation. Our J-codes guide covers the basics.

JW and JZ on single-dose containers

Per CMS's JW and JZ FAQ, JZ has been required since July 1, 2023, when nothing is discarded from a single-dose container. Since October 1, 2023, claims without the right modifier may be returned. For waste, bill the dose on one line and the discarded amount on a second JW line, and document it in the record. Multiple-dose containers and packaged hospital or ASC drugs are out of scope.

Noridian's article A57185 (revision effective April 9, 2026) applies the same rules to bladder botulinum toxin injections.

Match the CLIA certificate to the test menu

Under CMS's CLIA program, a lab must be certified to be paid by Medicare or Medicaid, and the application page says to match the certificate to your highest complexity test. Dipstick urinalysis is waived (42 CFR 493.15); urine sediment exams are provider-performed microscopy (42 CFR 493.19).

Per the CLIA definitions, a waiver covers only waived tests, a PPM certificate adds microscopy, and higher complexity needs registration, compliance or accreditation. Medicare edits lab claims at the certificate level, per MLN Matters MM14273 (November 2025). See our laboratory billing and coding guide.

Prior authorization and payer rules to check before the visit

Clear authorizations and frequency limits before scheduling: advanced imaging, specialty drugs, implants in WISeR states and Medicare screening dates.

Since January 1, 2026, the CMS-0057-F final rule has required Medicare Advantage, Medicaid and CHIP plans to decide expedited requests within 72 hours and standard ones within seven calendar days, with a specific reason for any denial. Exchange plans are excluded from these timeframes, and drugs from the rule.

The WISeR guide sets decisions within 3 days (standard) or 2 days (expedited). The tracking number goes on the claim; without a request, the claim goes to pre-payment review.

UnitedHealthcare says CT, MRI, MRA and PET may need prior authorization outside emergency, observation, urgent care and inpatient settings; its Medicare Advantage plans exempt CT, MRI and MRA.

In the AMA's 2025 survey of 1,000 physicians, released May 13, 2026, physicians averaged 40 prior authorizations and 13 hours of staff and physician time a week.
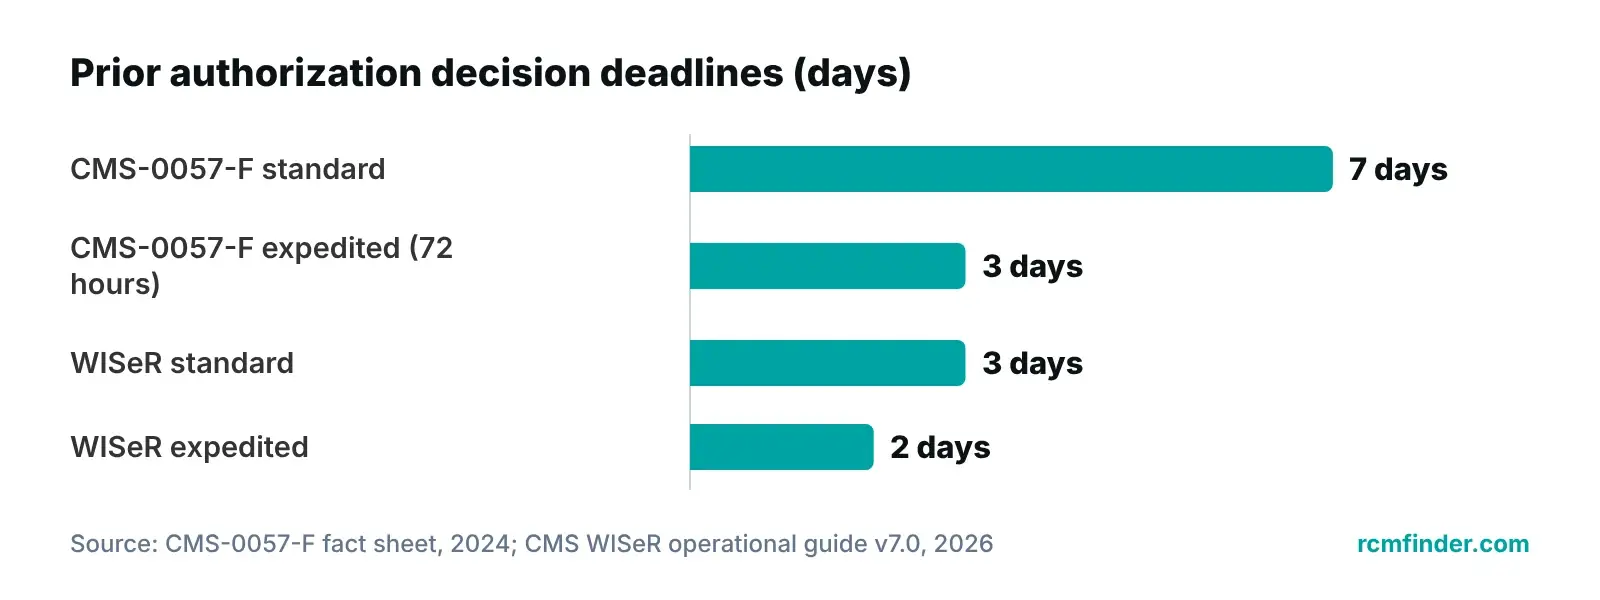
Bar chart of prior authorization decision deadlines in days under CMS-0057-F and the CMS WISeR Model
Maximum days to a decision. CMS-0057-F covers Medicare Advantage, Medicaid and CHIP; WISeR covers Original Medicare in six states.
Pre-visit checklist: urology screening limits and prior authorization rules our VMAs check
RuleSourceWhat the VMA checks before the visit
Screening PSA and rectal exam: men over 50; 11 months after the month of the last paid test42 CFR 410.39; NCD 210.1; CMS ABN pageLast paid screening date; an ABN when Medicare is expected to deny
MA, Medicaid and CHIP: 72-hour expedited and 7-day standard decisions with a specific denial reasonCMS-0057-F (from Jan 1, 2026)Request and due dates logged; follow-up on the due date
WISeR states: penile prostheses, sacral nerve stimulators and incontinence devices need a request or face pre-payment reviewCMS WISeR guide v7.0 (2026)Patient's state and Original Medicare status; tracking number saved
CT, MRI, MRA and PET may need plan approval outside emergency, observation, urgent care and inpatient careUnitedHealthcare radiology page (2026)Ordered study checked against the member's plan
Listed specialty drugs given in the office need approval; without it, claims may denyUnitedHealthcare specialty drug program (2026)Approval on file before the injection

Sources: 42 CFR 410.39; NCD 210.1; CMS ABN page (2026); CMS-0057-F fact sheet (2024); CMS WISeR guide v7.0 (2026); UnitedHealthcare radiology and specialty drug pages (2026). Always check the member's current plan.

For the full workflow, read our prior authorization guide for providers.

See what denials and delays cost you

Enter your claim volume and denial rate to estimate what your urology practice is losing.

Open the Revenue Calculator

Marketing a urology practice within ad and privacy rules

Urology marketing should promote conditions, procedures and access to care, not prescription drugs, and keep tracking away from patient data.

Google's Healthcare and medicines policy restricts prescription drug terms in ads, keywords and landing pages. Its sexual health and wellness policy allows prescription erectile dysfunction drug ads only in limited cases, only to users 18 or older, and not with a focus on sexual pleasure or enhancement.

HHS guidance on online tracking says tracking on appointment pages can collect protected health information, the vendor then needs a Business Associate Agreement, and a cookie banner is not a HIPAA authorization. A June 2024 court order vacated part of it. We keep tracking off appointment and referral forms unless the vendor signs a BAA.

  • Condition pages for kidney stones, enlarged prostate, incontinence and blood in the urine
  • Vasectomy and stone treatment pages that say who is a candidate
  • Review replies that never confirm someone is a patient
  • KPIs: booked consults by source; days from referral to first visit

In-house team, billing-only vendor or four-pillar partner?

Stay in-house if you have experienced urology coders and front-desk time for authorizations. A billing-only vendor fits when claims are the only gap. A combined partner fits when problems start at scheduling.

Decision table: which billing model fits a urology practice?
JobIn-house teamBilling-only vendorFour-pillar partner (RCM Finder)
Screening dates and frequency limitsFront desk, if someone checksUsually found at denialVMA checks the last paid date before the test
Drug, imaging and WISeR authorizationsClinical staff between patientsUsually left to the practiceVMA starts each request and logs the decision
Drug units and JW or JZDepends on who enters chargesFixed on the claim after the factChecked against the dose before submission
Lab claims and CLIALab managerBilled as sentCertificate level checked on lab lines
Referral growth and reviewsA separate agency, or nobodyNot includedMarketing pillar tied to booked consults
Cost structureSalaries, benefits, turnoverVaries; ask how fees are setQuoted after a free practice audit

Whichever model you choose, ask for denials by reason and payer. If you need only one pillar, the audit will say so.

How it works

We start with a free audit and change nothing until you see the findings. We build our billing pipeline around how claims actually move through a practice: registration, charge entry, submission, payment and follow-up. For urology, we add the checks on this page.

  1. 1

    Free practice audit

    We review recent procedure, drug and lab claims, denials and authorization logs, and check charge templates for deleted codes.

  2. 2

    Business Associate Agreement and access

    We put a Business Associate Agreement in place before accessing patient data. Then we work inside your existing EHR (for example PrognoCIS, eClinicalWorks or athenahealth).

  3. 3

    Payer-rule map

    Your contractor's articles, plan authorization lists, WISeR status and CLIA certificate become a pre-visit checklist and portal workflow rules.

  4. 4

    Front desk and billing go live

    VMAs check screening dates and start authorizations. Claims are scrubbed, submitted and worked through denials and A/R.

  5. 5

    Weekly KPI review

    We review denials, A/R days, drug-line underpayments and visits cleared in advance. Add Own Practice Management System for more depth.

Talk to us about your urology practice

Tell us your procedure mix and hardest payer. We will tell you honestly whether we fit.

Call +1 (302) 556-2288

Compliance: what to ask any urology billing company

Any billing vendor that handles your patients' data is a HIPAA business associate. Get a Business Associate Agreement before any access, and check how access is limited and logged.

HHS guidance names billing as business associate work; subcontractors need their own agreement. The minimum necessary standard limits use to what each task needs. The Security Rule's technical safeguards require access control, audit controls, integrity controls, person or entity authentication and transmission security.

  1. Will you and your subcontractors sign a Business Associate Agreement before any access?
  2. How do you limit each person's access, and can we see the audit log?
  3. Who codes our claims, and what credential and urology experience do they have?
  4. How do you set drug units and choose between JW and JZ?
  5. Which contractor articles and plan lists do you track?
  6. Can we export our data if we leave?

We use role-based access, audit logging and encrypted (HTTPS) connections, and we put a Business Associate Agreement in place before accessing patient data. For your own side, use our HIPAA compliance checklist for medical practices.

Who this is for, and who it is not for

We would rather tell you now than after you sign. Here is where we fit and where we do not.

A good fit if you are

  • Urology groups doing cystoscopy, urodynamics and biopsies in the office
  • Practices that give hormone therapy, bladder instillations or botulinum toxin injections
  • Groups that bill in-office lab tests under their own CLIA certificate
  • Practices in the six WISeR states handling Original Medicare requests
  • Billing companies that want a shared portal for urology clients

Probably not a fit if you are

  • Hospital-employed urologists whose billing the hospital controls
  • Practices that want claims billed without changing any front-desk process
  • Practices looking for promised collection rates; we report measured KPIs instead
  • Groups that need a credentialing module or in-portal real-time eligibility today (coming next)

Expert recommendations from our operations team

What we would do first if we were running your practice's revenue cycle tomorrow.

  1. 01

    Remove 55700 from every 2026 template

    We check charge templates for deleted codes first. Biopsy notes should state the approach and any MRI fusion.

  2. 02

    Check the last screening date before the draw

    Medicare pays for a screening PSA or rectal exam only after at least 11 months have passed since the month of the last paid one. We look it up before the visit.

  3. 03

    Record every vial

    For each single-dose drug, the note should show the dose given and any amount discarded, to support units and JW or JZ.

  4. 04

    Save modifier 25 for real separate problems

    Routine pre-procedure checks belong to a 0-day procedure. We add 25 only for a significant, separately identifiable visit.

  5. 05

    Know your WISeR status

    In the six WISeR states, we list your services in the model and save each tracking number for the claim.

  6. 06

    Re-run your 2026 fee expectations

    We load the CY 2026 conversion factor and efficiency adjustment into expected amounts for underpayment flags.

Frequently asked questions

What do urology billing services include?

They cover coding support, claim scrubbing, submission, denial management and A/R follow-up for urology visits, procedures, drugs and lab tests. A good service also checks screening dates, prior authorizations, drug units with the JW or JZ modifier and the lab's CLIA certificate before claims go out. RCM Finder adds front-desk assistants, patient marketing and a claims portal, so one team owns the process from referral to payment.

How often does Medicare pay for PSA screening and a digital rectal exam?

Once every 12 months for men over 50. Federal rules let Medicare pay only after at least 11 months have passed since the month of the last paid screening of that type. Medicare.gov says patients pay nothing for the screening PSA blood test, while the rectal exam is subject to the Part B deductible and 20% coinsurance. G0103 is the screening PSA code and G0102 the screening rectal exam.

Can we bill an office visit on the same day as a cystoscopy?

Only when the visit is significant and separately identifiable. CMS's NCCI manual says a same-day E/M is included in a minor procedure's payment, including the decision to do it, and new-patient status alone is not enough. A separate problem, documented on its own, can be billed with modifier 25. For a 90-day procedure, the visit that leads to the decision to operate uses modifier 57.

When do we use the JW and JZ modifiers on drug claims?

Use them on separately payable Part B drugs from single-dose containers. JZ says nothing was discarded. JW goes on a second claim line, with the same drug code, for the discarded amount. CMS has required JZ since July 1, 2023, and claims missing the right modifier may be returned. Document the discarded amount in the medical record. The modifiers do not apply to multiple-dose containers.

Do urology services need prior authorization in traditional Medicare?

In six states, some do. Since January 1, 2026, CMS's WISeR Model has required prior authorization, or pre-payment review, for selected Original Medicare services in Arizona, New Jersey, Ohio, Oklahoma, Texas and Washington. Its list includes penile prostheses, sacral nerve stimulators for urinary incontinence and incontinence control devices. Medicare Advantage plans set their own lists, now with 72-hour and seven-day decision limits.

Do you work inside our EHR, and is outsourcing safe under HIPAA?

Yes. Our team works inside your existing EHR, for example PrognoCIS, eClinicalWorks or athenahealth. HIPAA treats a billing vendor as a business associate, so a Business Associate Agreement must be in place before it receives patient data. We put a Business Associate Agreement in place before accessing patient data, and we use role-based access, audit logging and encrypted (HTTPS) connections. Pricing is quoted after a free practice audit.

No cost, no commitment

Get your free practice audit

Tell us about your practice. A member of our operations team replies within one business day.

  • A review of your recent claims, denials and A/R aging
  • Where your front desk and prior authorizations slow payment
  • A prioritized fix list you keep, whether or not you hire us

Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.

Tell us about your practice

RCMFinder Master Intake Form
AA

About the author: Awais Afzal

Healthcare Operations & Data Analyst, RCM Finder

Awais has spent more than 16 years in healthcare digital marketing and clinical operations management. He builds data-driven revenue cycle blueprints for high-ticket medical practices and leads product development of the RCM Finder portal. More about our team.

How we write: every figure, code and rule on this page was checked against the primary source listed below and independently fact-checked before publishing. We re-review this page every six months. Last reviewed October 12, 2026; next review April 12, 2027.

Sources

  1. 42 CFR 410.39 Prostate cancer screening tests: Conditions for and limitations on coverage — eCFR (current (accessed 2026-10-09))
  2. NCD 210.1 Prostate Cancer Screening Tests — CMS Medicare Coverage Database (Version 2, effective 06/19/2006 (accessed 2026-10-09))
  3. Prostate cancer screenings — Medicare.gov (accessed 2026-10-09)
  4. HCPCS G0102 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  5. HCPCS G0103 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  6. Medicare NCCI Policy Manual, Chapter VII: Surgery: Urinary, Male Genital, Female Genital, Maternity Care and Delivery Systems (CPT 50000-59999) — CMS (2026)
  7. Global Surgery Booklet (MLN907166) — CMS Medicare Learning Network (2025 (December))
  8. Coding Tips & Tricks: Modifier 25: Appropriate Use Explained — AUANews (American Urological Association) (2023)
  9. Coding for Urodynamic Procedures (coding fact sheet) — American Urogynecologic Society (AUGS) (2018 (last updated January 2018))
  10. Modifier 26 (JF Part B) — Noridian Healthcare Solutions (Medicare contractor) (accessed 2026-10-09)
  11. AMA releases CPT 2026 code set — American Medical Association (undated (accessed 2026-10-09); code set effective January 1, 2026)
  12. Medicare and Medicaid Programs; CY 2026 Payment Policies Under the Physician Fee Schedule (CMS-1832-F), section on prostate biopsy services — CMS via Federal Register (90 FR 49266, document 2025-19787) (2025 (published November 5, 2025))
  13. CPT 55707 code summary — AAPC (secondary; plain-language code meaning only; primary: CY 2026 PFS final rule) (accessed 2026-10-09)
  14. CPT 55708 code summary — AAPC (secondary; plain-language code meaning only; primary: CY 2026 PFS final rule) (accessed 2026-10-09)
  15. CPT 55709 code summary — AAPC (secondary; plain-language code meaning only; primary: CY 2026 PFS final rule) (accessed 2026-10-09)
  16. HCPCS G0416 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  17. CPT 52000 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  18. CPT 52332 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  19. CPT 52287 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  20. CPT 51720 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  21. CPT 96402 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  22. HCPCS J9217 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  23. HCPCS J9155 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  24. HCPCS J9030 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  25. HCPCS J0585 code summary — AAPC (secondary; plain-language code meaning only) (accessed 2026-10-09)
  26. Calendar Year (CY) 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F) fact sheet — CMS (2025)
  27. WISeR (Wasteful and Inappropriate Service Reduction) Model — CMS Innovation Center (page updated 2026-09-30)
  28. WISeR Provider and Supplier Operational Guide, Version 7.0 — CMS Innovation Center (2026 (July 24))
  29. JW Modifier and JZ Modifier Policy Frequently Asked Questions — CMS (undated (accessed 2026-10-09))
  30. Billing and Coding: Botulinum Toxin Injections (A57185) — CMS Medicare Coverage Database (Noridian, Jurisdiction J-E) (2026 (revision effective 04/09/2026))
  31. Specialty Drugs Prior Authorization Program (clinical and specialty pharmacy) — UnitedHealthcare Provider (2026)
  32. Radiology prior authorization and notification — UnitedHealthcare Provider (2026)
  33. Clinical Laboratory Improvement Amendments (CLIA) — CMS (accessed 2026-10-09)
  34. Apply for a CLIA Certificate — CMS (page last modified 2026-09-09)
  35. 42 CFR 493.2 Definitions — eCFR (current (accessed 2026-10-09))
  36. 42 CFR 493.15 Laboratories performing waived tests — eCFR (current (accessed 2026-10-09))
  37. 42 CFR 493.19 Provider-performed microscopy (PPM) procedures — eCFR (current (accessed 2026-10-09))
  38. MLN Matters MM14273: New Waived Tests — CMS Medicare Learning Network (2025 (November 14; effective January 1, 2026))
  39. CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) fact sheet — CMS (2024)
  40. AMA survey: Prior authorization reform pledge falls short with physicians — American Medical Association (2026)
  41. FFS ABN (Advance Beneficiary Notice of Non-coverage, CMS-R-131) — CMS (page last modified 2026-07-17)
  42. Healthcare and medicines policy — Google Ads Help (accessed 2026-10-09)
  43. Sexual health and wellness policy — Google Ads Help (accessed 2026-10-09)
  44. Business Associates — HHS Office for Civil Rights (2026 (content last reviewed July 30, 2026))
  45. Minimum Necessary Requirement — HHS Office for Civil Rights (undated (accessed 2026-10-09))
  46. 45 CFR 164.312 Technical safeguards — eCFR (current (accessed 2026-10-09))
  47. Use of Online Tracking Technologies by HIPAA Covered Entities and Business Associates — HHS Office for Civil Rights (2024 (reviewed June 26, 2024))