

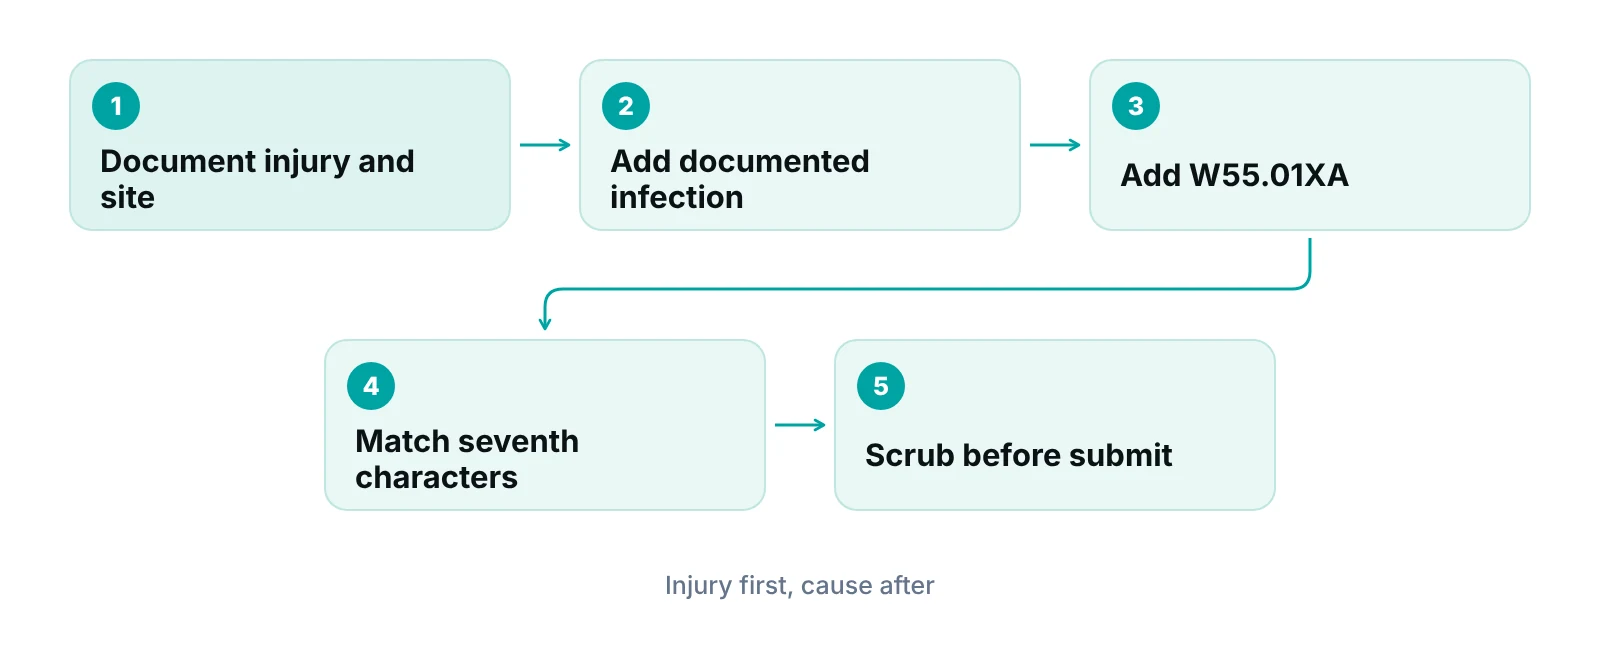
Cat bite ICD-10 coding starts with the injury the provider documents, such as S61.451A for an open bite of the right hand. Add W55.01XA (bitten by cat) as a supporting external cause code, never as the first-listed diagnosis, and report any documented infection with its own code.
“Bitten by a cat” describes how the injury happened. It does not describe the injury, and a claim needs both. Older versions of this page used the wrong external cause code in its main example, so the codes below were rechecked against current code listings and the official ICD-10-CM Guidelines for FY 2027.
This page covers cats only. For dog bites, see the dog bite ICD-10 guide; for tick removal and tick-bite billing, see the tick removal billing guide. Cat bites differ because they are often deep puncture wounds with a real infection risk, and that changes what the chart must say.
Key takeaways
- The first-listed code is the injury (for example an open bite of a body site), not the cause.
- W55.01XA is the external cause code for “bitten by cat”, initial encounter. W54 is the dog code.
- Infection is not part of the bite code. When the provider documents cellulitis or another infection, it is reported with its own code.
- The seventh character on the external cause code should follow the injury code for the same encounter.
- Most cat bite denials are documentation problems: missing site, laterality or episode of care.
What a cat bite claim needs
A cat bite claim needs the injury, the cause and, when present, the infection. Each is a separate piece of information, and each depends on what the provider wrote in the note.
The injury code comes from Chapter 19 of ICD-10-CM (the S codes). For a bite that breaks the skin on the right hand, S61.451A describes an open bite of the right hand, initial encounter. The cause comes from Chapter 20, the external cause codes. For a cat, that is W55.01XA, bitten by cat, initial encounter. Both descriptors were checked against current code listings.
External cause codes add context. The Highmark provider guidance describes them as supplementary and says they should never be sequenced as the principal or first-listed diagnosis. If the only thing on the claim is the cat code, the claim has no injury to pay for.
| Code | Descriptor | Role on the claim | When it applies |
|---|---|---|---|
| S61.451A | Open bite of right hand, initial encounter | Injury (first-listed) | Bite that breaks the skin of the right hand, active treatment |
| S61.451S | Open bite of right hand, sequela | Injury (late effect) | Only for a later effect of the bite, not for routine follow-up |
| W55.01XA | Bitten by cat, initial encounter | External cause (secondary) | Added after the injury code when the provider documents a cat bite |
| L03.011 | Cellulitis of right finger | Infection (when documented) | Provider diagnoses cellulitis at that site |
| A28.0 | Pasteurellosis | Infection (when documented) | Provider diagnoses Pasteurella infection |
| A28.1 | Cat-scratch disease | Infection (when documented) | Provider diagnoses cat-scratch disease |
Source: ICD-10-CM code listings (S61.451A, S61.451S, W55.01XA, L03.011, A28.0, A28.1), FY 2027 release; descriptors paraphrased. Hand and finger codes are examples; other body sites have their own codes.
The table shows examples. A cat bite on the left forearm, the face or the foot uses different injury codes. The coder finds the right one in the Tabular List by body site, laterality and type of wound. The pattern stays the same: injury first, cause second, infection added only when documented.
Choose the injury code from the documentation
The injury code is only as specific as the note. A provider who writes “cat bite” with no site, side or wound type leaves the coder without enough to pick a code.
Open bite codes (such as S61.451A for the right hand) exist for bites that break the skin. The chart should therefore answer four questions before a claim is built:
- Where on the body is the bite, and which side?
- Did the bite break the skin? Cat bites are often puncture wounds, and the note should say so.
- Is this the first active treatment, a follow-up, or a late effect?
- Did the provider diagnose an infection, or is the wound only at risk of one?
DC Health clinical guidance describes cat bites as penetrating and difficult to decontaminate, because a cat’s canine teeth can push bacteria deep into tissue (DC Health, undated). That is clinical background, not a coding rule. Its practical meaning for coders is that a small wound on the surface may carry a longer note than expected, and the claim should reflect what the provider documented rather than the size of the wound.
Do not code from the patient's words
A patient’s phrase such as “my cat bit me” is history. The code must come from the provider’s diagnosis. If the note names the cause but not the injury, send a documentation query before the claim goes out.
If the bite is one part of a larger visit, the other diagnoses still need their own codes. A short primer on how code sets work together is in the CPT, ICD-10 and HCPCS explainer.
External cause codes for cat bites
W55.01XA is the cat bite external cause code, and it never stands alone. It tells the payer how the injury happened. It does not replace the injury code.
The most common error is using the dog code. W54 is the dog category, and W55 is contact with other mammals, which includes cats. A search listing for W55.01XA places it under W55.0, contact with cat, within W55, contact with other mammals. Older versions of this page paired the cat bite with W54.0XXA, which is the wrong animal.
Sequencing and the seventh character
External cause codes follow the injury code on the claim. The official ICD-10-CM Guidelines for FY 2027 have a section on application of seventh characters in Chapter 19 and a separate section on general external cause coding. Read both before building a coding policy. In practice, the character on the external cause code (A for initial encounter in the codes above) should match the injury code for the same visit. A claim that shows S61.451A with a different episode on the cause code looks inconsistent and may be flagged by a claim scrubber.
Place and activity codes are optional detail
Besides the cause of injury, external cause codes can describe where it happened and what the person was doing. The Highmark provider guidance lists Y93 as the activity category. These add context but do not change the injury code. Whether a payer, state or registry asks for them is a policy question for each practice to check, not a universal rule.
“An external cause code answers "how did this happen?". It supports the injury code and should never be the reason a claim exists.”
The same logic applies to other injuries, such as slips and falls. For a worked example, see the ground-level falls coding guide.
Coding infection after a cat bite
Infection gets its own code, and only when the provider diagnoses it. The bite code does not tell the payer that the wound is infected, so an infected bite needs the injury code plus a code for the infection.
Two features of cat bites make infection a real coding topic. First, Pasteurella multocida is normal mouth bacteria in cats and dogs, and DC Health says it can cause painful wound and skin infections, usually with skin signs within 24 hours (DC Health, undated). Second, cat scratch disease can follow a bite or scratch, with a mild wound infection 3 to 14 days later, according to the same document. These are clinical facts. A coder cannot assign an infection code because a bite is likely to get infected; the provider must document it.
| What the provider documented | Injury code | Add external cause | Add infection code |
|---|---|---|---|
| Fresh bite, right hand, skin broken, no infection noted | S61.451A (example) | W55.01XA | None |
| Bite with cellulitis of the right finger | Injury code for the site | W55.01XA | L03.011 |
| Bite with Pasteurella infection diagnosed | Injury code for the site | W55.01XA | A28.0 |
| Cat-scratch disease diagnosed after a bite or scratch | Injury code if a wound is treated | W55.01XA when the cause is a bite | A28.1 |
| “Cat bite” only, no site or wound type | Query the provider | Hold | None |
Source: ICD-10-CM code listings, FY 2027 release (descriptors paraphrased). Rows are illustrative; always code from the provider’s actual documentation and the Tabular List notes.
Cellulitis codes in the L03 category are chosen by body site, so a hand or forearm infection uses a different code than a finger infection. Confirm the site-specific code and any instructional notes (such as an additional code for the organism) in the Tabular List before assigning it.
Urgent care and walk-in clinics see the majority of fresh bites, and their billing often mixes the visit, the wound care and any injections. For the broader picture, see the urgent care billing and coding guide and the urgent care billing and RCM page.
Initial visit, follow-up and late effects
The seventh character tells the payer which phase of care the visit belongs to. The A character in S61.451A and W55.01XA marks the initial encounter, meaning active treatment.
Not every visit after a bite is an initial encounter. Whether a wound check, a dressing change or an antibiotic recheck counts as active treatment depends on what the provider is doing at the visit, so the coder should follow the guideline definitions rather than the calendar. The sequela code S61.451S exists for a late effect of the bite, which is a different situation from a routine recheck.
| Visit | What the note should show | Common error |
|---|---|---|
| First visit | Site, side, wound type, cause, any signs of infection | Cause documented, injury missing |
| Recheck for infection | Whether infection is now diagnosed; who treated and why | Infection coded without a provider diagnosis |
| Later effect | Link between the current problem and the earlier bite | Using the sequela character for a routine recheck |
| Outside referral | Same cause and site as the original visit | Different codes at the two practices for one bite |
Source: ICD-10-CM Official Guidelines for Coding and Reporting, FY 2027 (structure: seventh characters in Chapter 19; external cause coding). Rows are practice checks, not quoted rules.
Rabies and tetanus: what is clinical and what is billing
Rabies and tetanus decisions are clinical, and the coder works from what the provider documents. They matter on a bite visit because they drive extra services that need their own documentation.
According to DC Health, the rabies status of a domestic cat cannot be confirmed by testing while the animal is alive, so the cat is observed for 10 days or tested. It also advises tetanus vaccination for anyone bitten who has not had a booster in the past five years (DC Health, undated). Treat this as one jurisdiction’s clinical guidance. Providers should follow current CDC, state and local health department advice.
For billing, the practical questions are narrow. Did the provider document an exposure assessment? Was a vaccine or immune globulin given, and what were the product, dose and route? Is the visit reportable to the local health department? The coder should not assign codes for services or exposure status that the note does not support.
Vaccine and immune globulin products have their own procedure codes and diagnosis pairing rules that vary by payer. A short list of rules to check is better than memory:
- Payer policy for the product and administration codes used.
- Whether the diagnosis on the claim supports medical necessity for the service.
- Any state reporting duty for animal bites (rules vary by state).
- Wound care procedures performed the same day, such as irrigation or repair, and their documentation.
For the procedure side of wound care, the CPT coding wound care guide covers how procedures are described and documented.
Why cat bite claims get denied or delayed
Most denials on bite claims trace back to documentation gaps that were visible before submission. Catching them requires a short pre-bill check, not more coding knowledge.
- Only the external cause code is on the claim, with no injury code.
- Dog code W54 used for a cat bite, or the reverse.
- Missing laterality or body site, so the injury code is unspecified or wrong.
- Infection code reported without a provider diagnosis, or infection documented but not coded.
- Seventh characters that do not match between the injury and the cause.
- Different codes for one bite across the referring and treating practice.
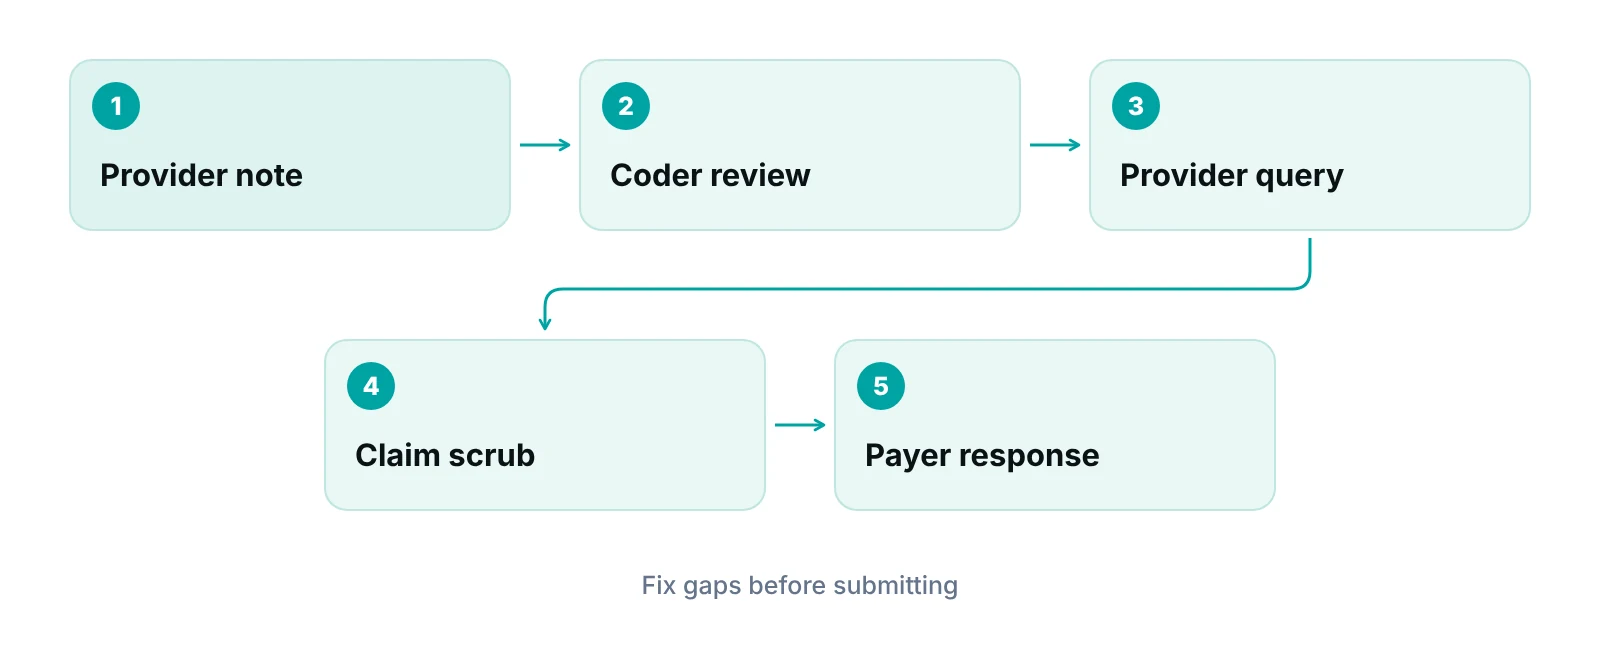
A claim scrubber can catch the structural errors (missing injury code, mismatched characters), but it cannot read the note. That is a coder’s or provider’s job. The claim scrubbing guide explains what automated checks do and do not cover.
When a bite claim does come back denied, the fix is usually an appeal or a corrected claim based on the note. The denial management services page describes how that work is handled. Practices that want to review their own bite and injury claims can start with a coding audit; the medical coding audit guide lists the common types.
Want a second look at your injury and bite claims?
A free practice audit reviews how your documentation turns into codes and where claims stall before payment.
A simple workflow for front desk, coders and providers
A short checklist keeps the bite visit consistent from the exam room to the claim. The checklist is useful because the information a coder needs is usually known to the provider at the time of the visit.
- Provider documents site, side, wound type (for example puncture), the animal (cat) and whether skin was broken.
- Provider states any infection diagnosis in words, not only in a prescription.
- Provider records the episode of care: first visit, follow-up for the same problem, or a later effect.
- Coder picks the injury code first, then the infection code if documented, then W55.01XA.
- Coder checks that the seventh characters agree and that there is no dog code on a cat bite.
- Billing runs the claim through a scrubber and sends queries back to the provider for anything missing.
Practices that outsource coding can ask the vendor to show this sequence in their process. The medical billing services page describes what RCM Finder’s billing and coding support covers, and the revenue calculator gives a rough view of how much unpaid claim value a practice might be carrying.
Our recommendations
- Put the injury before the cause in templates. Build the visit template so the provider enters site, side and wound type before the cause field. The cause is easy to remember and the injury detail is what gets skipped.
- Add a cat vs dog check to the scrub. A simple rule that flags W54 on a note containing the word “cat” (or the reverse) removes the most common mix-up. Treat the flag as a review prompt, not an automatic fix.
- Ask for infection language in words. Ask providers to write “cellulitis” or “Pasteurella infection” when they diagnose it. A prescription alone is not a diagnosis a coder can use.
- Keep the clinical pathway separate from the coding rules. Rabies and tetanus decisions follow current CDC and local health department guidance. The billing team should check the documentation for those services, not rewrite the clinical logic.
- Review code sets every October. ICD-10-CM changes on October 1 each year. Check the codes in your templates and encoders against the new release, and update any internal cheat sheets.
- Audit a sample of injury claims. Pull 20 to 30 closed bite and injury claims, compare the note to the codes, and record the reasons for any mismatch. Fix the cause, whether template, training or scrub rules.
Bottom line
For a cat bite, code the documented injury first, add W55.01XA as the supporting cause, and report infection separately when the provider diagnoses it. If your claims are stalling on documentation gaps, see our revenue cycle management and denial management services, or start with a free practice audit.
Frequently asked questions
What is the ICD-10 code for a cat bite?
There is no single code. The injury code depends on the body site and wound type, for example S61.451A for an open bite of the right hand. The external cause code W55.01XA (bitten by cat, initial encounter) is added after it. Infection, if documented, gets a separate code.
Can W55.01XA be the primary diagnosis?
No. External cause codes are supplementary, and payer guidance says they should not be sequenced as the principal or first-listed diagnosis. List the injury (or the condition being treated) first and add the cause after it.
What is the difference between W54 and W55 for animal bites?
W54 is for dog bites and W55 is contact with other mammals, which includes cats (W55.01XA is bitten by cat, initial encounter). Using the dog code for a cat bite is a common error, including in older versions of this page.
How do I code an infected cat bite?
Code the injury, add W55.01XA, and add a code for the infection the provider documented, such as cellulitis (L03 category, chosen by site) or Pasteurellosis (A28.0). Do not assign an infection code only because a bite is at risk of infection.
Do I need an external cause code on every claim?
Not always. Whether one is required depends on the payer, the state and the practice’s own policy, so check each. Where reported, the seventh character should match the injury code for the same encounter.
When do I use the seventh character S for a cat bite?
S marks a sequela, a late effect of the bite, such as S61.451S for the right hand. A routine follow-up for the same wound is not automatically a sequela. Follow the official guideline definitions and ask the provider when the note is unclear.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- ICD-10-CM Official Guidelines for Coding and Reporting FY 2027 — CDC / NCHS (2026)
- Coding Corner: Understanding External Cause Codes — Highmark (n.d.)
- Animal Bites: Clinical and Public Health Considerations — DC Health (n.d.)
- W55.01XA Bitten by cat, initial encounter — Find-A-Code (2026)
- S61.451A Open bite of right hand — Unbound Medicine (ICD-10-CM) (2024)
- L03.011 Cellulitis of right finger — Unbound Medicine (ICD-10-CM) (2024)
- ICD-Code A28.0: Pasteurellosis — gesund.bund.de (n.d.)
- A28.1 Cat-scratch disease — icd-10codes.com (2027)
Disclaimer: This article is educational and is not legal, coding, clinical or compliance advice. Code sets, guidelines and payer rules change and vary by payer and state. Confirm every code in the current ICD-10-CM Tabular List and with the payer before billing.
