
Gynecology CPT codes fall into four working groups: office E/M visits (99202-99215), preventive and screening services, in-office procedures such as IUD placement and hysteroscopy, and surgery. The code is only half the claim. Bundling edits, modifiers and global periods decide how those codes pay together.
This guide groups gynecology CPT codes the way a claim is actually built, so a biller or practice manager can see where each service sits and which rule applies. It replaces an older version of this article that mislabeled some codes. Every rule below was checked against a CMS or Medicare contractor page, and the places where you must still check the current CPT codebook are marked. For a wider view of how codes work across specialties, see our guide to CPT codes in medical billing.
Key takeaways
- Group gynecology services by claim type: E/M visit, preventive or screening, procedure, surgery.
- Office E/M levels are chosen by medical decision making or total time, not by history and exam.
- CMS bundling edits mean diagnostic hysteroscopy, diagnostic laparoscopy and pelvic exams are often not billable on top of the main procedure.
- Modifier 25, 57 and 58 each answer a different timing question; the global period (0, 10 or 90 days) decides which one applies.
- CPT descriptors belong to the AMA; confirm every code in the current codebook before it goes on a charge master.
How gynecology CPT codes are grouped
Gynecology claims fall into four groups, and each group follows its own rules. Sorting a service into the right group first prevents most of the wrong-code and wrong-modifier problems that follow.
The table lists examples we could verify from a fetched source. It is a starting map, not a full code set. Imaging and laboratory codes sit in their own CPT sections, so use the radiology CPT codes guide for pelvic imaging and look up pathology and lab codes in your current codebook.
| Group | Codes you will meet | What to check before billing |
|---|---|---|
| Office visits (E/M) | 99202-99215 (new and established patient, office or outpatient) | Level is set by medical decision making or total time on the date of the encounter |
| Preventive and screening | Age-banded preventive medicine visit codes (private payers); P3000, P3001, Q0091 and G0123-G0148 family for Medicare screening Pap services | Medicare and commercial payers handle screening differently; read the payer policy |
| In-office procedures | 58300 family (IUD introduction procedures); 58555 (diagnostic hysteroscopy); 57420, 57452 and 56820 (diagnostic colposcopy) | Diagnostic hysteroscopy and colposcopy are often bundled into the definitive procedure |
| Surgery | 58140 (myomectomy), 58150 (total abdominal hysterectomy), 58570 (laparoscopic total hysterectomy, uterus 250 g or less), 58605 (tubal ligation), 58940 (oophorectomy), 58956 (bilateral salpingo-oophorectomy with omentectomy and total abdominal hysterectomy for malignancy) | Global period, laparoscopic versus open approach, and approach-specific NCCI edits |
| Imaging and lab | Reported from the radiology, pathology and laboratory sections of CPT | Look up each code in the current CPT codebook; see our radiology CPT guide |
Source: CMS NCCI Policy Manual Chapter 7 (2026); Noridian Medicare (screening Pap tests); MGMA (2021 E/M changes); code lookup at findacode.com and codingahead.com. CPT descriptors are AMA property; summaries are in our own words.
Corrections to common code lists
Code lists copied between websites often carry errors. In the lookup sources we checked, 58940 is oophorectomy, partial or total, unilateral or bilateral. 58956 is a bilateral salpingo-oophorectomy with total omentectomy and total abdominal hysterectomy for malignancy, not removal of one ovary. 58605 is a tubal ligation code, not removal of ovarian lesions. Diagnostic imaging and hysteroscopy are not laboratory or pharmaceutical codes.
Office visits: E/M codes 99202-99215
Office and outpatient visits are billed with 99202-99215, and since 2021 the level is chosen by medical decision making (MDM) or by total time on the date of the encounter. Either method may be used, so long as the record supports it.
According to MGMA‘s summary of the 2021 changes, the revised rules apply only to office and outpatient E/M codes. Medically appropriate history and exam are still documented but no longer set the level. Code 99201 was deleted, and 99211 has no MDM requirement.
What this means for a gynecology visit
- MDM needs two of three elements: problems addressed, data reviewed and analyzed, and risk of patient management.
- Time counts the provider’s own face-to-face and non-face-to-face work on the date of service, and the total must be documented if time is used.
- A routine problem visit and a preventive visit are different services. Do not bill a problem E/M as a substitute for a screening visit, or the reverse.
When a significant, separately identifiable E/M service happens on the same day as a procedure, modifier 25 is the signal. Our modifier 25 versus 59 guide covers the difference in detail.
Preventive and screening services
Medicare screening uses HCPCS codes, not the age-banded preventive visit codes used by many commercial plans. If your patient mix includes Medicare, build two separate charge paths for screening.
A Medicare administrative contractor, Noridian, lists the screening codes, frequency and diagnosis codes in the table below. The page also says the Pap test and the pelvic exam can be performed during the same encounter.
| Item | Detail |
|---|---|
| Who is eligible | All female Medicare beneficiaries; ordered by a physician, CNM, PA, NP or CNS |
| Frequency | Every two years at normal risk; annually if at high risk for cervical or vaginal cancer |
| Collection and handling | Q0091: screening Pap smear, obtaining, preparing and conveying the specimen to the lab |
| Lab interpretation | P3000 (technician under physician supervision), P3001 (requires physician interpretation), G0123, G0124, G0141, G0143-G0145, G0147, G0148 |
| Diagnosis codes (normal risk) | Z01.411, Z01.419, Z12.4, Z12.72, Z12.79, Z12.89 |
| Diagnosis codes (high risk) | Z72.51-Z72.53, Z77.21, Z77.22, Z77.9, Z91.89, Z92.89 |
| Patient cost | Deductible and coinsurance waived |
Source: Noridian Healthcare Solutions, Medicare Part B, Screening Pap Tests (JE Part B page, accessed 2026). Frequency and coverage details vary by contractor and change over time; confirm in your MAC’s current policy.
Commercial payers publish their own preventive visit policies, including which age-banded preventive medicine code to use and whether a separate problem-oriented visit is payable the same day. Those rules differ by payer and by plan, so treat the payer’s policy as the source of truth. We have not listed the preventive visit code ranges here because we could not verify the current descriptors from a primary source; pull them from your CPT codebook.
Procedures and surgery: what NCCI bundles together
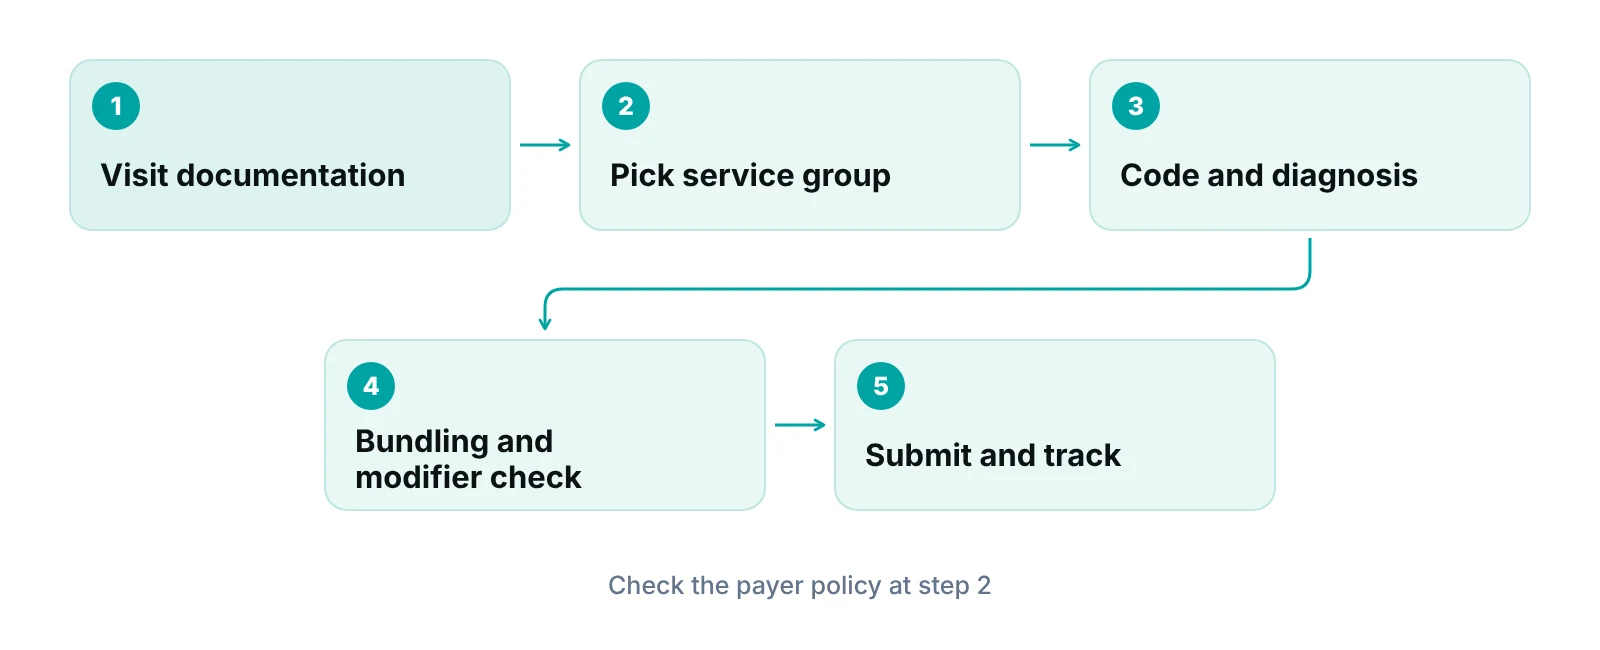
Procedure and surgery codes in the 50000-59999 range are governed by CMS National Correct Coding Initiative (NCCI) edits that bundle many related services. A code may exist, and the physician may have performed it, and still not be separately payable.
The CMS NCCI Policy Manual, Chapter 7 (2026) covers urinary, male genital, female genital, maternity and delivery surgery. The rules below come from its female genital system sections.
Bundling rules that affect gynecology claims
- Surgical laparoscopic, hysteroscopic or peritoneoscopic procedures include diagnostic procedures. Diagnostic hysteroscopy (58555) is included in 58558-58565.
- Surgical laparoscopy includes diagnostic laparoscopy. If a diagnostic laparoscopy leads to an open procedure, it may be separately reportable with modifier 58.
- Colposcopy is not separately reported when it is done to confirm a lesion or to assess the surgical field. A diagnostic colposcopy that leads to a non-colposcopic procedure may be reported, with modifier 58 on the non-colposcopic procedure.
- A pelvic exam that is part of a gynecologic procedure is not separately reportable, and pelvic examination under anesthesia (57410) is included in all major and most minor gynecological procedures.
- Laparoscopic lysis of adhesions (58660) is not separately reportable with other surgical laparoscopic procedures.
- A vaginal hysterectomy normally includes fixation of the vagina. Reporting colpopexy codes 57282 or 57283 for that routine fixation is a misuse of those codes.
- Radiofrequency ablation of uterine fibroids and myomectomy codes (58140-58146) are not both reported for the same leiomyoma.
- When a code already includes imaging guidance, ultrasound or other radiologic guidance is not separately reported.
These edits change how you read a surgeon’s note. A note that says “diagnostic hysteroscopy, then polypectomy” usually produces one billable service, not two. Teach charge-entry staff to ask what the final procedure was before they add the exploratory step.
“A correct code with the wrong approach, the wrong modifier or an unbundled step is still a denied claim. Coding review should happen before the claim leaves the building, not after the denial arrives.”
For group practices that perform many procedures, a periodic internal review catches these patterns early. Our overview of medical coding audits explains the main types.
Modifiers and global periods
Modifiers tell the payer why a second service is payable. The global period tells you how long related care is included in the surgery payment. Learn both together, because one decides which of the other you need.
The CMS global surgery booklet explains that a global package includes pre-operative visits, intra-operative services and routine post-operative care. For 10-day codes, the total global period is 11 days. For 90-day codes, it is 92 days, counting one day before surgery, the day of surgery and the 90 days after.
| Item | What it means (CMS) | Typical gynecology situation |
|---|---|---|
| Modifier 25 | Significant, separately identifiable E/M by the same provider on the day of a procedure | Problem visit and an in-office procedure on the same day |
| Modifier 57 | E/M visit that results in the first decision to do surgery; major surgery only | Visit where hysterectomy or myomectomy is decided |
| Modifier 58 | Used by NCCI when a diagnostic colposcopy or laparoscopy leads to a different procedure | Diagnostic laparoscopy that leads to an open procedure |
| Modifier 24 | Unrelated E/M by the same provider during a post-operative period | New problem during the 90-day period after a hysterectomy |
| Modifier 79 | Unrelated procedure by the same provider during a post-operative period | Unrelated procedure during a global period |
| Modifier 50 | Reported when a procedure is not identified as bilateral, as a single line item | Bilateral procedure whose descriptor does not say bilateral |
| Global periods | 000 (0-day), 010 (10-day), 090 (90-day); 010 totals 11 days, 090 totals 92 days | Major gynecologic surgery is typically 090; check each code’s indicator |
Source: CMS MLN Global Surgery booklet (MLN907166); CMS NCCI Policy Manual Chapter 7 (2026). Modifier 58’s formal CPT definition is the AMA’s; the NCCI usage above is as described in the manual.
Modifiers 22, 51 and 59
Modifier 22 (increased procedural services), modifier 51 (multiple procedures) and modifier 59 (distinct procedural service) are in common use in gynecology. We did not verify their current definitions from a primary source for this update, so confirm them in the CPT codebook and the payer’s policy. Modifier 59 and its X-modifiers are discussed in our modifier 25 versus 59 comparison. The NCCI manual refers to an NCCI procedure-to-procedure (PTP) associated modifier, which is the category those modifiers fall into.
A coding review checklist for OB-GYN claims
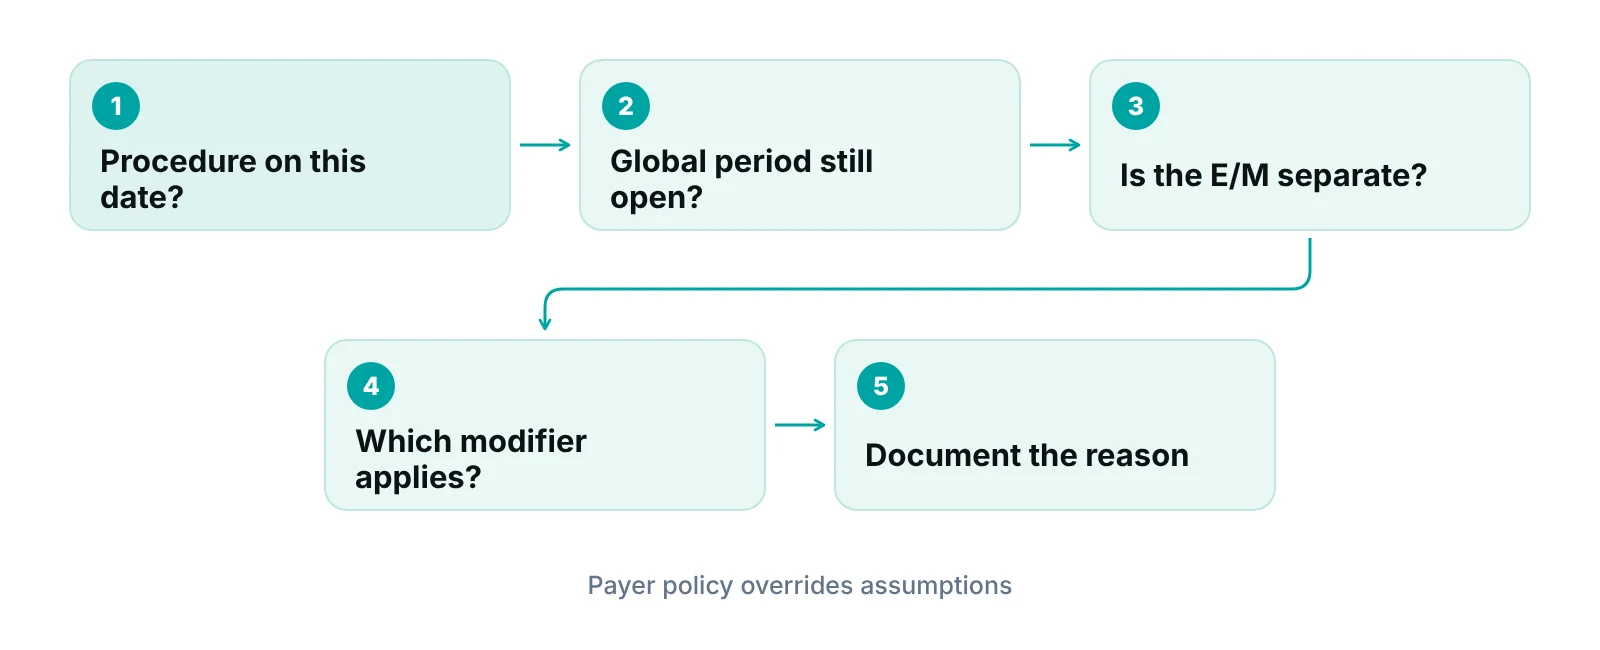
A coding review checks four things on each charge: the service group, the code, the modifier and the documentation. Most corrections come from the last three.
- Match the code to the operative or procedure note, not to the scheduling description.
- Confirm the approach (open, laparoscopic, hysteroscopic, vaginal) because many gynecology codes are approach-specific.
- Check NCCI bundling before adding exploratory or diagnostic steps.
- Confirm the global period before billing a visit within 10 or 90 days of a procedure.
- Match diagnosis codes to the service. Screening and problem visits use different diagnosis sets.
- Store the payer’s policy for each plan that pays differently from Medicare.
Tools help with the repetition. A practice management system that checks claim data for completeness before submission and tracks each claim by stage, such as a practice management system that tracks claims by stage, can catch missing information. It does not decide whether a code is correct; that remains a coder’s job. For the technology side of this specialty, read technology for efficient OB-GYN billing.
Clean submission also depends on basics such as demographics and payer data. See our guide to clean claims in medical billing for that checklist.
Deciding who handles gynecology coding
Practices usually choose between three setups: keep coding in-house, outsource billing and coding, or split the work. The right one depends on how many procedures the practice performs and whether anyone owns coding updates and denials.
- In-house works when a credentialed coder is on staff, reviews updates every year and has time to work denials.
- Outsourcing fits when coding knowledge is thin, volume is uneven, or denials are piling up with no owner.
- A hybrid keeps charge entry in-house and sends coding review, claim follow-up or denials to a partner.
If you are weighing outsourcing, our OB-GYN billing outsourcing checklist lists what to ask a vendor, including a Business Associate Agreement, access controls and reporting. You can also read about our OB-GYN billing and revenue cycle support and our medical billing services.
Want a second set of eyes on your OB-GYN claims?
Request a free practice audit and we will review how your gynecology charges, modifiers and denials are handled today.
Our recommendations
- Group before you code. Sort each service into visit, preventive, procedure or surgery first. The group decides which payer rule applies.
- Verify every code in the current CPT codebook. CPT is updated by the AMA and descriptors are AMA property. Re-check your charge master against the current edition each year.
- Build NCCI checks into charge entry. Teach staff to bill the final procedure, not the diagnostic step that led to it, unless the NCCI manual allows both.
- Track global periods per procedure. Record the global indicator for each surgical code so a visit inside a 10- or 90-day period is flagged before billing.
- Keep a payer policy file. Store the preventive visit and screening policy for each major commercial plan alongside Medicare’s.
- Review denials by cause. Sort denials into bundling, modifier, global period and documentation, then fix the upstream step. See our denial management services for how that work is organized.
A practice management system can flag incomplete gynecology claims before they are submitted.
RCM Finder's portal tracks claims by stage with an owner and runs data-completeness checks before submission. It supports a coder's review; it does not replace code selection.
See how the RCM Finder portal works · Create a portal account
Disclosure: RCM Finder builds and sells this portal. It is a practice management system, not an EHR.
Bottom line
Gynecology CPT codes are easiest to manage when you group services by claim type, respect NCCI bundling, and decide modifiers by global period. Use the current CPT codebook to confirm every descriptor. If your claims keep coming back, request a free practice audit, or read about our denial management services and OB-GYN billing support. You can also estimate the cost of unpaid claims with our revenue calculator.
Frequently asked questions
What are gynecology CPT codes?
Gynecology CPT codes are the AMA-maintained numeric codes used to report visits, screening, procedures and surgery for female reproductive care. Practices group them into office E/M, preventive and screening, in-office procedures and surgery, then add modifiers and diagnosis codes. Each claim also needs a matching diagnosis code, and the payer’s policy decides what is payable.
Which E/M codes do gynecology offices use?
Office and outpatient visits use 99202-99215. Since 2021 the level is chosen by medical decision making or total time on the date of the encounter, not by history and exam. Preventive visits use separate preventive medicine codes selected by patient age.
Does Medicare use the same codes for a screening Pap?
No. Medicare screening Pap services use HCPCS codes such as Q0091, P3000 and P3001 and the G0123-G0148 family, rather than the commercial preventive visit codes. A Medicare contractor lists coverage as every two years at normal risk and annually at high risk.
When can diagnostic hysteroscopy or laparoscopy be billed separately?
Usually not, when it leads to a surgical hysteroscopy or laparoscopy; CMS NCCI says surgical procedures include the diagnostic step. A diagnostic laparoscopy that leads to an open procedure may be reportable with modifier 58. Edits are updated over time, so check the current NCCI tables and the payer’s policy before billing a diagnostic step on its own.
What is a global surgery period?
It is the time during which related pre- and post-operative care is included in the surgery payment. CMS lists 0-day (000), 10-day (010) and 90-day (090) periods. A 10-day period totals 11 days and a 90-day period totals 92 days.
Where can I confirm the current code descriptors?
Use the current AMA CPT codebook or a licensed CPT product, plus your payer’s policy and the CMS NCCI edit tables. Descriptors change with each annual release, so a code list from a blog or website, including this one, should never replace the codebook. This article describes codes in plain words and is not a substitute for the codebook.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- NCCI Policy Manual for Medicare Services, Chapter 7 (2026) — CMS (2026)
- Global Surgery booklet (MLN907166) — CMS Medicare Learning Network (2026)
- Preparing your practice for 2021 E/M changes — MGMA (2021)
- Screening Pap Tests (JE Part B) — Noridian Healthcare Solutions (Medicare contractor) (2026)
- CPT procedure codes, 58 group — findacode.com (secondary lookup) (2026)
- CPT code 58940 and 58956 pages — codingahead.com (secondary lookup) (2026)
Disclaimer: This article is educational and is not legal, coding or compliance advice. CPT codes and descriptors are owned by the American Medical Association, and payer rules vary by plan and change over time. Confirm every code, modifier and edit in the current CPT codebook and your payer's policy before billing.
