
Inpatient coding vs outpatient coding comes down to code sets and payment. For Medicare acute-care stays, procedures are reported with ICD-10-PCS and paid by MS-DRG per discharge. Hospital outpatient services are reported with CPT and HCPCS codes and paid by APC under OPPS. The physician's inpatient order decides which path a stay takes.
Many coding questions start with a status question: was this patient an inpatient or an outpatient? The answer changes the diagnosis rules, the procedure code set, the claim and the payment method. A wrong status or a wrong code set can send a claim down the wrong path before anyone reads the clinical note. This guide is for practice managers, billers and new coders. It covers the five differences that matter most, and it links to deeper guides on hospital versus professional billing, the difference between billing and coding and CPT, ICD-10 and HCPCS codes.
Key takeaways
- Inpatient status requires a formal admission order; time spent in a bed does not create it.
- For Medicare acute-care stays, ICD-10-PCS procedure codes and diagnoses feed the MS-DRG grouper; hospital outpatient services are paid by APC under OPPS.
- The two-midnight benchmark is a Medicare Part A payment rule based on the admitting physician’s documented expectation.
- Facility coding and professional coding are separate claims for the same visit, and they should tell the same clinical story.
- Inpatient claims name a principal diagnosis; outpatient claims name a first-listed condition.
The core difference: status, code sets and payment
The short version is that inpatient and outpatient coding answer the same question, what happened to this patient, but they report it to different payment systems. The table below shows the main points for a Medicare hospital setting. Other payers can use their own rules, so check each contract.
| Question | Inpatient | Hospital outpatient |
|---|---|---|
| How is status set? | Formal admission under an inpatient order by a qualified practitioner | No inpatient order; care is billed as outpatient services, including observation |
| Diagnosis rule | Principal diagnosis, plus secondary diagnoses | First-listed condition (Section IV of the ICD-10-CM guidelines) |
| Procedure code set | ICD-10-PCS | CPT and HCPCS |
| Grouping and pricing | MS-DRG, assigned per discharge | APC, with a status indicator on each HCPCS code |
| What drives the rate | Principal diagnosis, secondary diagnoses (MCC, CC) and procedures | The separately paid code on each line, or packaging into another service |
Source: CMS two-midnight standards (42 CFR 412.3); CMS MLN Acute Care Hospital IPPS booklet (2020); CMS Transmittal 13562 (2025); CMS Claims Processing Manual Ch. 4; ICD-10-CM Official Guidelines FY 2027.
Every row follows from the first one. Once a patient is an inpatient, the stay is coded as one case and priced as one case. Outpatient care is coded and priced service by service. The sections below take each row in turn.
Who decides inpatient status: the order and the two-midnight benchmark
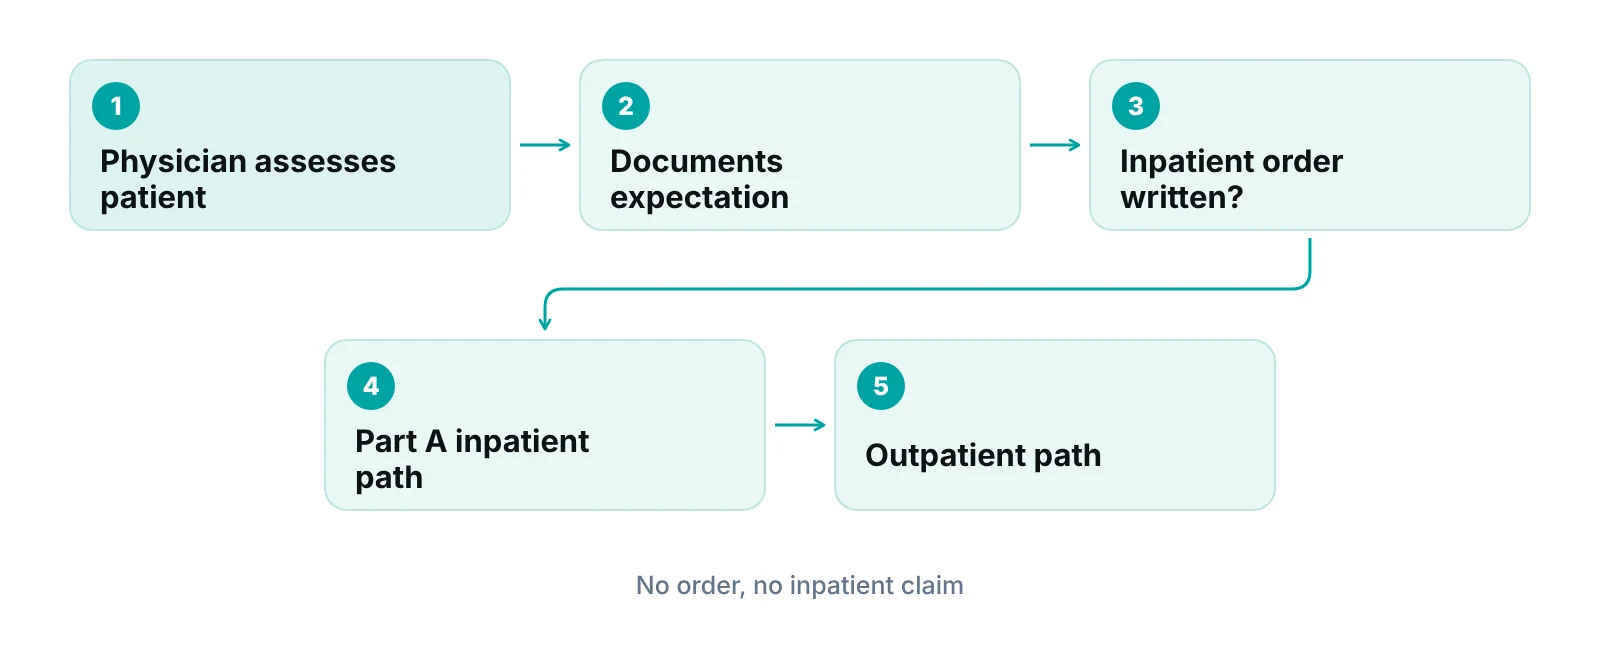
Inpatient status comes from an order, not from a patient occupying a bed. Under 42 CFR 412.3(a), as described in CMS two-midnight standards, a person is an inpatient when formally admitted under an order for inpatient admission by a qualified practitioner with admitting privileges. The order must be in the medical record, supported by the admission and progress notes, and furnished at or before admission.
What the two-midnight benchmark says
For Medicare Part A payment, an inpatient admission is generally appropriate when the admitting physician expects the patient to need hospital care that crosses two midnights. That expectation has to rest on complex medical factors recorded in the chart, such as history, comorbidities, severity of signs and symptoms, current medical needs and risk of an adverse event. CMS gives the source as 42 CFR 412.3(d)(1), in effect for admissions on or after October 1, 2013 and amended in the CY 2016 OPPS/ASC final rule.
Two exceptions matter to coders. A procedure on the Inpatient Only list is generally appropriate for Part A payment regardless of expected duration (412.3(d)(2)). And a stay expected to be shorter than two midnights may still qualify for inpatient payment case by case, based on the physician’s judgment and record support. CMS says such cases are subject to medical review.
Where observation fits
Observation is an outpatient service. The CMS material notes that the admission decision typically comes within 24 to 48 hours of observation care, and that observation beyond 48 hours should be rare. The ICD-10-CM guidelines also contain a specific rule for admission from an observation unit. For the full status walk-through, read our post on inpatient vs observation and the two-midnight rule.
“A coder can only code the status the order created. If the order and the stay disagree, resolve it before the claim is built.”
Code sets: ICD-10-CM, ICD-10-PCS, CPT and HCPCS
Diagnoses use ICD-10-CM in both settings. Procedures are where the paths split. For Medicare inpatient discharges, the MS-DRG grouper assigns each case from the reported diagnosis and procedure codes and demographic information, and the procedure codes it reads are ICD-10-PCS codes. CMS’s April 2026 grouper update (Version 43.1) added 80 new ICD-10-PCS procedure codes, each with its MS-DRG assignment.
Hospital outpatient services under OPPS are reported with HCPCS codes, which include the CPT codes hospitals use for procedures such as cardiac device implants. CMS’s Claims Processing Manual Chapter 4 tells hospitals to report codes consistently with CPT or CMS instructions and correct coding principles. If you need a refresher on how these code sets differ, see our explainer on CPT, ICD-10 and HCPCS codes.
Principal diagnosis vs first-listed condition
The terms differ because the guidelines differ. The ICD-10-CM Official Guidelines for FY 2027 put selection of the principal diagnosis in Section II, which applies to non-outpatient settings, and selection of the first-listed condition in Section IV, which is for outpatient coding and reporting. Sequencing and uncertain-diagnosis rules are written separately for each setting, so the same documentation can be coded differently depending on status. The older claim that outpatient diagnoses are simply ‘not established’ is not how the guidelines frame it.
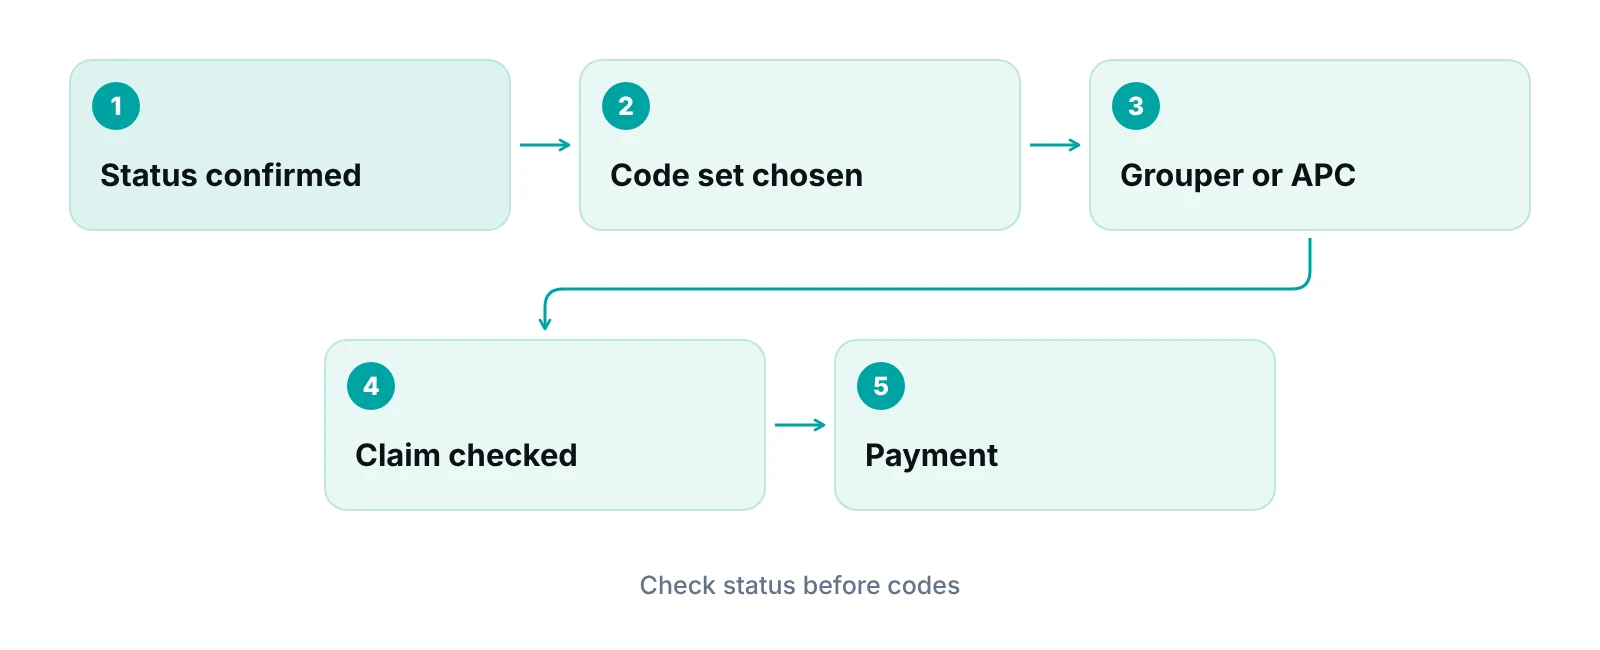
Code the status first
Confirm inpatient or outpatient status before choosing a code set. Applying ICD-10-PCS to an outpatient service, or CPT to an inpatient procedure on a facility claim, is a status error disguised as a coding error.
Payment: MS-DRG vs APC
Medicare pays acute-care hospitals for inpatient stays under the inpatient prospective payment system (IPPS) per discharge. The CMS MLN booklet on IPPS (March 2020) describes a base rate adjusted by a wage index and multiplied by a DRG weighting factor, with add-ons for teaching, low-income patient care, new technology and high-cost outliers. MS-DRGs group similar cases and split them into three severity levels: MCC, CC and non-CC, based on secondary diagnoses.
Hospital outpatient services are paid differently. The Claims Processing Manual says each separately paid OPPS code is assigned to an ambulatory payment classification (APC) group, and the APC’s payment rate and coinsurance apply to services in it. An OPPS status indicator is assigned to every HCPCS code, showing whether the service is paid separately or packaged. Packaged items get no separate APC payment, as the CMS status indicator addendum shows for indicator N.
| Feature | MS-DRG (inpatient, IPPS) | APC (hospital outpatient, OPPS) |
|---|---|---|
| Unit of payment | The whole inpatient case (per discharge) | Each separately paid service code |
| Grouping input | Principal diagnosis, up to 24 secondary diagnoses, up to 25 procedures, plus age, sex and discharge status | The CPT or HCPCS code reported on the line |
| Severity | MCC, CC or non-CC level from secondary diagnoses | Not severity-tiered; the APC sets the payment and coinsurance for the services in it |
| Bundling | Diagnoses and procedures roll into one DRG | Status indicators show whether a code is paid separately or packaged |
| Coder focus | Capture every reportable secondary diagnosis and procedure | Report each service correctly, because the code decides the line |
Source: CMS MLN Acute Care Hospital IPPS booklet (March 2020); CMS Claims Processing Manual Ch. 4, sections 10.1 to 10.2; CMS OPPS Addendum D1. Counts of diagnoses and procedures are from the 2020 booklet; confirm the current limits in the grouper.
The practical point for coders is that detail earns different things in each system. On an inpatient case, a missed secondary diagnosis can change the severity level. On an outpatient claim, a wrong or missing code changes the line. Neither system rewards guessing, and both reward complete documentation.
Facility vs professional coding
A single patient visit can produce two claims: one from the facility and one from the clinician. Facility coding reports the hospital’s services and resources. Professional coding reports what the clinician personally did. For a deeper comparison of claim types and forms, see our guide to hospital vs professional billing and institutional vs professional billing claims.
| Point | Facility (hospital) coding | Professional (clinician) coding |
|---|---|---|
| What is being reported | The hospital’s resources and services for the stay or visit | The clinician’s own work, such as an evaluation or procedure |
| Typical code sets | ICD-10-PCS and MS-DRG for inpatient stays; HCPCS/CPT and APC for outpatient | CPT and HCPCS with ICD-10-CM diagnoses |
| Who usually codes | Hospital coding or HIM staff from the full record | Practice coders or billers from the clinician’s notes |
| Main risk | Wrong status or missed secondary diagnoses | Procedure codes that do not match the note |
| Alignment check | Diagnoses and procedures should agree with the professional claim for the same encounter | Same encounter, same clinical story, different claim |
Source: CMS Transmittal 13562 and Claims Processing Manual Ch. 4 for facility code sets. Professional-claim rows are general definitions; see our hospital vs professional billing guide.
Because the same clinical note can feed both claims, a mismatch between the facility diagnosis and the professional diagnosis is an easy way to trigger a payer question. If you are unsure where coding ends and billing begins, the billing vs coding guide draws the line.
Whoever codes the facility side, a practice is responsible for its own professional claim being right. Medical billing services can take on claim preparation, but status and documentation start in the chart. Your specialty also changes which procedures appear most often, so build your coding checks around the services you actually perform.
Documentation: what each setting needs from the chart
Older versions of this article said inpatient coding needs ‘comprehensive’ documentation and outpatient coding needs ‘less’. That is too loose to be useful. Both settings need documentation that supports every code reported. What differs is what the record must show.
- Inpatient: a dated inpatient order, the admission note with the physician’s expectation, progress notes that support continued stay, a clearly stated principal diagnosis, and every reportable secondary diagnosis and procedure.
- Outpatient: the reason for the encounter, the service performed, the first-listed condition, and the support for each CPT or HCPCS code reported.
- Observation to inpatient: the time and date of the order, since the order marks the start of the inpatient stay.
- Query trail: any clarification a coder asked for and the answer, filed in the record.
Coding audits help here because they test documentation against codes. See medical coding audit types and benefits for how to set one up, and the clean claims guide for the checks that should happen before submission.
See where status and coding errors enter your claims
A free practice audit reviews your coding, documentation and denial patterns and shows where claims lose time. Pricing for any service is quoted after the audit.
Common mistakes to watch for
These are patterns to check in your own claims, not statistics. They come from the rules above.
- Billing an inpatient claim without a valid inpatient order in the record.
- Treating a long observation stay as an inpatient stay without a documented admission order.
- Using one code set for both settings, such as reporting CPT procedure codes on a Medicare inpatient facility claim where ICD-10-PCS applies.
- Missing secondary diagnoses that would change the MS-DRG severity level.
- Using the principal diagnosis rules on an outpatient claim, or the first-listed condition rules on an inpatient one.
- Letting the facility and professional claims describe the same visit in different ways.
- Coding from an old code set after an update. CMS issues grouper updates during the year, such as the April 2026 release.
Upcoding and downcoding risks also differ by setting. If your team is unsure where the line is, our posts on upcoding in medical billing and down-coding explain what payers look for.
Our recommendations
- Verify status before coding. We recommend a standing check that an inpatient order exists, is dated, and is supported by the admission note before an inpatient case is coded.
- Document the expectation, not just the stay. We recommend that admitting physicians record why they expect care to cross two midnights, using the factors CMS lists, so the note supports the order.
- Route observation stays through a second look. We recommend flagging every observation stay that converts to inpatient so a coder confirms the order time and the guideline for admission from observation.
- Keep facility and professional claims in step. We recommend comparing diagnoses on the two claims for the same encounter, and resolving differences with the clinician before submission.
- Track grouper and code-set updates. We recommend a calendar entry for each CMS grouper update and the October code set release, with a named owner who confirms the software is current.
- Audit a sample each quarter. We recommend auditing a small sample of inpatient and outpatient claims each quarter against the chart, and recording the error type, not only the count.
Bottom line
Inpatient and outpatient coding differ because they feed different payment systems: ICD-10-PCS and MS-DRG for Medicare inpatient cases, CPT/HCPCS and APC for hospital outpatient services. Status, set by a physician’s order, comes first. If your claims keep running into status or code-set errors, an end-to-end revenue cycle management service can review the whole path from chart to payment, and a free practice audit is the place to start.
Frequently asked questions
What is the main difference between inpatient and outpatient coding?
Inpatient coding reports a formally admitted stay as one case. Diagnoses use ICD-10-CM, procedures use ICD-10-PCS, and Medicare acute-care payment follows the MS-DRG. Outpatient coding reports each service. Hospital outpatient services use CPT and HCPCS codes and pay by APC under OPPS. Status, set by the admission order, decides the path.
Do outpatient claims use ICD-10-PCS?
Not in the Medicare hospital outpatient system described by CMS. Hospital outpatient services under OPPS are reported with HCPCS codes, which include CPT codes. ICD-10-PCS procedure codes feed the MS-DRG grouper for inpatient cases. Always confirm the code set required by each payer and claim type.
What is the two-midnight rule?
For Medicare Part A payment, an inpatient admission is generally appropriate when the admitting physician expects the patient to need hospital care crossing two midnights, supported by medical factors in the record. A valid inpatient order is also required. Exceptions include Inpatient Only procedures and case-by-case stays. It is a payment rule, not a coding rule.
What is the difference between MS-DRG and APC?
An MS-DRG groups an inpatient case from its diagnoses and procedures into one payment per discharge, with severity levels (MCC, CC, non-CC). An APC groups separately paid outpatient services under OPPS, and each HCPCS code carries a status indicator that shows whether it is paid separately or packaged.
What is the difference between principal diagnosis and first-listed diagnosis?
Principal diagnosis applies to inpatient and other non-outpatient coding under Section II of the ICD-10-CM guidelines. First-listed condition applies to outpatient coding under Section IV. The guidelines set different sequencing and uncertain-diagnosis rules for each, so check the setting before assigning the primary code.
What is the difference between facility and professional coding?
Facility coding reports the hospital’s services for a stay or visit. Professional coding reports the clinician’s own work. They are separate claims for the same patient, so diagnoses and procedures should agree. Our guide to hospital vs professional billing explains the claim types in more detail.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Two-midnight rule: standards for inpatient admission (42 CFR 412.3) — CMS (undated)
- Acute Care Hospital Inpatient Prospective Payment System (MLN006815) — CMS / HHS (2020)
- April 2026 Update to the MS-DRG Grouper and MCE Version 43.1 (Transmittal 13562) — CMS (2025)
- Medicare Claims Processing Manual, Chapter 4 (Part B Hospital) — CMS (undated)
- OPPS Addendum D1, payment status indicators — CMS (undated)
- ICD-10-CM Official Guidelines for Coding and Reporting, FY 2027 — CDC / NCHS (2026)
Disclaimer: This article is educational and is not legal, coding, billing, medical or compliance advice. CPT codes are owned by the AMA. Medicare rules, code sets and groupers are updated regularly, and other payers set their own rules. Verify current requirements with CMS, your Medicare Administrative Contractor and each payer before you bill.
