
Modifier 26 bills the professional component of a diagnostic test: the physician's interpretation and written report. Modifier TC bills the technical component: equipment, staff and supplies. A cardiology practice bills one global claim when it performs the test on its own equipment and its physician reads it. For hospital patients, the cardiologist bills only the professional part.
In cardiology, component billing is a daily decision. One echo, stress test or Holter study can become one global claim, two claims from two organizations, or a purchased read with its own payment cap.
This guide uses 2026 Medicare fee schedule data, the Medicare manuals, federal regulations and Medicare Administrative Contractor (MAC) articles. For the service view, see our cardiology billing services.
Key takeaways
- Modifier 26 is the read and report; modifier TC is equipment, staff and supplies; no modifier means global.
- Check the PC/TC indicator first: ECGs, exercise stress tests, Holter monitors and remote device checks use separate codes.
- For hospital patients, the hospital bills the technical side and the cardiologist bills only the read.
- Purchased reads fall under the anti-markup rule: no global claim, the performer named, and a payment cap.
- No separate, signed written report means no billable interpretation.
What do modifier 26 and modifier TC mean?
Modifier 26 reports only the professional component (PC) of a diagnostic test. Modifier TC reports only the technical component (TC). A line with neither modifier is a global claim for both parts.
Noridian, the MAC for Jurisdiction F, defines the PC as the physician’s work interpreting the test, plus related overhead and malpractice costs, and the TC as everything else: staff, equipment and space (page updated July 2025).
The math is additive. In CMS’s 2026 fee schedule data, a complete transthoracic echo with Doppler (CPT 93306) carries 2.02 total relative value units (RVUs) for the PC and 3.87 for the TC; the global value, 5.89, is their sum. Noridian’s modifier 26 guidance (updated May 2025) agrees: the two component fees equal the global allowance. Our guide to RVUs in medical billing explains the units.
Noridian also says to report 26 in the first modifier field and to use no modifier when one provider performed the whole service. These are payment modifiers, unlike 25 and 59, which flag separate services (see our modifier 25 vs 59 guide).
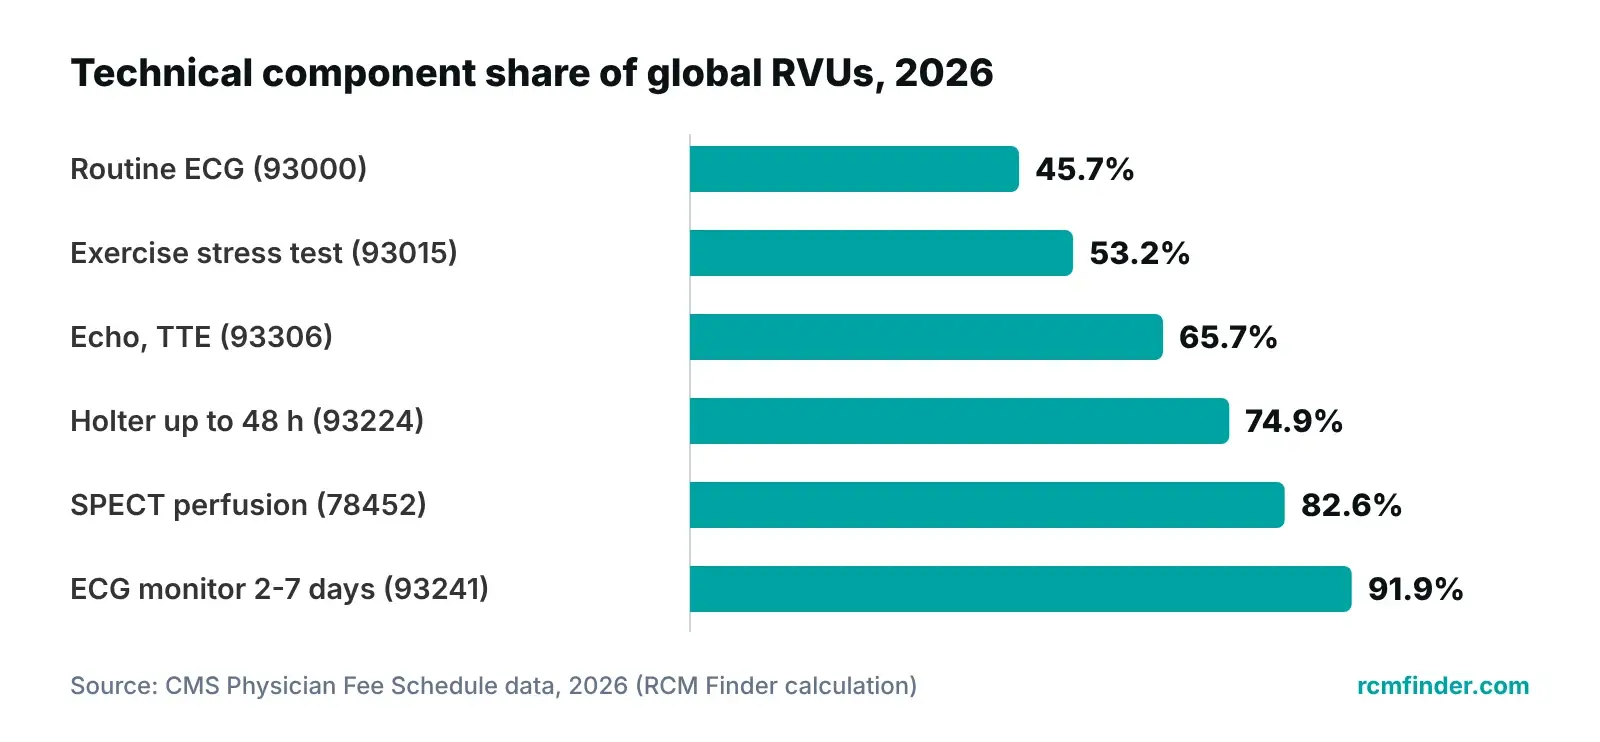
For most of these tests, the technical side carries the larger share. When a hospital performs the test, it is paid for that side separately, and the cardiologist’s claim carries only the read.
How do you know whether a code takes modifier 26 or TC?
Check the code’s PC/TC indicator before adding either modifier. Only indicator 1 codes take 26 or TC. Indicator 2, 3 and 4 codes already describe the professional, technical or global service, so a modifier on them is an error.
CMS defines the indicators in its fee schedule indicator documentation (last modified July 2026):
- 0: physician services, such as visits, that cannot be split. No 26 or TC.
- 1: diagnostic tests with both components. 26 and TC are allowed; a 26 line includes physician work, a TC line only practice and malpractice expense.
- 2: professional-only codes. CMS’s example is 93010, the ECG interpretation and report.
- 3: technical-only codes. CMS’s example is 93005, the ECG tracing alone.
- 4: global-only codes, valued at the sum of their professional-only and technical-only codes.
Cardiology uses both systems. Echo, stress echo, nuclear imaging and in-person device checks split by modifier. ECGs, exercise stress tests, ambulatory ECG monitoring and remote device checks use a separate code per part. Imaging works the same way; see our radiology CPT codes guide.
A common error: 93010-26
Adding 26 to 93010 or 93018, or TC to 93005 or 93017, splits a code that is already split. CMS says 26 and TC cannot be used with indicator 2, 3 or 4 codes. Fix it once in your charge setup, not claim by claim.
Cardiology tests: global, professional and technical codes
Each common test has a global option plus matching professional and technical options. Brackets show the 2026 PC/TC indicator; the last column is the supervision CMS requires for the technical side.
| Test (described in our words) | Global claim | Professional side | Technical side | TC supervision |
|---|---|---|---|---|
| Routine ECG | 93000 [4] | 93010, read and report [2] | 93005, tracing only [3] | General |
| Cardiovascular stress test (exercise or drug) | 93015 [4] | 93016 supervision + 93018 read and report [2] | 93017, tracing only [3] | Direct |
| Complete transthoracic echo with Doppler | 93306 [1] | 93306-26 | 93306-TC | General |
| Stress echo (imaging only, or complete) | 93350 or 93351 [1] | Code with 26 | Code with TC | Direct |
| SPECT myocardial perfusion imaging, multiple studies | 78452 [1] | 78452-26 | 78452-TC | General |
| External ECG recording up to 48 hours (Holter) | 93224 [4] | 93227, review and interpretation [2] | 93225 recording + 93226 scan and report [3] | General |
| External ECG recording, over 48 hours to 7 days | 93241 [4] | 93244, review and interpretation [2] | 93242 recording + 93243 scan and report [3] | General |
| Remote 30-day ECG monitoring (mobile cardiac telemetry) | None | 93228, review and report [2] | 93229, technical support [3] | General |
| Pacemaker check, in person or remote | 93288 [1]; remote: none | 93288-26; remote: 93294 [2] | 93288-TC; remote: 93296 [3] | Direct in person; general remote |
Source: CMS Physician Fee Schedule indicators file for 2026 (PC/TC indicator and physician supervision fields), queried October 2026; CMS indicator definitions (2026). Descriptions are RCM Finder paraphrases, not AMA CPT descriptors.
Two details trip billers up. The stress test’s professional side is two codes, 93016 (supervision) and 93018 (read); each physician bills the part they did. And supervision is a payment condition: 42 CFR 410.32(b) defines direct supervision as presence in the office suite and immediate availability, which the current text lets many services meet by real-time audio-video.
These are 2026 values
CMS’s CY 2027 Physician Fee Schedule proposed rule (July 14, 2026) proposes conversion factors of $33.17 for qualifying APM participants and $32.84 for others, down from $33.57 and $33.40. The final rule and 2027 RVU files will set values from January 1, 2027; recheck indicators and RVUs then.
Who bills which part? It depends on where the test happens
The site of service decides who may bill the technical side. In your office, on your equipment, your practice bills it. For a hospital inpatient or outpatient, the hospital bills it, and your cardiologist bills only the professional side.
Under 42 CFR 410.42, Part B does not pay an outside entity for services to a hospital outpatient without a hospital arrangement; physician services are excepted. The Claims Processing Manual, Chapter 13, §20.2.1 bars Part B payment of the radiology TC for hospital patients, and Noridian’s component page says the fee schedule pays the TC for patients who are not hospital patients.
Place of service follows the patient, not the reading room. Chapter 13, §150 says the place of service on a professional component is the setting where the patient received the technical component, and Chapter 26, §10.6 gives hospital inpatients and outpatients the hospital code regardless of where the face-to-face service occurs. A hospital outpatient’s echo read from your office still takes POS 22 (on campus) or 19 (off campus), not 11; inpatients take 21 (CMS place of service code set; see our place of service codes guide).
| Setting | Technical side | Professional side | Claim notes |
|---|---|---|---|
| Your office and equipment; your cardiologist reads | Your practice | Your practice, same line | One global line, no modifier, POS 11 |
| Your office and equipment; an outside group reads and bills | Your practice: TC or technical-only code | Reading group: 26 or professional-only code | Two claims from two billers |
| Hospital outpatient, on or off campus | Hospital, institutional claim | Your cardiologist: 26 or professional-only code | POS 22 or 19 |
| Hospital inpatient | Hospital, institutional claim | Your cardiologist: 26 or professional-only code | POS 21 |
| Independent diagnostic testing facility (IDTF) | The enrolled IDTF | The interpreting physician | Written order from the treating physician |
| Purchased read or test (performer does not share your practice) | Your practice, never global | Your practice, never global | Item 20 yes; performer’s name, address and NPI in Item 32 |
Sources: 42 CFR 410.33, 410.42 and 414.50 (eCFR, current October 2026); Medicare Claims Processing Manual Ch. 1 §10.1.1.2, Ch. 13 §20.2.1, Ch. 26 §§10.4 and 10.6 (CMS); Noridian JF Part B (2025). Medicare rules only; commercial payers may differ.
The hospital uses an institutional claim and your read a professional one (see hospital vs professional billing and institutional vs professional claims). Noridian adds that parts done at different enrolled locations are billed separately, even by one group.
Purchased interpretations and the anti-markup rule
If your practice orders a test and bills a component performed by a physician who does not share your practice, the anti-markup rule caps what Medicare pays you. You cannot bill it globally, and the claim must name the performer.
Under 42 CFR 414.50, payment is the lowest of three amounts: the performer’s net charge to you, your actual charge, or the fee schedule amount the performer would receive billing directly. For the TC, the performer is the supervising physician; for the PC, the reading physician.
A physician shares your practice if at least 75 percent of their professional services go through it, or if they are your owner, employee or contractor and the component is performed in your office: space where your ordering physician regularly sees patients.
How an anti-markup claim must look
- No global billing. The Claims Processing Manual, Chapter 1, §10.1.1.2 treats globally billed anti-markup tests as unprocessable. Bill TC and PC separately.
- Name the performer. Since October 1, 2015, the performer’s name, address and NPI are required (Items 32 and 32a). Your own NPI in 32a, or one that cannot be verified as Medicare-enrolled, gets the claim returned.
- Mark Item 20. Per Chapter 26, §10.4, yes means someone other than the biller performed the test. Use a separate claim form for each supplier.
- Identify the net charge. Without the performer and its net charge, 42 CFR 414.50(b) allows no payment, and you may not bill the patient.
- Bill your own MAC, priced by the ZIP code where the test was performed (Chapter 1).
For the rest of the form, see our CMS-1500 claim form guide.
“A purchased read is a different claim type, not a shortcut. We set it up that way from the first order, so nobody has to remember the rule at month-end.”
— Awais Afzal, Healthcare Operations & Data Analyst
What the interpretation report must document
A billable interpretation is a separate, signed written report, not a line in the visit note. If the report is missing, unsigned or folded into an E/M note, the professional component is not supported.
Chapter 13, §20.1 says an interpretation includes a written report, and 42 CFR 415.120 pays for radiology interpretations for hospital patients, ultrasound included, only when a written report is prepared for the hospital’s medical record. Noridian’s ECG billing article (A57326) wants a complete, separately identifiable report covering findings, relevant clinical issues and comparative data when available. A brief E/M note is not a separate interpretation.
Wellpoint Federal’s echo article (A56781) adds measurements, Doppler modes, a report kept with the images and the ordering physician’s NPI on the claim. Noridian’s stress testing article (A57183) asks you to document the read of every segment and, preferably on the report, that supervision was met.
Our pre-billing report checklist
- An order from the treating physician (42 CFR 410.32(a)); the biller keeps it and checks that the claim matches.
- Test, date of service and location.
- Findings, relevant clinical issues and comparison with prior studies.
- Test-specific content: echo measurements and Doppler modes, each stress segment, the ambulatory ECG recording period.
- A supervision statement when direct supervision is required.
- The reader’s signature and date. CMS’s signature requirements booklet (July 2025) warns that claims may be denied when signatures fall short; stamped signatures are generally not accepted.
- Diagnoses that match the order (see our chest pain ICD-10 codes and NSTEMI type 1 vs type 2 guides).
One reading per ECG
Noridian’s ECG article says Medicare generally pays for one professional reading of an ECG in institutional settings. A second reading needs a documented unusual circumstance, such as a questionable finding; otherwise it is denied as a quality control service.
Denials and overpayments from billing the wrong component
Wrong-component claims fail in predictable ways: two claims for one technical service, modifiers on codes that cannot take them, and anti-markup claims missing the performer. Some are denied; others are recovered later.
CMS approved Recovery Audit topic 0116, Modifiers TC and PC: Incorrect Coding on August 27, 2025: an automated review of indicator 1 codes paid at the wrong component rate. Our RAC audit guide explains these reviews.
| Error | What usually happens | Prevention |
|---|---|---|
| Global claim for a hospital patient’s test | TC not payable to the physician; the hospital bills it | Hospital studies get 26 or the professional-only code |
| Read billed without 26 after the hospital billed TC | Reads as a claim for both parts; Part B cannot pay the technical part for a hospital patient, so it may be denied | Scrub hospital-site claims for a missing 26 |
| 26 or TC on an indicator 2, 3 or 4 code (93010-26) | Invalid code-modifier pair; expect a rejection or denial | Fix modifier rules in charge setup |
| Payment not matching the 26 or TC rate | Overpayment on automated review (RAC topic 0116) | Compare component payments with the fee schedule |
| Purchased test billed globally, or performer NPI missing | Returned as unprocessable | Separate TC and PC lines; Items 20 and 32 completed |
| Second reading of the same ECG | Generally denied without a documented unusual circumstance | One designated reader per tracing |
| Read with no separate written report | Not separately payable; a brief note is part of the E/M | Hold the claim until the signed report exists |
Sources: CMS RAC topic 0116 (2025); Medicare Claims Processing Manual Ch. 1 and Ch. 13; 42 CFR 410.42; CMS PC/TC indicator definitions (2026); Noridian modifier 26 guidance (2025); Noridian A57326 (2025).
Most are front-end problems. A claim check that knows each code’s indicator and each test’s site catches them before submission.
Check your cardiology claims for component errors
Our free practice audit reviews a sample of your cardiology claims by site, modifier and remittance, and shows where global, 26 or TC billing needs to change.
Get a Free Practice AuditOur recommendations
- Build a test-site map before you bill. We list every test, its site, the equipment owner, the supervisor and the reader, and check hospital reads against the hospital’s study list. That map decides global, 26 or TC.
- Look up the indicator, then the modifier. Each January, when CMS posts new files, we recheck the PC/TC indicator for every diagnostic code in your charge setup. Indicator 2, 3 and 4 codes never get 26 or TC.
- Treat purchased reads as their own claim type. We set up anti-markup claims with separate component lines, Item 20 marked, the performer in Item 32 and the net-charge paperwork on file.
- No signed report, no claim. We hold professional claims until a separate, signed report is in the chart. A one-day delay beats a hard conversation in an audit.
- Check professional-only payments. We compare each 26 and professional-only payment with the expected amount and follow up on short payments.
Bottom line
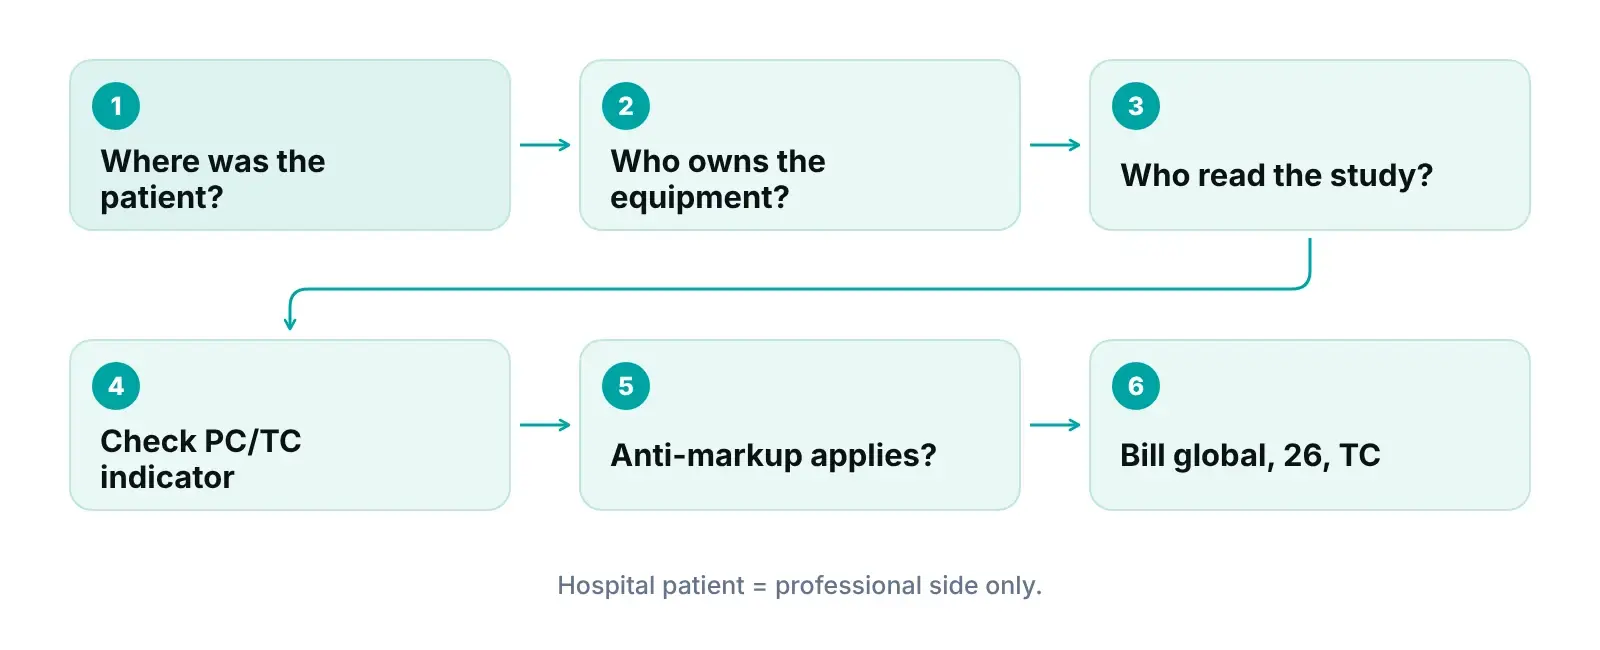
Modifier 26 vs TC comes down to three questions: where the patient was, who furnished the equipment and staff, and who read the study. Answer them per test and per site, check the PC/TC indicator, and handle purchased reads under the anti-markup rule. For help applying this to your claims, see our cardiology billing services or our end-to-end revenue cycle management.
Frequently asked questions
Can a cardiologist bill globally for an echo done in the hospital?
No. For a hospital inpatient or outpatient, the hospital bills the technical side, and Medicare Part B does not pay your practice for it. Your cardiologist bills the read with modifier 26, for example 93306-26, using a hospital place of service. Global billing is for tests your practice performs on its own equipment.
Do we add modifier 26 to 93010 or 93018?
No. Both are professional-only codes (PC/TC indicator 2 in the 2026 Medicare file). CMS says modifiers 26 and TC cannot be used with indicator 2, 3 or 4 codes, because the code already describes one component. The same applies to 93005 and 93017 on the technical side and to the global codes 93000 and 93015.
Which place of service goes on a hospital read done from our office?
For a registered hospital inpatient or outpatient, Medicare’s Claims Processing Manual says the correct place of service is the hospital code, regardless of where the face-to-face service occurs, and that the professional component takes the setting where the patient received the technical component. That means POS 21 for inpatients, 22 for on-campus outpatients and 19 for off-campus outpatients. Check your MAC’s instructions for unusual cases.
Can we bill globally if an outside cardiologist reads our office studies?
Only if the reader shares your practice: for example, your employee or contractor reading in your office, or a physician who furnishes at least 75 percent of their services through your practice. Otherwise the anti-markup rule applies. Bill the technical and professional parts separately, name the performer in Item 32, and expect payment at the lowest of the three amounts in 42 CFR 414.50.
Do commercial payers follow the same 26/TC rules?
Many use the same modifiers and similar logic, but each payer sets its own policies on global billing, site of service, purchased services and accepted codes. Check each payer’s reimbursement policy and your contract before assuming Medicare rules apply. This guide covers Medicare Part B.
How does RCM Finder check component billing?
We start with a free audit that maps each test to its site, equipment owner and reader, then compares that map with your claims and remittances. In the RCM Finder portal, workflow rules can flag a claim for review before submission, and underpayment checks compare payments with expected amounts. Our team works inside your existing EHR.
Get your free practice audit
Tell us about your practice. A member of our operations team replies within one business day.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Status Indicators (PFS Look-Up Tool help: PC/TC indicator, supervision and multiple procedure definitions) — CMS (2026)
- Physician Fee Schedule: Indicators for 2026 (datastore, dataset 7c7df311) — CMS (pfs.data.cms.gov) (2026)
- RVU26D Physician Fee Schedule Relative Value Files (October 2026 release) — CMS (2026)
- Medicare Claims Processing Manual, Chapter 13: Radiology Services and Other Diagnostic Procedures (Rev. 13150) — CMS (2025)
- Transmittal 2679 (CR 7631): Revised and Clarified Place of Service (POS) Coding Instructions — CMS (2013)
- Medicare Claims Processing Manual, Chapter 1: General Billing Requirements (Rev. 13725) — CMS (2026)
- Medicare Claims Processing Manual, Chapter 26: Completing and Processing Form CMS-1500 Data Set — CMS (2026 (accessed; §10.6 last revised 2016))
- 42 CFR 414.50: Physician or other supplier billing for diagnostic tests performed or interpreted by a physician who does not share a practice — eCFR (National Archives) (2026)
- 42 CFR 410.42: Limitations on coverage of certain services furnished to hospital outpatients — eCFR (National Archives) (2026)
- 42 CFR 410.32: Diagnostic x-ray tests, diagnostic laboratory tests, and other diagnostic tests: Conditions — eCFR (National Archives) (2026)
- 42 CFR 410.33: Independent diagnostic testing facility — eCFR (National Archives) (2026)
- 42 CFR 415.120: Conditions for payment: Radiology services — eCFR (National Archives) (2026)
- Modifier 26 (JF Part B) — Noridian Healthcare Solutions (Medicare Administrative Contractor) (2025)
- Billing Professional and Technical Components (JF Part B) — Noridian Healthcare Solutions (Medicare Administrative Contractor) (2025)
- 0116-Modifiers TC and PC: Incorrect Coding (approved RAC topic) — CMS (2025)
- Place of Service Code Set — CMS (2026)
- Billing and Coding: Electrocardiograms (A57326) — Noridian Healthcare Solutions via CMS Medicare Coverage Database (2025 (a draft revision effective 10/01/2026 was displayed on 2026-10-10))
- Billing and Coding: Transthoracic Echocardiography (TTE) (A56781) — Wellpoint Federal via CMS Medicare Coverage Database (2026 (displayed as a draft revision effective 10/01/2026))
- Billing and Coding: Cardiovascular Stress Testing, Including Exercise and/or Pharmacological Stress and Stress Echocardiography (A57183) — Noridian Healthcare Solutions via CMS Medicare Coverage Database (2026 (displayed as a draft revision effective 01/01/2026))
- Complying with Medicare Signature Requirements (MLN905364) — CMS Medicare Learning Network (2025)
- Calendar Year (CY) 2027 Medicare Physician Fee Schedule Proposed Rule (fact sheet) — CMS (2026)
Disclaimer: This article is general educational information about Medicare billing for cardiology diagnostic tests. It is not legal, coding, billing-compliance or financial advice. CPT codes are owned by the American Medical Association and are described here in our own words. Fee schedule values, MAC policies and payer rules vary and change every year; confirm requirements with your MAC, your payers and qualified advisors before acting.
