
Ophthalmology marketing works when medical eye care, cataract surgery and refractive or cosmetic care are planned as three service lines. Medical care runs on referrals, cataract care on Medicare rules and optometry co-management, and refractive care on self-pay advertising that must follow FTC, FDA and professional rules. Measure each line separately.
An eye care practice often sells three different things under one name. Medical eye care is mostly referred and billed to insurance. Cataract surgery is a decision made with a physician and paid largely by Medicare for a conventional lens. Refractive and cosmetic care is a consumer purchase that patients pay for themselves. Each has a different buyer, a different referral source and a different set of advertising risks.
This guide is for owners and managers deciding where marketing effort goes. It covers the plan for each line, how to build optometrist referral relationships without crossing legal lines, which claims need review, and what to measure. Local search is covered in ophthalmology SEO and the site itself in ophthalmology website design, so neither is repeated here.
Key takeaways
- Medical, cataract and refractive care have different payers and decision makers, so each needs its own message, intake path and scorecard.
- Medical eye care grows through referrals. A fast, reliable referral loop matters more than ad spend.
- Cataract marketing must explain what Medicare covers and what a patient may pay for added lens features.
- Referral and co-management arrangements need patient consent, written agreements and legal review, because the Anti-Kickback Statute reaches anything of value.
- Refractive advertising has to balance benefits and risks, and testimonials and reviews are governed by the FTC.
Why does ophthalmology marketing need three separate plans?
Because each line has a different buyer, payer and risk. A glaucoma or diabetic eye patient needs access and a clear referral path. A cataract patient needs help understanding surgery and cost. A refractive patient compares options and pays out of pocket.
Payment is the clearest difference. Original Medicare does not cover routine eye exams (Medicare.gov) but covers a diabetic eye exam once a year when an eye doctor who is allowed to do the test in the state performs it, with 20% coinsurance after the Part B deductible (Medicare.gov). It may cover cataract surgery that implants a conventional lens (Medicare.gov). For LASIK, the FDA’s patient checklist lists cost as a candidacy question: can the person afford the procedure (FDA)? Table 1 sets the lines side by side.
| Service line | Typical patient | How care is usually paid | Marketing job | Lead measure |
|---|---|---|---|---|
| Medical eye care | Referred for glaucoma, diabetic eye disease or a retina problem; urgent eye complaints | Health plan or Medicare, depending on the service | Make referral and access easy; state plans accepted and what to bring | Referrals received and kept, by source |
| Cataract | Older patient with reduced vision, often sent by an optometrist | Medicare or a health plan for the covered surgery; patient pays for non-covered lens features | Explain the process, the evaluation and cost clearly | Surgical evaluations kept and surgeries scheduled |
| Refractive and cosmetic | Consumer comparing LASIK and other vision correction or cosmetic procedures | Usually self-pay; confirm per service | Educate, qualify candidacy, set realistic expectations | Consultations kept and procedures started |
| Crossover | Medical or cataract patient asking about lens options or refractive correction | Separate visits, separate payers | Make options visible without pressure | Consults begun inside other visits |
Source: Medicare.gov (2026); FDA LASIK checklist (content current as of 2018). Payment for any one service depends on the plan and the service.
How is medical eye care marketed when most patients arrive by referral?
Through the referral loop, not through consumer ads. Optometrists, primary care offices and other specialists keep sending patients to the practice that is easy to reach, books quickly and reports back.
A referral program is mostly operations. A few plain habits carry it:
- Give referring offices one number and one form, with a named coordinator who answers.
- Confirm receipt of every referral and tell the referring office the appointment date.
- Send the consultation report back to the referring clinician promptly.
- Log the referral source on every new patient so the program can be measured.
Scripts matter too. A patient who books a routine exam and one who books a medical visit for a diagnosed condition are billed differently, and Medicare does not cover routine eye exams. The way the front desk asks about the reason for the visit should match what the billing team needs, as explained in ophthalmology medical billing. A virtual medical assistant services team can also take calls and referral intake.
What should cataract marketing say when Medicare pays for the surgery?
It should explain the evaluation, the surgery and the cost split honestly, because the covered and non-covered parts are defined by Medicare.
Medicare pays for the covered surgery and a conventional lens. After the Part B deductible, the patient pays 20% of the Medicare-approved amount, and Part B covers one pair of eyeglasses with standard frames or one set of contacts after each cataract surgery that implants a lens (Medicare.gov). Non-covered features need separate handling. In a 2007 ruling on astigmatism-correcting lenses, CMS said the astigmatism-correcting function is not covered, and the beneficiary may be responsible for charges above those for a conventional lens (CMS Ruling CMS-1536-R). Table 2 turns this into intake rules.
| Item | What the source says | What the patient may pay | What marketing and intake should do |
|---|---|---|---|
| Surgery with a conventional lens | Part B may cover surgery that implants a conventional lens | 20% of the Medicare-approved amount after the deductible | Describe coverage as “may” and send patients to the evaluation for specifics |
| Glasses after surgery | Part B covers one pair with standard frames, or one set of contacts, after each lens implant surgery | Cost-sharing rules apply; the page does not state them | Do not promise free or upgraded glasses |
| Astigmatism-correcting function | CMS ruled the function is not covered (2007) | Amounts above the conventional lens charge, plus related services | Show added-feature charges in writing before surgery |
| Routine eye exam | Original Medicare does not cover it | The full cost | Make the exam type clear when booking |
Source: Medicare.gov, cataract surgery and routine eye exams (2026); CMS, Ruling CMS-1536-R (2007). The ruling covers astigmatism-correcting lenses only.
The coding and claim side of cataract surgery is in the cataract surgery billing guide. For marketing, do not put a price or coverage promise in an ad that the evaluation cannot back up.
How do you build optometrist referral relationships without crossing legal lines?
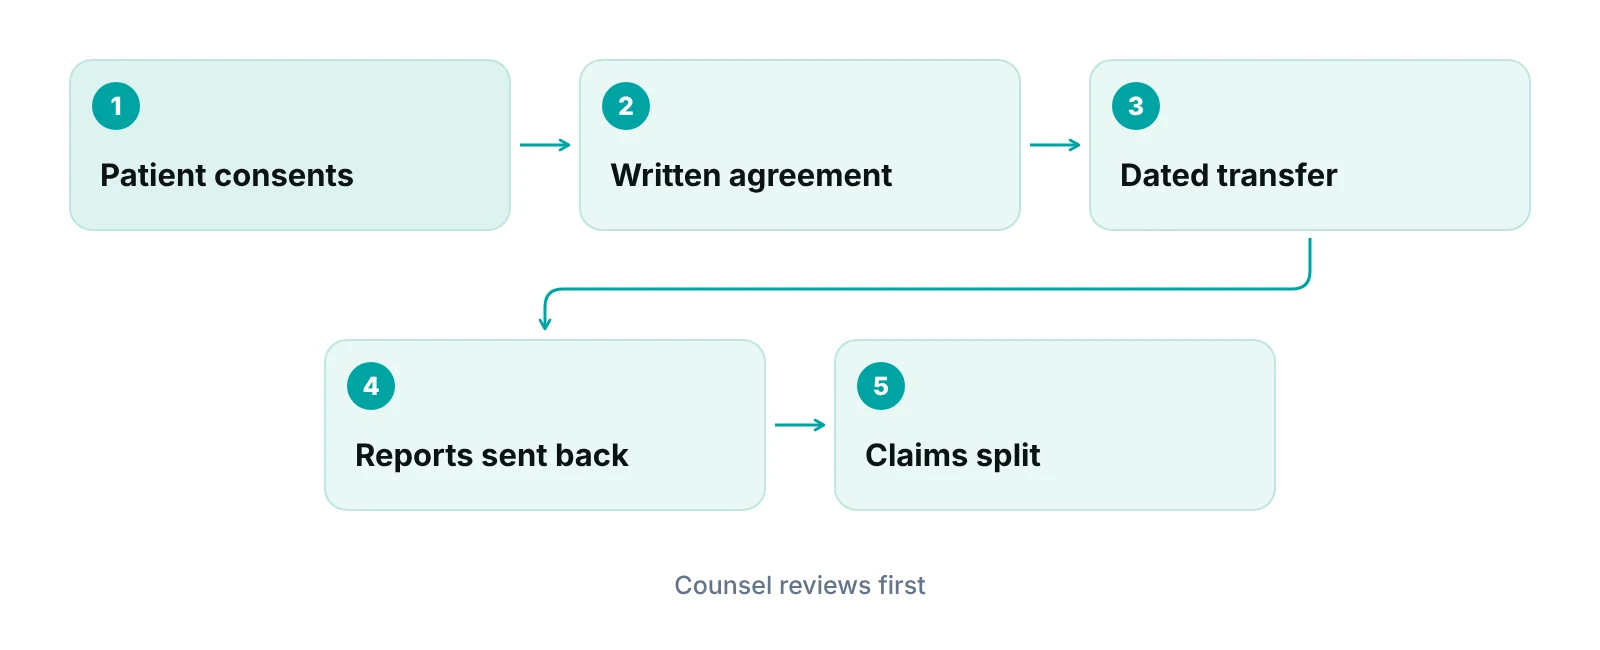
By competing on service and communication, and by putting every co-management arrangement in writing with the patient’s consent. This is the one area where the practice’s attorney should be involved before launch.
The Anti-Kickback Statute is a criminal law against remuneration offered to induce or reward referrals for items or services that federal health care programs pay for, and remuneration includes anything of value. Safe harbors protect only arrangements that fit squarely within them, and each party’s intent is a key element (HHS Office of Inspector General). The American Academy of Ophthalmology notes OIG concern about co-management driven by economic considerations rather than clinical appropriateness, says poorly structured arrangements carry a relatively high degree of regulatory risk, and tells readers to consult counsel before signing (AAO).
The operational side is better defined. Under the First Coast Service Options guidance, a Medicare contractor, split surgical and postoperative care requires a written, dated transfer of care that both physicians keep, and the claims are split with modifiers 54 and 55 (First Coast Service Options). Other contractors may differ, so confirm with yours. The AAO Code of Ethics adds that postoperative referral needs the patient’s approval and that fees should reflect the arrangement, with advance disclosure to the patient (AAO).
Do not market a referral arrangement as a perk
Gifts, meals, free staff, per-referral payments or any offer that rewards sending patients can raise Anti-Kickback concerns. Keep offers to referring optometrists to clinical communication, access and education, and have an attorney review anything of value.
Are your referring optometry offices getting what they need?
Send your referral intake steps and inquiry handling. A free practice audit shows where referral handling and marketing pull against each other.
For the optometry side of the relationship, the practice-operations view is in ophthalmology practice management. The marketing job is narrower: make it easy for an optometrist to refer, to know when the patient was seen, and to receive the patient back.
What rules shape refractive and cosmetic eye advertising?
The FDA regulates the lasers, the FTC polices advertising claims and reviews, HHS sets the privacy limits on using patient information, the AAO sets professional standards, and states add their own rules.
On the FDA side, the agency says it regulates the sale of LASIK lasers and does not tell doctors how to run their businesses (FDA). Its LASIK program page still records that in 2009 the FDA sent eye care professionals information on promoting and advertising lasers, and that in 2011 it reminded them of their legal responsibility to provide balanced information, after complaints that risks were not shared with consumers (FDA). The FDA’s checklist lists risks and limits a patient should understand, including the need for more than one surgery, worsened dry eye, and glare and halos (FDA). In July 2022 the FDA issued draft guidance proposing a patient decision checklist (American Academy of Ophthalmology).
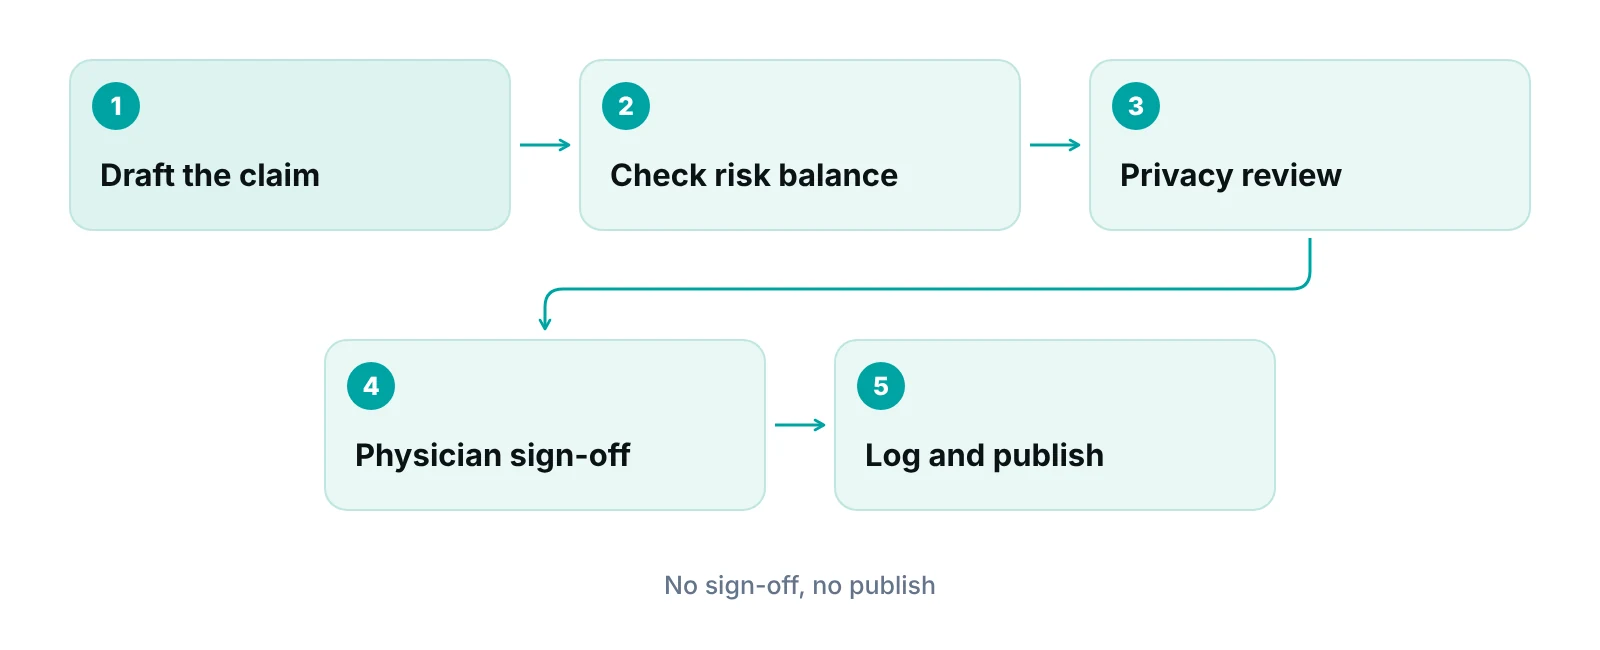
The AAO’s advisory opinion on public communications says they must be accurate, must not omit material information, must not create unjustified expectations, may include accurate testimonials where state law allows, and require substantiation for superiority claims. It also says the ophthalmologist remains responsible for content a marketing firm or staff member writes (AAO). The FTC’s Endorsement Guides add that a connection that could affect how people view an endorsement should be disclosed, and that an unrepresentative testimonial may need context about what consumers can generally expect (FTC).
| Claim or asset | Rule source | What it means for the ad |
|---|---|---|
| Benefits and risks | FDA program page and LASIK checklist; AAO advisory opinion | Give balanced information; do not leave out material risks |
| Expected results | AAO advisory opinion; FTC Endorsement Guides | Avoid guarantees and inflated predictions; add context to unrepresentative results |
| Testimonials and reviews | FTC reviews rule; AAO advisory opinion; state law | No fake or sentiment-conditioned reviews; check state law before using testimonials |
| “Most experienced” and similar claims | AAO advisory opinion | Use only claims that can be substantiated and verified |
| Patient stories and images | HHS marketing guidance; state law | Most marketing uses of patient information need written authorization; privacy officer reviews |
| Paid or insider content | FTC Endorsement Guides; FTC reviews rule | Disclose paid or employee connections clearly |
Source: FDA, AAO, FTC and HHS pages as cited in the text (2026). State law is not covered here and varies.
Wider cash-pay questions, such as influencers and photo galleries, are in the aesthetic practice marketing.
How should reviews and patient stories be handled?
Ask every patient the same way, never write or buy reviews, and treat patient stories as a privacy matter. The FTC’s Consumer Reviews and Testimonials Rule took effect on October 21, 2024. Its staff guidance says incentives cannot require or imply a positive review, paying for five-star reviews violates the rule, employees and relatives must disclose their connection, and reviews on a business’s own review pages may not be suppressed (FTC).
Patient information raises a separate question. HHS says most marketing requires the individual’s written authorization, with exceptions for treatment communications, descriptions of the covered entity’s own health-related services, face-to-face communications and nominal gifts. If a third party pays for the communication, the authorization must say so (HHS). A general announcement of a new service differs from a post featuring a named patient. Have your privacy officer decide which is which, and use the HIPAA compliance checklist as a starting point. Review tactics are covered in the online reputation management guide.
What should each service line be measured on?
Each line needs its own few numbers, because a single count of new patients hides what is working.
- Medical eye care: referrals received, referrals scheduled, referrals kept, and the referring source for each.
- Cataract: evaluations kept, surgeries scheduled, and the optometry offices behind them.
- Refractive and cosmetic: inquiries, consultations kept, procedures started, and the first-contact channel.
- All lines: speed to first response, no-show rate by line, and lead source.
See how a marketing plan fits a mixed eye care practice
Review the healthcare digital marketing service for local search, paid media and reputation work built around your service lines.
Record the source when the call or form arrives, not months later. The medical marketing ROI guide explains how to connect marketing activity to patient and revenue figures. Keep capacity in view as well: a campaign that fills the consultation calendar can crowd out referred medical patients, which is a scheduling question for ophthalmology practice management.
“Referrals follow the practice that answers the phone and sends the report back.”
— Awais Afzal, Healthcare Operations & Data Analyst
Our recommendations
- Write a one-page plan for each service line. List audience, payer, referral sources and one lead measure for each line before setting a budget.
- Fix the referral loop before buying traffic. Name a referral coordinator, confirm every referral and report back quickly.
- Put co-management in writing and have counsel review it. Use a dated transfer of care, patient consent and a lawyer’s review of anything of value offered to referring offices.
- State coverage as "may" and show added-feature charges in writing. Send patients to the evaluation for specifics and give non-covered lens charges before surgery.
- Keep an approval log for refractive claims. Record who approved each risk statement, result claim, credential, testimonial and image, and the authorization behind it.
- Ask every patient for a review in the same way. Use one request process, offer no conditions on sentiment, and disclose staff connections.
- Give each line its own monthly scorecard. Report referrals, evaluations, consultations and no-shows by line, and review them with the billing team.
Bottom line
Ophthalmology marketing succeeds when medical eye care, cataract surgery and refractive care are marketed as what they are: different decisions, paid differently, under different rules. Build the referral loop, document co-management, review every claim and measure each line on its own. To see how this fits a wider plan, review the healthcare digital marketing service. A free practice audit is the next step.
Frequently asked questions
How is ophthalmology marketing different from other specialties?
An eye practice serves referral-driven medical patients, Medicare cataract patients and self-pay refractive patients at once. Each needs its own message, intake path and measures, and refractive advertising adds risk-disclosure, review and privacy rules that other medical lines rarely face. Plan, staff and measure each line separately.
Can we market directly to optometrists for cataract referrals?
Yes, with care. Communication, access, education and prompt reports back are normal. Anything of value offered to induce referrals can raise Anti-Kickback concerns, so have an attorney review gifts, services or payments, and put co-management in a written, dated agreement with the patient’s consent. Your Medicare contractor’s transfer-of-care rules also apply.
Can a practice advertise that Medicare covers cataract surgery?
State it carefully. Medicare may cover surgery with a conventional lens, and the patient generally pays 20% after the deductible. Added lens features may be non-covered, so avoid blanket coverage or free claims and direct patients to the evaluation, where the covered and non-covered parts can be explained in writing.
What does the FDA say about LASIK advertising?
The FDA regulates the lasers and says it does not tell doctors how to run their business. It has also reminded eye care professionals to provide balanced information, including risks, in promotion. The FTC and state rules, and professional ethics standards, apply too, so review each claim before it runs.
Can we offer a discount for online reviews?
Incentives are allowed in some forms, but they cannot require or imply a positive review, and paying for five-star reviews violates the FTC rule. Ask every patient the same way, disclose staff connections, and do not suppress reviews on your own pages.
Should medical and cosmetic eye care share one website and brand?
They can share a brand, but each line needs its own pages, intake questions and scorecard. This helps patients understand what insurance covers and what is self-pay, and it keeps referring offices from seeing a cosmetic message first. Separate landing pages and intake questions make the split work in practice.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Cataract surgery — Medicare.gov (2026)
- Eye exams (routine) — Medicare.gov (2026)
- Eye exams (for diabetes) — Medicare.gov (2026)
- Are you a good or poor candidate for LASIK surgery? (checklist) — FDA (2018)
- The FDA's LASIK program — FDA (2026)
- LASIK: FDA's role — FDA (2026)
- FDA releases draft guidance on LASIK patient label — American Academy of Ophthalmology (2022)
- Ruling CMS-1536-R — CMS (2007)
- Consumer Reviews and Testimonials Rule: Questions and Answers — FTC (2026)
- Advertisement endorsements — FTC (2026)
- Fraud and abuse laws — HHS Office of Inspector General (2026)
- Postoperative co-management: modifiers 54 and 55 — First Coast Service Options (2026)
- Ask the Ethicist: inappropriate fee-splitting or good comanagement contract? — American Academy of Ophthalmology (2026)
- Advisory opinion: communications to the public — American Academy of Ophthalmology (2026)
- Code of Ethics: delegation and comanagement — American Academy of Ophthalmology (2026)
- Marketing (HIPAA Privacy Rule guidance) — HHS (2026)
Disclaimer: This article is educational and is not legal, coding, tax or compliance advice. CPT is a registered trademark of the American Medical Association. Advertising, referral, privacy and medical board rules differ by state and change, and payer rules vary, so confirm current requirements with your attorney, privacy officer, payers and Medicare contractor before acting.
