
ICD-10 codes for mental health are the Chapter 5 diagnosis codes, the F codes, and they tell a payer why a patient was seen. Report the most specific code the note supports, use an unspecified code only when that is all the record shows, and refresh your code list each October 1.
The FY 2027 code set has been in effect since October 1, 2026, and many older guides still show codes that were revised or never valid. This guide lists verified example codes for common conditions, explains how specific a code must be, and points to the pages that cover the CPT side.
Key takeaways
- The FY 2027 ICD-10-CM codes apply to services from October 1, 2026 through September 30, 2027.
- Mental health diagnoses sit in Chapter 5 (F01 to F99); the diagnosis must fit the CPT service billed.
- Report the highest specificity the note supports; use unspecified codes only when the record shows nothing more.
- Several older cheat-sheet codes are wrong or changed, including eating disorder and severe depression codes.
- No US ICD-11 date appears in the sources we reviewed, so plan around the annual ICD-10-CM update.
What ICD-10-CM covers, and what changed on October 1, 2026
The ICD-10-CM code set is updated every fiscal year, and the FY 2027 release took effect on October 1, 2026. The CDC’s file listing shows the FY27 codes applying to services from October 1, 2026 through September 30, 2027, replacing the April 1, 2026 release (CDC/NCHS). CMS posts the same FY 2027 tabular list, addendum and official coding guidelines (CMS). A claim for a visit this month should use the FY 2027 code book, not last year’s cheat sheet.
Mental health diagnoses sit in Chapter 5, Mental, Behavioral and Neurodevelopmental Disorders, which runs from F01 through F99 (CDC tabular list). The chapter is a family of categories, not one list. Dementias, delirium, substance-related disorders, mood and anxiety disorders, eating disorders and sleep disorders each sit in their own block. The guidelines also allow Z codes, which describe other reasons for a healthcare encounter, to be assigned as appropriate (FY 2027 official guidelines).
This page is the diagnosis side of a pair. It shows which codes describe common conditions and how specific the note has to be. The procedure side, meaning evaluation codes, psychotherapy time bands, add-ons and telehealth, is in our guide to coding and billing for mental health services, with code-level detail in the mental health CPT codes guide. We do not repeat that material here.
Is ICD-11 about to replace these codes?
The sources we reviewed do not give a US date. CDC reports that ICD-11 took effect internationally on January 1, 2022, while the United States continues to use ICD-10 for mortality coding (CDC, Health, United States). A 2024 letter from the National Committee on Vital and Health Statistics describes ICD-10-CM as managed by CDC/NCHS and urges HHS to move toward ICD-11, but it states no US transition date (NCVHS). Until a rule sets one, plan around the annual ICD-10-CM update.
How the diagnosis code and the CPT code work together
A CPT code says what the clinician did, and an ICD-10-CM code says why. A mental health claim needs the two to agree, because payers check the diagnosis against the service before they pay.
Novitas Solutions, a Medicare Administrative Contractor, publishes a billing and coding article for psychiatric codes. It lists ICD-10-CM codes that support medical necessity for services including 90785, 90791, 90792, 90832 through 90840, 90845 through 90847 and 90853. It also says the provider is responsible for choosing codes to the highest specificity from the code book in effect for the year of service (Novitas article A57130). Other contractors and commercial payers keep their own lists, so the habit worth building is a check: is this diagnosis accepted for this service on this payer’s list?
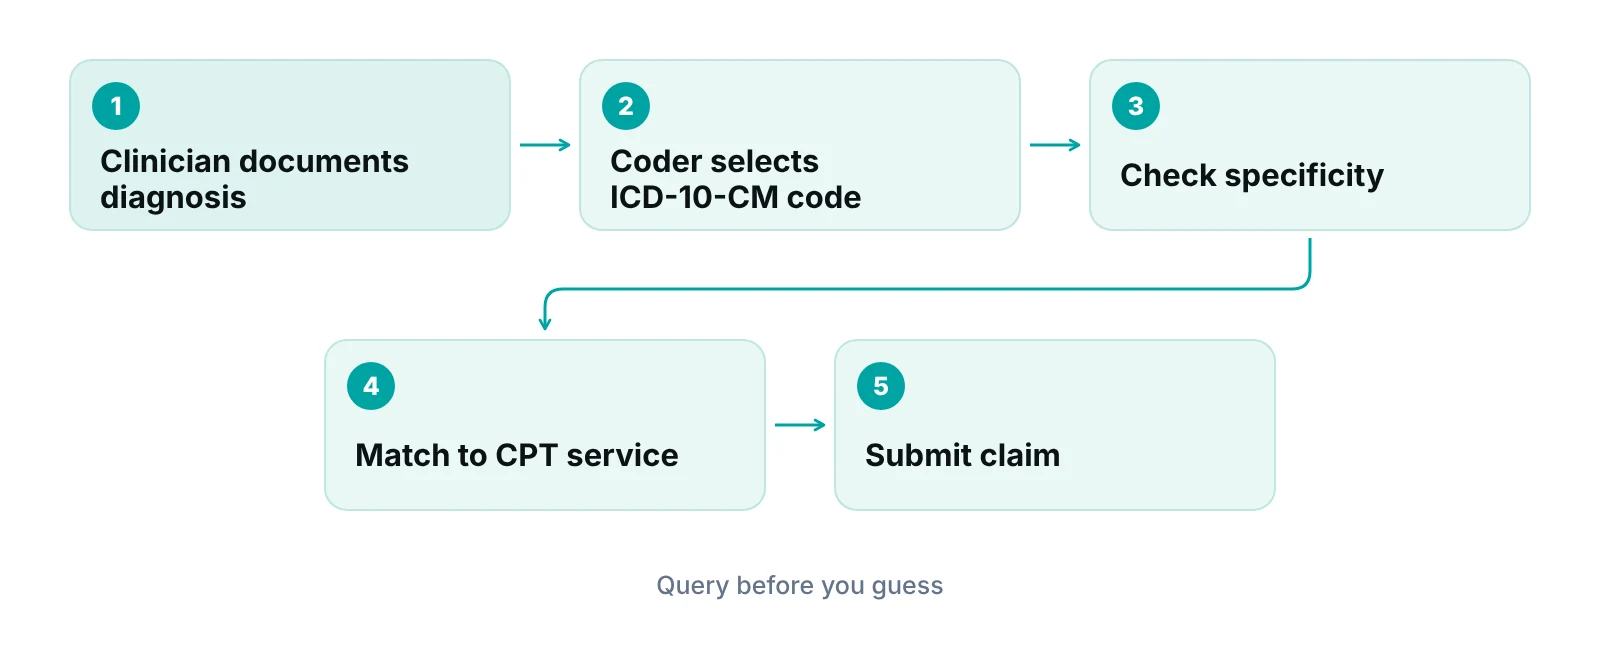
Three roles are easy to blur, so it helps to name them:
- The clinician makes and documents the diagnosis, including severity, episode and remission status where they apply.
- The coder or biller translates that documentation into the code. The guidelines tell coders not to select a specific code the documentation does not support.
- The payer decides whether the diagnosis fits the service billed under its own policy.
Depression, bipolar and anxiety codes
These are the codes mental health practices report most often. The table below uses descriptors from the code list in a Medicare contractor article, grouped in our own wording. It is a sample of the chapter, not every code in it.
| Condition | Code | What the code describes | Coding note |
|---|---|---|---|
| Depressive episode, single | F32.0 to F32.5 | Major depressive disorder, single episode: mild (F32.0), moderate (F32.1), severe without psychotic features (F32.2), severe with psychotic features (F32.3), partial remission (F32.4), full remission (F32.5) | Severity and psychosis are separate codes, so the note must state both |
| Depression, unspecified | F32.A and F32.9 | F32.A is “Depression, unspecified”; F32.9 is major depressive disorder, single episode, unspecified | Use only when the record shows nothing more specific |
| Depressive disorder, recurrent | F33.0 to F33.3, F33.9 | Major depressive disorder, recurrent: mild, moderate, severe without psychotic features, severe with psychotic symptoms; F33.9 is unspecified | The note should say recurrent, not just “depression” |
| Persistent low mood | F34.1 | Dysthymic disorder | Report only when the clinician documents that diagnosis |
| Bipolar disorder | F31.9 | Bipolar disorder, unspecified | The chapter has many more specific bipolar codes; use them when the note supports them |
| Panic disorder | F41.0 | Panic disorder (episodic paroxysmal anxiety) | Separate from generalized anxiety |
| Generalized and unspecified anxiety | F41.1 and F41.9 | Generalized anxiety disorder; anxiety disorder, unspecified | F41.1 needs the diagnosis stated, not just “anxious” |
| Obsessive-compulsive disorder | F42.2 and F42.9 | Mixed obsessional thoughts and acts; obsessive-compulsive disorder, unspecified | Choose by what the note documents |
Source: Novitas Solutions, Billing and Coding: Psychiatric Codes (A57130), code list in the revision effective October 1, 2025 (FY2026 code set). Confirm each code against the FY2027 tabular list.
Two details cause repeat errors. First, F32.2 and F32.3 differ by psychotic features: F32.2 is severe without them and F32.3 is severe with them. Second, F32.A and F32.9 are not interchangeable, because F32.9 names a major depressive disorder and F32.A does not. For a deeper look at the anxiety family, including the phobia and stress codes, see our anxiety ICD-10 codes guide.
Trauma, psychotic, substance use, eating and sleep codes
The second group covers conditions where the code depends on a detail that is easy to leave out of a note: the course of the illness, the substance, the type of reaction or the severity.
| Condition | Code | What the code describes | Coding note |
|---|---|---|---|
| Post-traumatic stress | F43.10 and F43.12 | Post-traumatic stress disorder, unspecified; post-traumatic stress disorder, chronic | Chronic needs the course documented |
| Adjustment disorders | F43.20 to F43.25 | Unspecified (F43.20); with depressed mood (F43.21); with anxiety (F43.22); with mixed anxiety and depressed mood (F43.23); with mixed disturbance of emotions and conduct (F43.25) | The subtype comes from the symptoms the note records |
| Reaction to severe stress | F43.9 | Reaction to severe stress, unspecified | A fallback, not a first choice |
| Psychotic disorders | F20.9, F22, F25.0 | Schizophrenia, unspecified; delusional disorders; schizoaffective disorder, bipolar type | Name the disorder; do not code from a symptom list |
| Alcohol | F10.10 and F10.20 | Alcohol abuse, uncomplicated; alcohol dependence, uncomplicated | Abuse and dependence are different codes |
| Opioid and cannabis | F11.20 and F12.10 | Opioid dependence, uncomplicated; cannabis abuse, uncomplicated | The substance is part of the code |
| Eating disorders | F50.010 to F50.89 | Anorexia nervosa (restricting type F50.010 to F50.014; binge eating/purging type F50.020 to F50.024), bulimia nervosa F50.21 to F50.25, binge eating disorder F50.810 to F50.814, avoidant/restrictive food intake disorder F50.82, other specified F50.89 | Severity or remission is built into the last character |
| Insomnia | F51.01, F51.02, F51.05 | Primary insomnia; adjustment insomnia; insomnia due to other mental disorder | Cause drives the code |
Source: Novitas Solutions, Billing and Coding: Psychiatric Codes (A57130), code list in the revision effective October 1, 2025 (FY2026 code set). Confirm each code against the FY2027 tabular list.
Eating disorder codes are no longer two-character shortcuts
Older cheat sheets list F50.01 for anorexia nervosa, restricting type and F50.02 for the binge-eating/purging type. In the FY2026 code list we checked, those categories carry a severity or remission character: for example F50.010 (mild) through F50.014 (in remission) for the restricting type, and F50.020 through F50.024 for the binge-eating/purging type. A code that stops one character short is incomplete. Confirm the current set in the FY 2027 tabular list.
For the substance rows, use the term the clinician documents, because abuse and dependence are separate codes. The FY 2027 guidelines have a dedicated section for mental and behavioral disorders due to psychoactive substance use (Section I.C.5.b); read it before coding anything beyond these examples (FY 2027 official guidelines). Adjustment disorder has its own page in our library: the adjustment disorder code guide covers when each subtype fits. Sleep complaints that stand alone or co-occur with another condition are covered in our insomnia ICD-10 coding guide.
How specific the code has to be
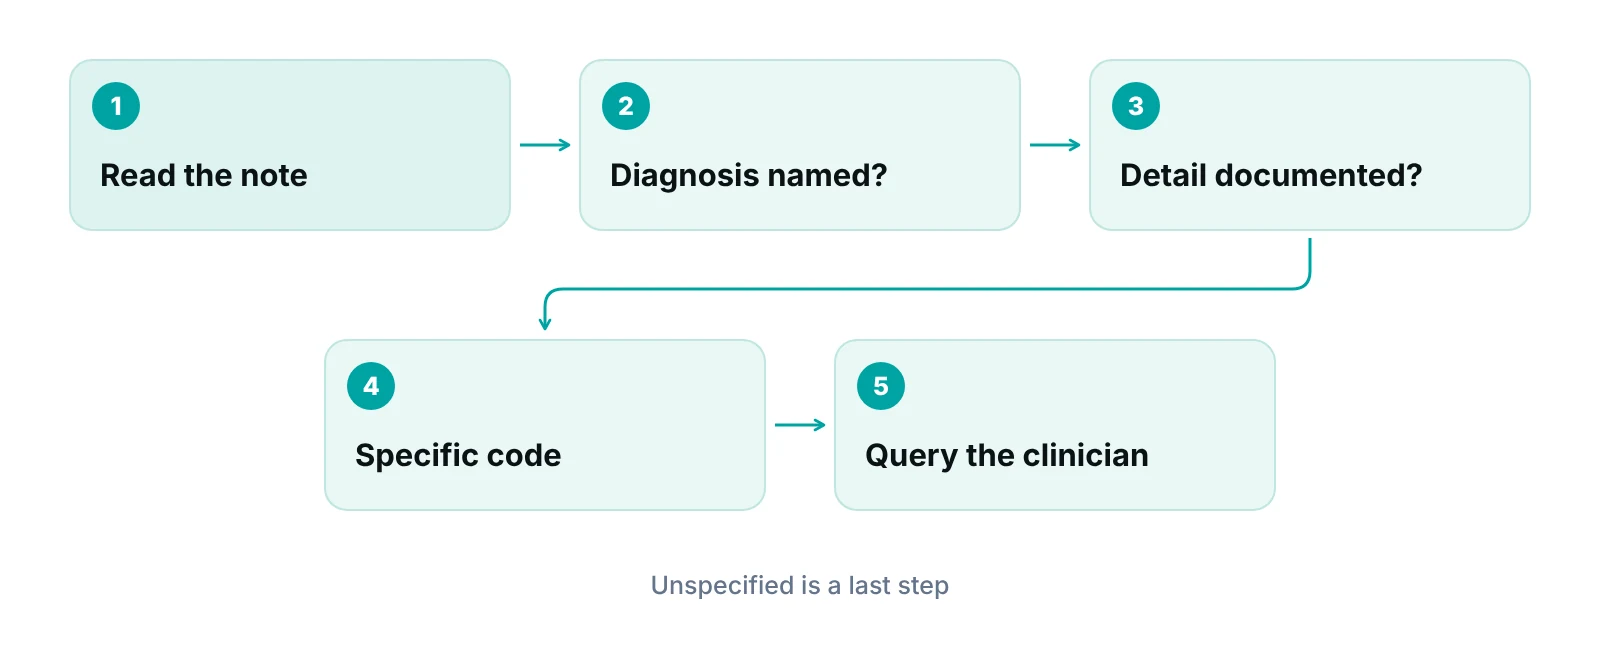
Report each diagnosis at the highest level of specificity the note supports, and no further. The FY 2027 guidelines say codes should be reported at their highest number of characters available (Section I.B.2), and that an unspecified code is appropriate when it best reflects what is known at that encounter. They also tell coders not to pick a specific code the documentation does not support, and not to order unnecessary testing just to reach a more specific one (Section I.B.18) (FY 2027 official guidelines).
Two other guideline rules matter for behavioral health. Sign and symptom codes are acceptable when a related definitive diagnosis has not been established (Section I.B.4), and each unique diagnosis code is reported only once per encounter (Section I.B.12). If a diagnosis is still uncertain, the guidelines have a separate section on uncertain diagnoses in outpatient services (Section IV.H), which is worth reading before a team codes any “rule out” or “probable” wording.
| What the note says | Code it supports | If the note falls short |
|---|---|---|
| “Depression” with no further detail | F32.A, Depression, unspecified | Ask whether a major depressive disorder was diagnosed, and whether the episode is single or recurrent |
| Major depressive disorder, single episode, moderate | F32.1 | Nothing further needed |
| Major depressive disorder, recurrent, severe, with psychotic symptoms | F33.3 | Check the psychotic-symptom wording before coding F33.2 instead |
| “Anxiety” with no diagnosis named | F41.9, Anxiety disorder, unspecified | Ask whether generalized anxiety, panic or another disorder was diagnosed |
| Post-traumatic stress disorder, chronic | F43.12 | Without “chronic” documented, the unspecified code F43.10 is what the record supports |
| Adjustment disorder with anxiety | F43.22 | If the note lists both anxiety and depressed mood, check F43.23 |
Source: code descriptors from Novitas Solutions article A57130 (FY2026 code set); specificity rules from the FY 2027 ICD-10-CM Official Guidelines (CMS). The examples are illustrations, not clinical advice.
“A diagnosis code is only as specific as the note behind it.”
What the note has to contain to support the diagnosis
Strong diagnosis coding starts in the chart. The coder cannot add detail that the clinician did not write, so the fix for most specificity problems is a better note template.
- A named diagnosis. A symptom or a rule-out is not the same as a diagnosis, and the code follows the diagnosis.
- Episode and course. Single or recurrent, chronic or not, in partial or full remission. These details separate neighboring codes in the tables above.
- Severity and features. Mild, moderate or severe, and with or without psychotic features, for conditions where the code set separates them.
- The substance and the pattern of use, for substance-related diagnoses.
- A link to the plan. The treatment plan and the services billed should fit the diagnosis on the claim.
- Updates when the picture changes. A diagnosis carried forward unchanged from an old note will not reflect remission, a new episode or a revised diagnosis.
Most of these gaps surface at the claim stage. Our guide to clean claims in medical billing explains how to catch them before submission, and the behavioral health coding cheat sheet is a quick companion for the procedure codes that go with these diagnoses.
Where diagnosis coding causes denials and delays
Diagnosis problems tend to be repeat problems. The same four patterns account for most of what a billing team ends up reworking.
- Diagnosis does not fit the service. The payer’s list for the billed CPT code does not include the diagnosis on the claim.
- An outdated code after October 1. A picklist or template that still offers last year’s code set produces avoidable errors.
- Too many unspecified codes. They are allowed when they reflect the record, but a pattern of F32.A or F41.9 on every claim signals a documentation gap.
- Diagnosis copied forward. The claim shows a diagnosis the current note no longer supports.
When these turn into rejected or denied claims, the work is to find the pattern, not to re-key one claim at a time. Our behavioral health billing guide covers the wider revenue cycle for these practices, and denial management services can work an existing backlog while you fix the front end.
Check whether your diagnosis coding is costing you claims
Our free practice audit reviews how diagnoses are documented, coded and matched to services, and shows where claims stall.
A yearly routine for the October 1 update
A short routine each fall prevents most code-set errors. It takes a few hours, not weeks, if one person owns it.
- Pull the new files. The tabular list, addendum and guidelines for the new fiscal year are posted by CMS and CDC/NCHS.
- Compare your top diagnoses. List the 25 or so diagnosis codes your practice reports most and check each against the new tabular list and addendum.
- Fix the picklists. Update the diagnosis list in your EHR, superbills and note templates so staff cannot select a retired code.
- Review the payer lists. Where a payer publishes diagnosis-to-service lists, check that your common pairings still hold.
- Brief the clinicians. Share any change that affects how a note should be worded, such as a new severity or remission character.
- Sample claims in November. Pull a handful of claims coded after October 1 and confirm the codes match the notes.
Practices that would rather not carry this load can hand coding support and claim submission to a team that works in medical billing services for behavioral health. If your practice is a therapy, psychiatry or intensive outpatient setting, our page for behavioral and mental health practices describes how that support is organized. For the wider map of how diagnosis, procedure and supply codes fit together, see CPT, ICD-10 and HCPCS codes explained.
Our recommendations
- Build diagnosis wording into the note template. Add fields for episode (single or recurrent), severity, remission status and psychotic features. The code can only be as specific as the template allows.
- Name one owner for the October 1 update. Assign a person and a date each year. Without an owner, retired or revised codes stay in picklists for months.
- Track your unspecified-code rate. Count how often claims carry F32.A, F41.9, F43.10 or F43.20. A rising share points to a documentation gap, not a coding choice.
- Keep a diagnosis-to-service sheet per payer. List which diagnoses each major payer accepts for the evaluation and therapy codes you bill, and update it when a payer publishes a revision.
- Query the clinician, do not guess. When a note is missing a detail, send a short written query. The guidelines say not to choose a code the documentation does not support.
- Retire cheat sheets that do not show a year. Any code list without a fiscal year is a risk. Replace it with one that cites the current tabular list.
Bottom line
Diagnosis coding for mental health comes down to documentation: a named diagnosis, the detail that separates neighboring codes and a yearly refresh of your code list. If denials are already tied to diagnosis problems, denial management services can help work the backlog, and you can also talk to our team about your setup.
Frequently asked questions
What are the ICD-10 codes for mental health?
Most mental health diagnoses sit in Chapter 5 of ICD-10-CM, the F codes from F01 through F99. Examples include F32.1 for a moderate single episode of major depressive disorder, F41.1 for generalized anxiety disorder and F43.10 for post-traumatic stress disorder, unspecified. Claims can also carry Z codes for other reasons for an encounter.
When did the FY 2027 ICD-10-CM codes take effect?
The FY 2027 release applies to services from October 1, 2026 through September 30, 2027, according to the CDC’s file listing. CMS posts the matching tabular list, addendum and guidelines. Update picklists, templates and superbills to the FY 2027 set before billing new dates of service.
Is F32.A the same as F32.9?
No. F32.A is “Depression, unspecified.” F32.9 is major depressive disorder, single episode, unspecified. Pick the code that matches the wording in the note. If the clinician wrote only “depression,” F32.A fits. If the note names a major depressive disorder but no severity, F32.9 may fit.
Can I use an unspecified mental health code?
Yes, when it best reflects what is known at that encounter. The FY 2027 guidelines also say not to choose a specific code the documentation does not support. If unspecified codes appear on most of your claims, that is a documentation signal, so review the note template with your clinicians.
Is ICD-11 replacing ICD-10-CM soon?
The sources we reviewed do not set a US date. CDC says ICD-11 took effect internationally in 2022 while the US continues to use ICD-10 for mortality coding, and a 2024 NCVHS letter urges HHS to plan adoption without giving a transition date. For now, billing follows the annual ICD-10-CM update.
How do diagnosis codes connect to CPT codes?
The CPT code reports the service and the ICD-10-CM code explains why it was needed. Payers and Medicare contractors often publish lists of diagnoses that support each service. Check the pairing before submitting. Our guide to coding and billing for mental health services covers the CPT side.
Get your free practice audit
Tell us about your practice. We will contact you using the details you give.
- A review of your recent claims, denials and A/R aging
- Where your front desk and prior authorizations slow payment
- A prioritized fix list you keep, whether or not you hire us
Pricing is quoted after the audit, based on your volume and the services you choose. Prefer to talk? Call +1 (302) 556-2288.
Sources
- Comprehensive Listing of ICD-10-CM Files — CDC / NCHS (2026)
- ICD-10 codes (FY 2027 files) — CMS (2026)
- FY 2027 ICD-10-CM Coding Guidelines — CMS (2026)
- Billing and Coding: Psychiatric Codes (A57130) — Novitas Solutions via CMS Medicare Coverage Database (2025)
- ICD-10-CM Tabular List of Diseases and Injuries (table of contents) — CDC / NCHS (2022)
- International Classification of Diseases (Health, United States) — CDC / NCHS (2026)
- NCVHS ICD-11 recommendation letter — National Committee on Vital and Health Statistics (HHS) (2024)
Disclaimer: This article is educational and is not clinical, legal, coding or compliance advice. ICD-10-CM is maintained by the CDC National Center for Health Statistics and CMS, and the code set changes each fiscal year. Example codes are illustrations only. Payer and Medicare contractor rules differ and change, so confirm each code against the current tabular list and your payer's policy before you bill.
